Hypoxia and right ventricular dysfunction in patients with acute pulmonary embolism
Related Experiment Video
Updated: Nov 7, 2026
Chronic Thromboembolic Pulmonary Hypertension and Assessment of Right Ventricular Function in the Piglet
Published on: November 4, 2015
Karsten Stannek1,2, Mads Dam Lyhne3,4, Eun Sang Lee1,5
1Center for Vascular Emergencies, Department of Emergency Medicine, Massachusetts General Hospital, 125 Nashua St., Suite 460, Boston, MA, 02114, USA.

Background:
In patients with acute pulmonary embolism (PE), hypoxia may increase pulmonary vascular resistance and worsen right ventricular dysfunction (RVD), which is a key prognostic factor. However, associations between hypoxia, RVD and clinical outcomes have not been well described.
Aim:
To describe associations between hypoxia, RVD and clinical outcomes in patients with PE.
Methods:
We performed a retrospective, single-center cohort study of patients treated by the Massachusetts General Hospital Pulmonary Embolism Response Team (PERT) from 10/2012 to 08/2021. Inclusion criteria included confirmed PE, recorded oxygen saturation prior to PERT activation, and echocardiogram within three days of PERT activation. Patients were categorized into four subgroups based on (1) hypoxia status (SaO₂ below vs. above 95%) and, (2) oxygen support (below vs. above 3 L/min). Our primary outcome was the presence of RVD on echocardiogram. Our secondary outcome was clinical deterioration within 7 days.
Results:
We included 894 PE patients. The mean age was 61 (± 16 SD), 614/894 (69%) were hypoxic, and 624/894 (70%) had RVD on echocardiogram. Overall, hypoxic patients were more likely to have RVD than non-hypoxic patients (467/614 [76%] vs. 157/280 [56%], p < 0.0001). On subgroup analysis, RVD prevalence was highest in the "hypoxic with oxygen support ≥3L" group (n = 216/266, 81%) followed by the "not hypoxic with oxygen support ≥3L" group 53/70 (76%); 198/278 (71%) in the "hypoxic with oxygen support <3L" and 157/280 (56%) in the "not hypoxic with oxygen support <3L" groups. Clinical deterioration occurred in 199/894 (22%) patients and was more common in hypoxic patients than non-hypoxic patients (157/614 [26%] vs. 42/280 [15%], p < 0.0001), and most common in the "hypoxic with oxygen support ≥3L" subgroup 88/266 (33%).
Conclusions:
Hypoxia is associated with RVD and clinical deterioration in patients with PE. More research is needed to understand the risk associated with hypoxia and the physiology of supplemental oxygen support in PE.
Clinical Trial Number:
Not applicable.
Related Concept Videos
 01:29
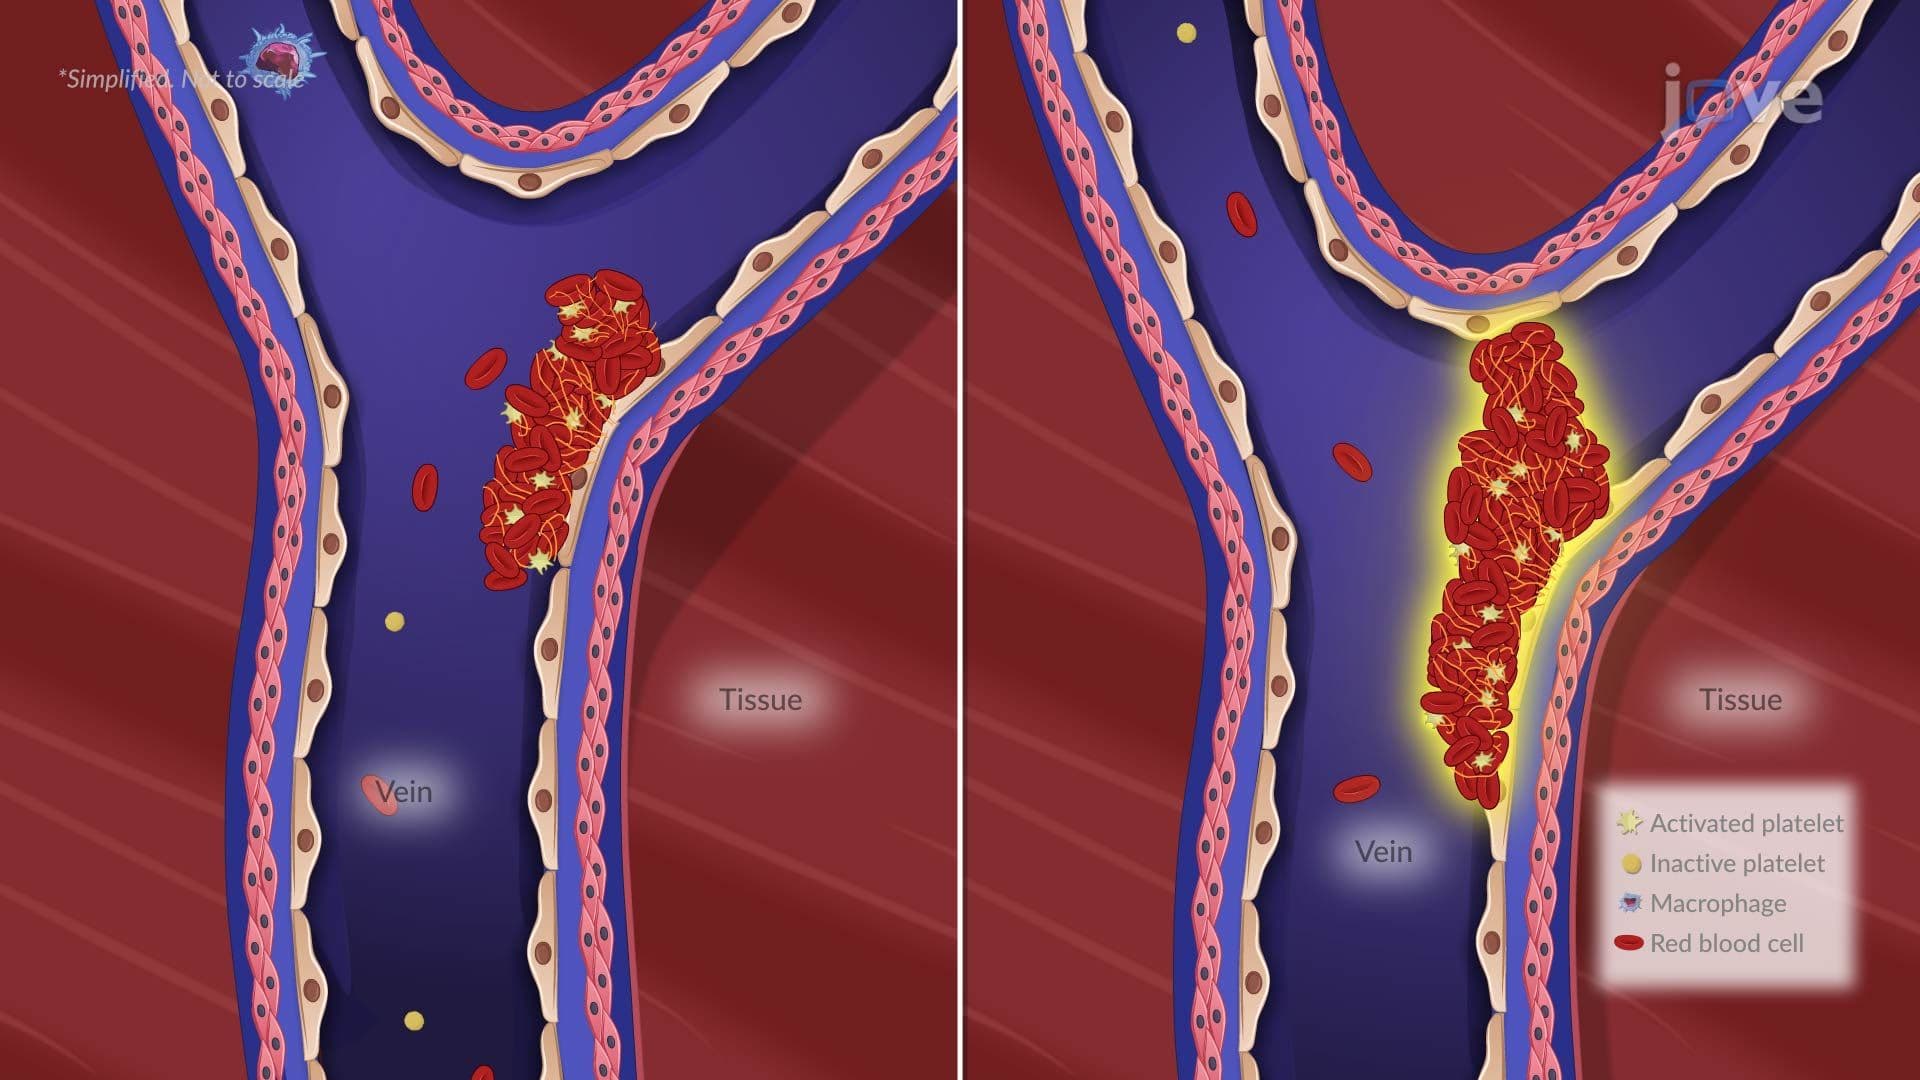
Pulmonary Embolism I: Introduction
 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:27
Pulmonary Embolism III: Nursing Management
 01:18
Pulmonary Edema II: Pathophysiology