Biphasic neonatal Graves disease following maternal thyroidectomy: a case report
Related Experiment Video
Updated: Nov 7, 2026
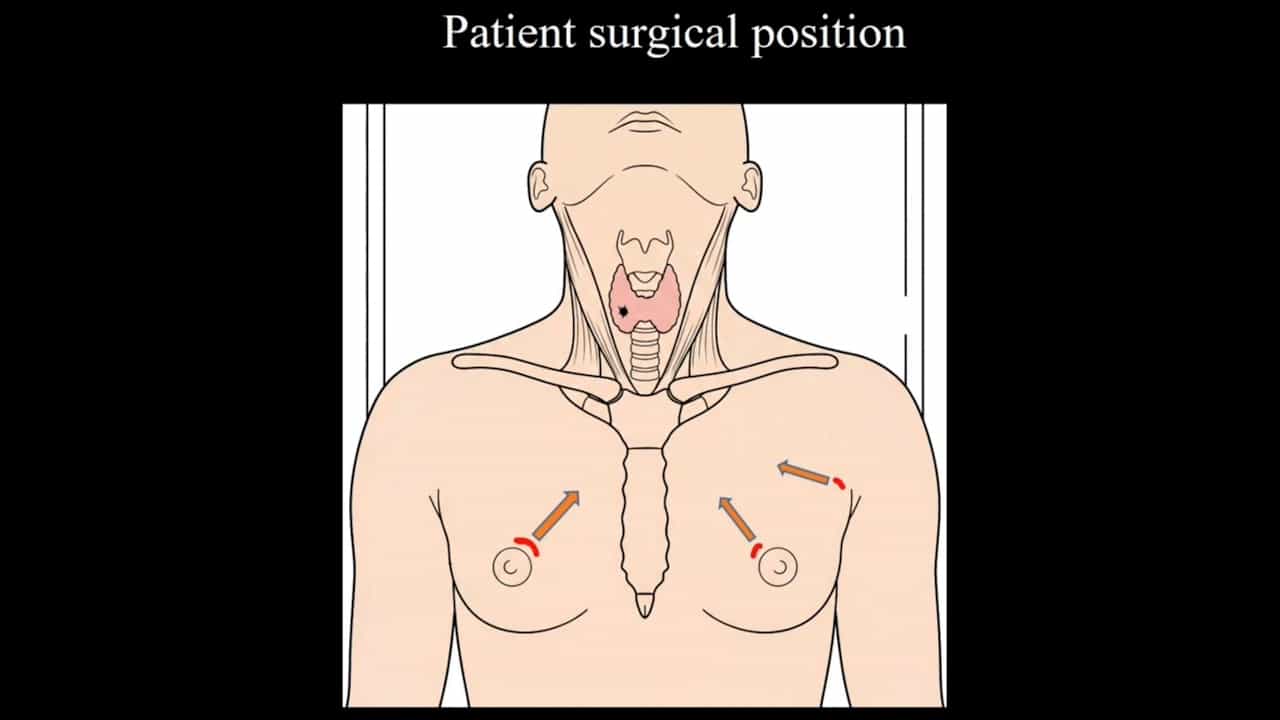
A Novel Contralateral Axillo-Bilateral-Breast Approach for Endoscopic Thyroid Surgery
Published on: July 28, 2026
Luisiana Stolfi1, Maria Scavone1, Elisabetta Placella1
1Neonatology and Neonatal Intensive Care Unit, Regional Hospital San Carlo, Potenza, Italy.

Objectives:
To describe transient neonatal hyperthyroidism in a preterm infant born to a mother with Graves disease previously treated by total thyroidectomy, with no antenatal TRAb assessment and a postpartum maternal TRAb result documented as negative.
Case Presentation:
A male infant was born at 33+6 weeks' gestation to a mother with Graves disease and orbitopathy who had undergone total thyroidectomy 5 years earlier and was receiving levothyroxine. Maternal TRAb were not measured during pregnancy. A privately performed postpartum thyrotropin receptor antibodies (TRAb) test was reviewed by the treating physicians and documented as negative, although the original laboratory report was unavailable. At birth, the infant had suppressed TSH, FT4 >6.28 ng/dL, FT3 22.48 pg/mL, and TRAb 60 IU/L. Thyroid hormone concentrations initially declined spontaneously, with TRAb decreasing to 31 IU/L by day 26. On day 33, FT4 and FT3 increased again, accompanied by agitation and episodic tachycardia. Methimazole was started on day 34. Thyroid function progressively improved, treatment was discontinued on day 110, and subsequent follow-up confirmed persistent euthyroidism.
Conclusions:
Postpartum maternal TRAb results cannot retrospectively define fetal antibody exposure. This case also illustrates that neonatal Graves disease may show a biphasic biochemical course requiring serial monitoring.
Related Concept Videos
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:25
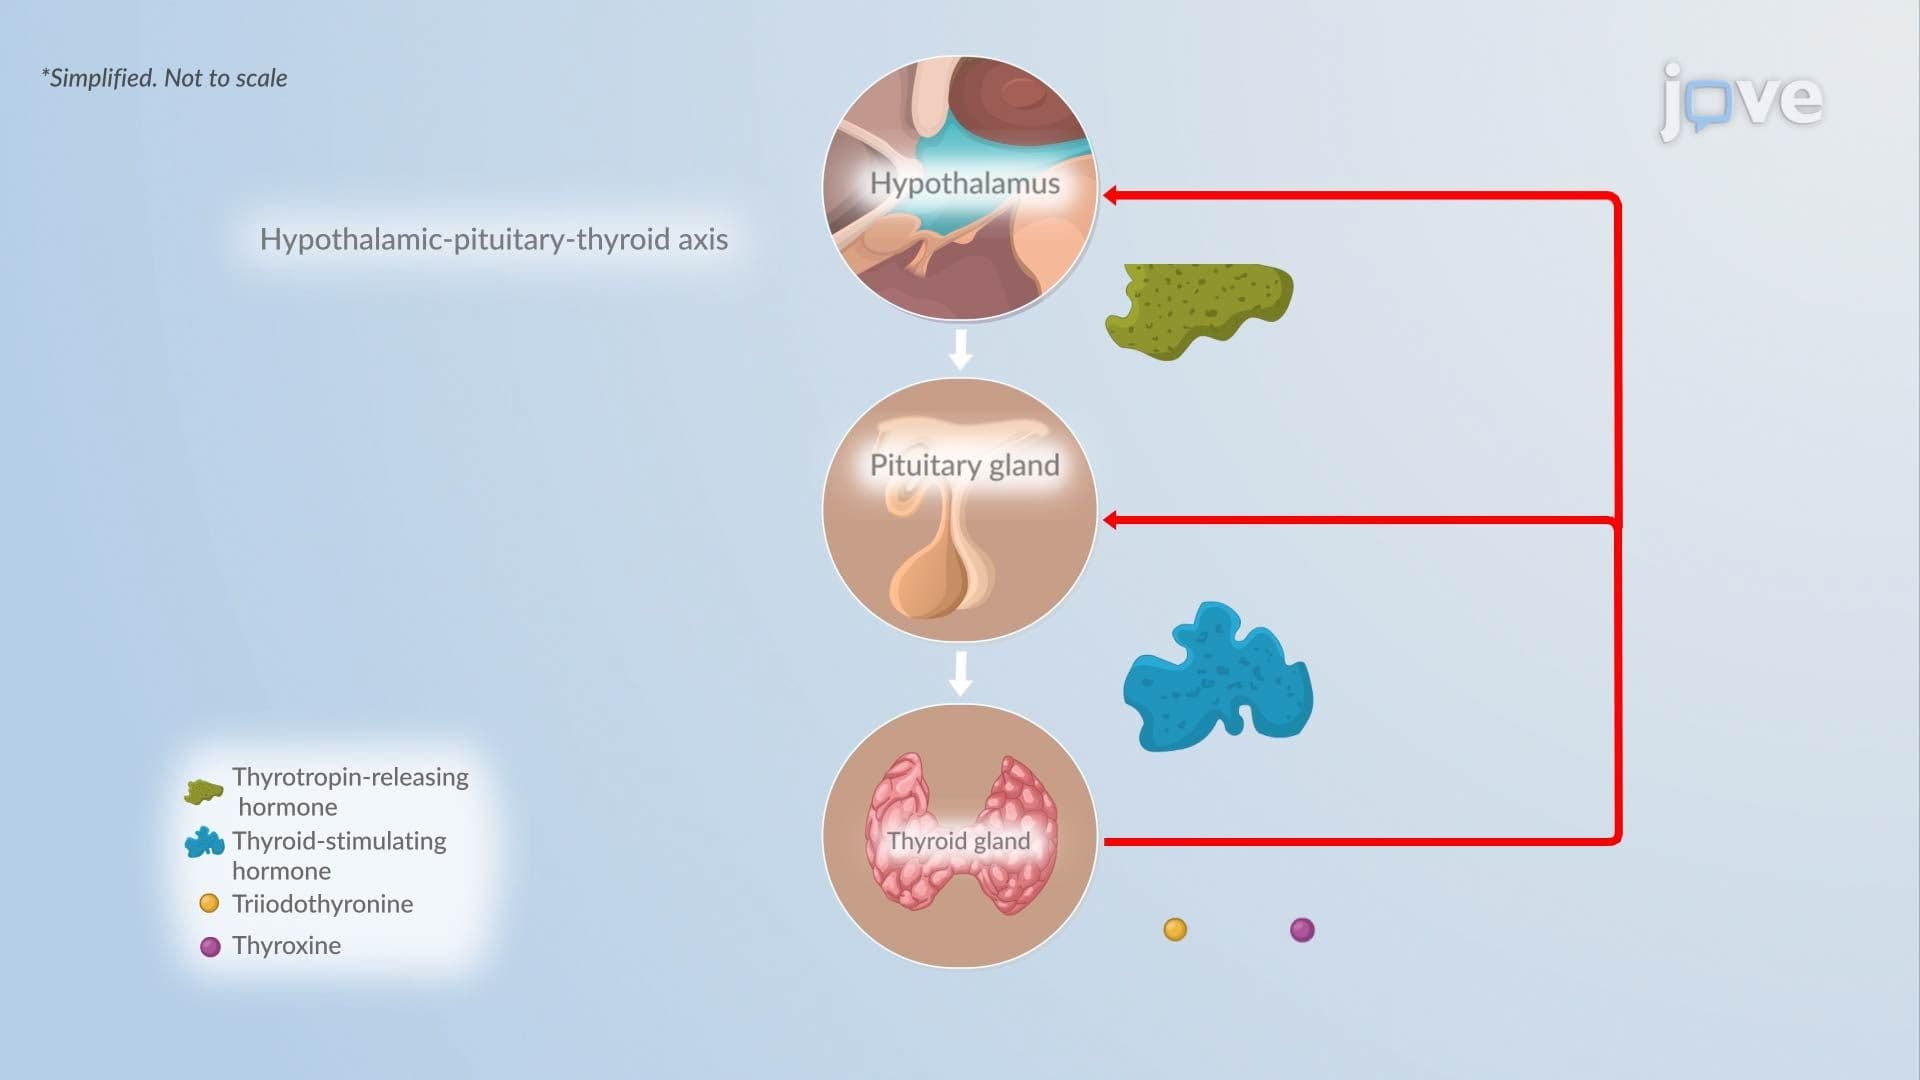
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:27
Goiter
 01:23
Hypothyroidism II: Pathophysiology