Chest physiotherapy for pneumonia in children
Related Experiment Video
Updated: Nov 7, 2026
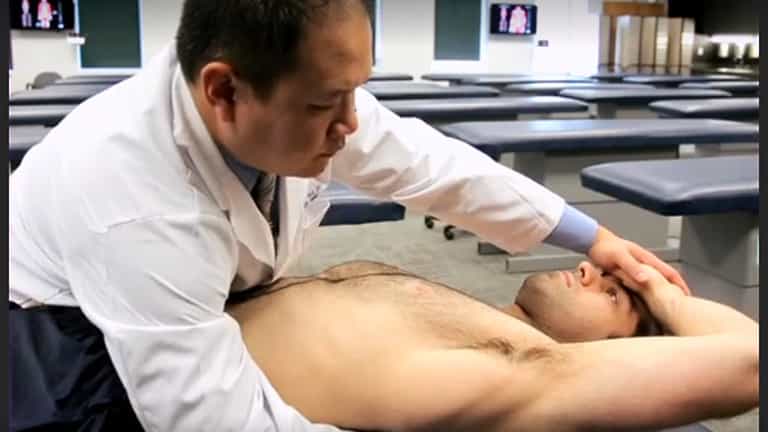
Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Thayla A Santino1, Gabriela Ss Chaves2, Tito Hs Penha3
1Department of Physical Therapy, State University of Paraiba, Campina Grande, Brazil.

Rationale:
Pneumonia is the single largest infectious cause of death in children aged under five years and remains a relevant cause of illness and death amongst older children and adolescents worldwide. Most pneumonia-related deaths occur in low- and middle-income countries, where access to healthcare resources, diagnostic services, and supportive treatments may be more limited than in high-income settings. Chest physiotherapy is widely used as adjuvant treatment for pneumonia. Physiotherapy is thought to help remove inflammatory exudates, tracheobronchial secretions, and airway obstructions, and reduce airway resistance to improve breathing and enhance gas exchange. This is an update of a review first published in 2013 and updated in 2019.
Objectives:
To assess the effectiveness of chest physiotherapy regarding time until clinical resolution in children (from birth to 18 years) of either gender with any type of pneumonia, irrespective of aetiology or clinical classification.
Search Methods:
We searched the Cochrane Central Register of Controlled Trials (CENTRAL), MEDLINE, Embase, CINAHL, LILACS, Web of Science, and PEDro and two clinical trial registries on 8 June 2026.
Eligibility Criteria:
We included randomised controlled trials (RCTs) that compared any type of chest physiotherapy with no chest physiotherapy (i.e. usual care for pneumonia treatment) in children with pneumonia. We did not apply any eligibility restrictions based on gestational age at birth.
Outcomes:
Our critical outcomes were mortality, duration of hospital stay, and time to clinical resolution. Adverse events was an important outcome.
Risk Of Bias:
We used the Cochrane RoB 1 tool for RCTs.
Synthesis Methods:
We used standard Cochrane methodological procedures. Two review authors independently selected studies for inclusion, extracted data, and assessed the risk of bias. For dichotomous outcomes, we calculated risk ratios (RRs) with 95% confidence intervals (CIs). For continuous outcomes measured on the same scale, we calculated mean differences (MDs) with 95% CIs. We synthesised the results for each outcome of interest using a random-effects meta-analysis. When pooling of data was not possible, we described the results narratively. We used GRADE to assess the certainty of evidence for each outcome.
Included Studies:
We included six new RCTs (2304 children) in this update, for a total of 12 RCTs involving 2863 children aged from 29 days to 14 years with pneumonia who were treated as inpatients. Pneumonia severity was described as moderate in two trials, severe in five trials, and was not stated in five trials. The included studies were conducted in Bangladesh, Brazil, China, Egypt, Ethiopia, Malawi, and South Africa. The studies assessed the effects of conventional (4 studies, 287 children), modern (1 study, 29 children), and instrumental chest physiotherapy (7 studies, 2547 children), comprising continuous positive airway pressure (CPAP), bubble CPAP (bCPAP), and thoracic high-frequency chest wall oscillation (HFCWO) devices, compared to no chest physiotherapy. The studies were at overall low risk of bias. Blinding of participants was not possible in most studies, but we considered that the outcomes were unlikely to be influenced by the lack of blinding.
Synthesis Of Results:
Six studies (2294 children) reported mortality. Three studies reported no deaths. However, three studies of bCPAP reported contrasting results: one reported higher mortality in the intervention group (RR 1.52, 95% CI 1.02 to 2.27), whereas the other two found lower mortality in the bCPAP group (RR 0.14, 95% CI 0.03 to 1.16; and RR 0.28, 95% CI 0.08 to 0.90). Due to high heterogeneity amongst the studies, a pooled analysis was not possible (I² = 83%; low-certainty evidence). However, the evidence suggests that chest physiotherapy results in little to no difference in mortality. Nine studies (2069 children) evaluated the duration of hospital stay. Five studies reported no difference between groups, whilst the other four studies found a shorter hospital stay in the group receiving chest physiotherapy. Due to high heterogeneity amongst the studies, a pooled analysis was not possible (I² = 88%; low-certainty evidence). Eleven studies (2219 children) assessed time to clinical resolution. Chest physiotherapy may result in little to no difference in time to clinical resolution of increased respiratory rate (MD -1.21, 95% CI -3.55 to 1.13; 4 studies, 1446 children; low-certainty evidence). Moreover, five studies reported the time to resolution of fever; however, pooling of data was not possible due to high heterogeneity (I² = 94%; very low-certainty evidence). Five studies assessed peripheral capillary oxygen saturation (SpO2), but pooling of data was not possible due to high heterogeneity (I² = 79%; very low-certainty evidence). Two out of five studies showed that children assigned to the intervention group had a significant increase in SpO2 compared to the control group. Regarding symptom improvement, three studies (336 children) found shorter cough and sputum duration in children receiving physiotherapy, whereas one study (89 children) observed a longer coughing period. Six studies (2382 children) reported adverse events. Most studies found no serious adverse events, but mild complications such as nasal irritation, skin breakdown, or abdominal distension were more common in children receiving CPAP or bCPAP. Due to high heterogeneity amongst the studies, a pooled analysis was not possible (I² = 80%; low-certainty evidence). Overall, the evidence was limited by small sample sizes, wide CIs, high risk of reporting bias, heterogeneity across interventions, and variations in outcome definitions. The certainty of evidence ranged from very low to low.
Authors' Conclusions:
We could draw no reliable conclusions regarding the effectiveness of chest physiotherapy for children with pneumonia due to substantial variability in study characteristics and limitations in how data were presented and analysed across the included trials. Future research should ensure adequate methodological rigour, standardisation of physiotherapy techniques, appropriate outcome measures (such as duration of leukocytosis and airway clearance), and careful reporting of potential adverse effects.
Funding:
The review authors declare no funding support or financial conflicts of interest.
Registration:
Protocol (2012) DOI: doi.org/10.1002/14651858.CD010277 Original review (2013) DOI: doi.org/10.1002/14651858.CD010277.pub2 Review update (2019) DOI: doi.org/10.1002/14651858.CD010277.pub3.
Related Concept Videos
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Pneumonia III: Complications and Assessment
 01:27
Pneumothorax-II
Clinical Manifestations: