Computed tomography (CT)-guided fiducial placement for lung nodule localization: a single-center experience
Related Experiment Video
Updated: Nov 9, 2026
Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
Katelyn R Ward1, Ryan Davis1, Varun Vadnala1
1Department of Surgery, Corewell Health William Beaumont University Hospital, Royal Oak, MI, USA.

Background:
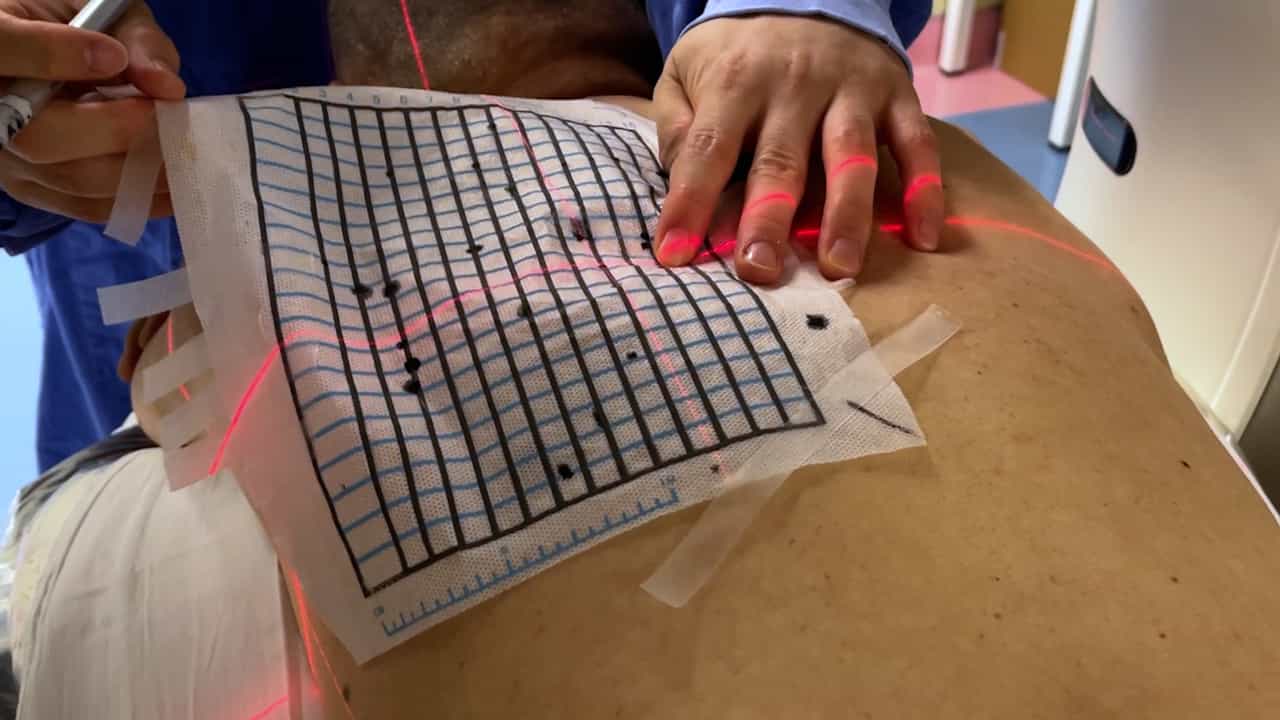
With the adoption of low-dose computed tomography (CT) for lung cancer screening, small lung nodules are increasingly detected. Sublobar resection has been shown to be oncologically equivalent to lobectomy for peripheral lung cancers ≤2 cm and appropriate for small pulmonary metastases, necessitating localization methods for non-anatomic wedge resection. Preoperative CT-guided metal fiducial placement with intraoperative fluoroscopy is one such method. We hypothesized that this technique would enable high resection success with few complications.
Methods:
We performed a single-institution retrospective review of patients undergoing lung nodule resection preceded by CT-guided fiducial placement between 12/2022-2/2025.
Results:
Fiducial placement was successful in 38 consecutive patients. Complications included hemorrhage [3 (8%), self-limited] and pneumothorax [7 (18%); 3 (8%) requiring pigtail catheter]. All fiducials were identified at the time of surgery. Six nodules could be identified by visualization or palpation alone. Operative plans changed in 3 (8%) cases: one lobectomy after three failed wedge resections, and two cases where the fiducial was not retrieved, but resection was deemed adequate. On final pathology, 29 (76%) patients had adenocarcinoma, 5 (13%) had metastases, and 4 (11%) had non-cancerous lesions. All cancer specimens had negative margins with a median distance to the closest cut margin of 1.4 cm (IQR, 0.7-1.9 cm), and the median lung nodule size was 1.2 cm (IQR, 1.0-1.5 cm).
Conclusions:
CT-guided fiducial placement is a reliable localization method. Pneumothorax requiring intervention occurred in 8% of cases. Nearly all fiducials and suspicious lesions were successfully removed via wedge resection. Compared to other methods of nodule localization, CT-guided fiducial placement was generally well tolerated with a high success rate and few complications, was resource-efficient, and demonstrated prolonged intraparenchymal stability. Further studies, including cost assessments, are needed to compare localization methods.