Noninvasive ventilation for non-expandable lung after pleural surgery: a single-center retrospective study
Related Experiment Video
Updated: Nov 9, 2026
Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
Thibault Le Gall1, Valentine Mismetti2,3, Abdulrazzaq Sulaiman1
1Department of Thoracic Surgery, North Hospital, University Hospital of Saint-Étienne, Saint-Étienne, France.

Background:
Non-expandable lung (NEL) is a well-recognized complication of pleural surgery, characterized by failure of the lung to fully re-expand and appose to the parietal pleura, resulting in a persistent pleural space and substantial morbidity. Management of NEL remains challenging, and although the physiological rationale suggests that positive airway pressure could enhance alveolar recruitment and facilitate pleural apposition, the role of noninvasive ventilation (NIV) in treating this condition remains poorly studied. This study aimed to evaluate the potential benefit of NIV on radiological outcomes, as well as its feasibility and safety, for NEL following pleural surgery.
Methods:
This retrospective, single-center observational study included patients who received NIV for NEL following pleural surgery between May 2022 and February 2026. The primary outcome was lung re-expansion after NIV, assessed by chest radiography on day 1 (D1) and day 3 (D3), and at 4 weeks (W4) after discharge. Secondary outcomes included duration of chest tube drainage, length of hospital stay, pulmonary complications, NIV-related adverse events, recurrence of pleural effusion, 30-day mortality, home NIV prescription, and treatment adherence.
Results:
A total of 52 patients, with a median age of 73 years, were included in the final analysis. The etiology of pleural effusion was malignant in 71.2% of cases, and video-assisted thoracoscopic surgery (VATS) was the predominant surgical approach. Complete re-expansion increased progressively, from 42.3% (22/52) at D1 to 73.1% (38/52) at D3 and 86.6% (45/52) at W4 after discharge, while the failure rate decreased correspondingly from 13.5% (7/52) to 3.8% (2/52) over the same follow-up period. Partial re-expansion also followed an inverse trend (44.2% at D1, 19.2% at D3, 9.6% at W4). The median durations of chest tube drainage and hospital stay were each 4 days. Pulmonary complications occurred in 2 patients (3.8%), recurrence of pleural effusion in 3 patients (5.8%), and no 30-day mortality was observed. NIV was well tolerated, with only minor adverse events; treatment adherence reached 94.2%, and 32.7% of patients were discharged with home NIV.
Conclusions:
In this preliminary, single-center, uncontrolled experience, NIV was feasible and associated with progressive radiological lung re-expansion in patients with established NEL following pleural surgery, with infrequent adverse events. These findings provide a preliminary proof of concept supporting NIV as a potential adjunct to standard postoperative care in this indication. Prospective, multicenter, randomized controlled trials, stratified by the mechanism of NEL, are needed to confirm this potential benefit and identify the patients most likely to benefit.
Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:27
Pneumothorax-II
Clinical Manifestations:
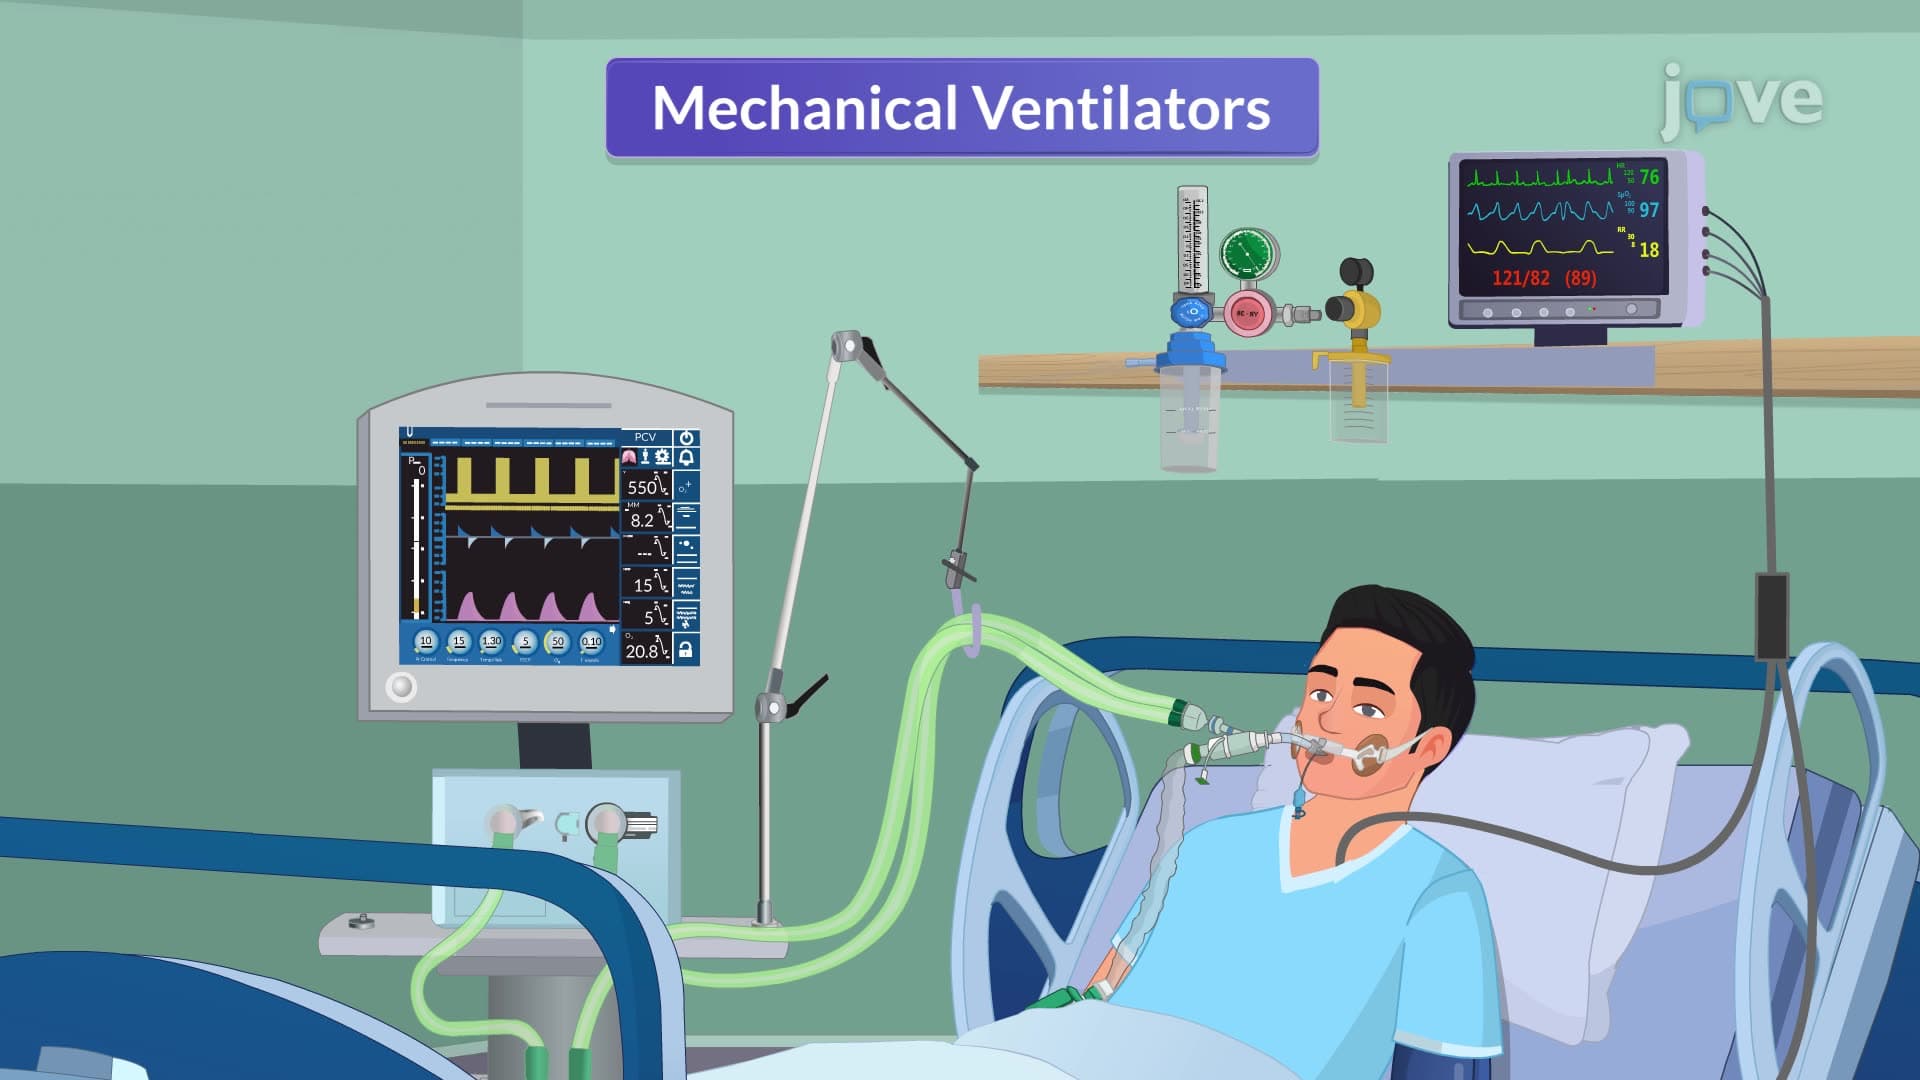 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...