Routine foreskin pathology in adults: Low yield, high cost-Time to change practice?
Related Experiment Video
Updated: Nov 9, 2026
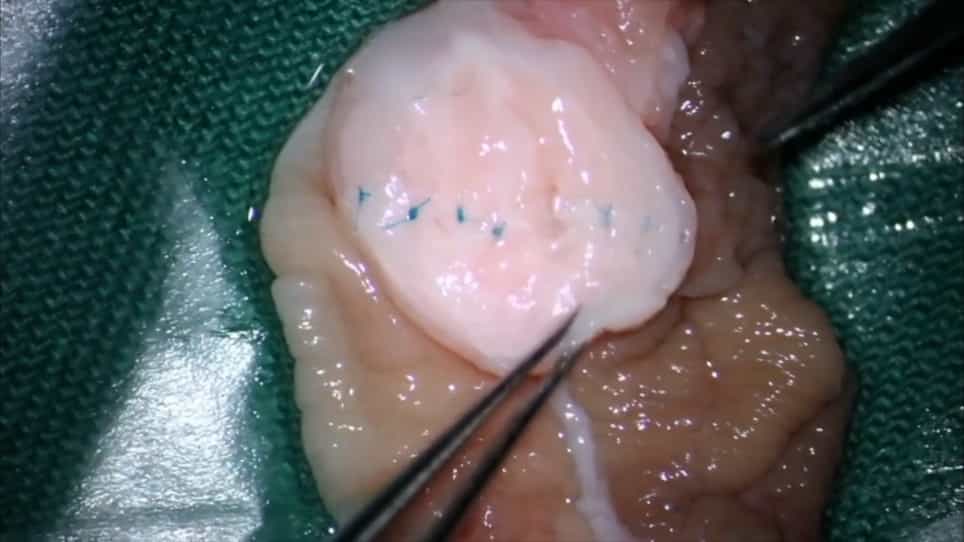
Microscopic Replantation of Penile Glans Amputation Due to Circumcision
Published on: June 3, 2022
Kenneth A McLean1,2, Ellen Gardner1, Kathryn Kirkwood3
1Department of Urology University of Edinburgh, Western General Hospital Edinburgh UK.

Objective:
This study aimed to determine the diagnostic yield for malignant lesions and cost-effectiveness of routine foreskin pathology in adults.
Subjects/Patients And Methods:
A retrospective audit was conducted of all adult circumcisions (age ≥16) performed between January 2015 and February 2025 at a UK tertiary centre. Clinical and pathology records were reviewed to identify unexpected cancer diagnoses-defined as cases with no prior biopsy evidence or clinical suspicion. The number needed to screen (NNS) to detect one cancer was calculated, and pathology costs were estimated based on local processing costs and the pathologist workload score for each sample.
Results:
There were 2503 adult circumcisions performed between 2015 and 2025, with 2.6% (n = 66/2503) cancers detected on pathological assessment. Of these, 78.8% (n = 52/66) patients with confirmed penile cancer had clinically suspicious findings pre-operatively. Therefore, the NNS on routine pathology for unexpected cancers was 109.4 (95% CI = 65.4-183.4), and only one clinically significant cancer (7.1%, n = 1/14 [0.04% overall cohort]) required further treatment (topical ablation). The diagnostic yield was also age-dependent, with low diagnostic yields in patients below age 40 with potentially suspicious pathology (NNS = 178.5, 95% CI: 49.5-650.3). Pathology-associated costs were estimated at £65 584 over the study period (£994 per cancer identified). Targeting pathology to men aged ≥40 with clinical suspicion of cancer would reduce costs by 73.3% (£48 074), while reducing the cost per cancer detected to £350.
Conclusion:
Routine foreskin pathology after adult circumcision has a low diagnostic yield for unexpected malignancy and rarely alters management. Targeting pathology to higher yield patient groups may optimise resource use, aligning with national guidelines and delivering substantial cost savings.