Postoperative prophylactic and delayed oral antibiotics after total shoulder arthroplasty: a multi-institutional database analysis
Related Experiment Video
Updated: Nov 10, 2026
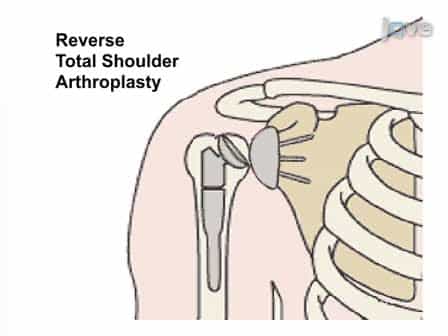
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Tarek Haj Shehadeh1,2, Anjan Singh1, Jawaad Chaudhry1
1Department of Orthopaedics and Therapy Services, Penn State Health, Penn State Milton S. Hershey Medical Center, Hershey, PA, USA.

Background:
To evaluate the effectiveness and safety of prophylactic and delayed postoperative oral antibiotics following total shoulder arthroplasty (TSA).
Methods:
The TriNetX database was queried for primary TSA patients. Those with prior pathologic fracture, upper extremity malignancy, infection, prosthetic joint infection (PJI), or revision surgery within 6 months were excluded. After 1:1 propensity score matching, two comparisons were performed: (1) prophylactic oral antibiotics within 1 postoperative day versus controls (n=5,891 per cohort) and (2) delayed oral antibiotics on postoperative days 7-30 versus controls (n=3,087 per cohort). Outcomes at 30 and 90 days included acute kidney injury (AKI), emergency department (ED) visits, readmission, PJI, and revision surgery.
Results:
At 30 days, prophylactic antibiotics were associated with fewer readmissions (2.78% vs. 3.73%; P=0.004), with no differences in AKI, ED visits, PJI, or revision surgery. At 90 days, they were associated with higher PJI (0.92% vs. 0.48%; P=0.004) and a trend toward lower ED visits (5.25% vs. 6.16%; P=0.032) and readmissions (3.70% vs. 4.67%; P=0.009), but higher revision surgery (1.17% vs. 0.73%; P=0.014). Delayed antibiotics were associated with higher rates of AKI, ED visits, readmissions, and revision surgery at both 30 and 90 days (all P<0.001), as well as higher PJI at 90 days (3.14% vs. 0.42%; P<0.001).
Conclusions:
Although residual confounding cannot be excluded, postoperative prophylactic or delayed oral antibiotics were not associated with reduced PJI or revision surgery and may be associated with antibiotic-related adverse effects. Level of evidence: III.