Single-session radiosurgery for Cushing disease after failed resection: a retrospective single-center cohort study
Related Experiment Video
Updated: Nov 11, 2026
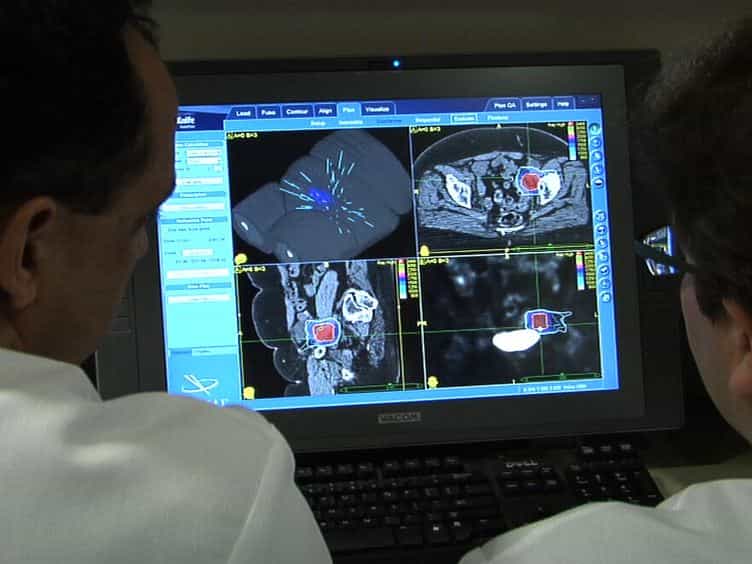
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Bardia Hajikarimloo1, Salem M Tos1, Yuki Shinya1
1Department of Neurological Surgery, University of Virginia, Charlottesville, VA 22908, USA.

Context:
Cushing disease (CD) from an adrenocorticotropic hormone-secreting pituitary adenoma causes substantial morbidity when hypercortisolism persists or recurs after transsphenoidal surgery (TSS).
Objective:
To define endocrine control, radiographic response, toxicity, and predictors after single-session Gamma Knife radiosurgery for residual or recurrent CD.
Design:
Retrospective single-center cohort study, 1990-2026; median endocrine follow-up 54 months.
Setting:
Single academic tertiary referral center.
Patients:
186 adults with residual or recurrent CD after ≥1 TSS and ≥12 months of follow-up. Median age 40.8 years; 78.0% female.
Intervention:
Single-session frame-based SRS (median prescription dose 23.0 Gy; maximum dose 48.0 Gy).
Main Outcome Measures:
Prespecified primary outcome was durable biochemical control off medications (sustained 24-hour urinary free cortisol [UFC] normalization without cortisol-lowering therapy), modeled with competing-risks methodology.
Results:
UFC normalized in 152 patients (81.7%), including 134 (72.0%) off all medications. Cumulative incidence of durable off-medication control was 51% (95% CI: 44-58%) at 12 months and 64% (95% CI: 56-71%) at 120 months. New endocrinopathy reached 42% (95% CI: 32-52%) at 120 months; new visual deficit occurred in 3.2%. A TSS-to-SRS interval <6 months independently predicted higher durable control (P < .001), while higher baseline AM cortisol (P < .001), whole-sella treatment (P = .013), and female gender (P = .027) predicted lower durable control. Higher maximum dose was the sole independent predictor of new endocrinopathy (P = .009).
Conclusion:
Single-session SRS achieves durable medication-free control in approximately two-thirds of patients with residual or recurrent CD, with excellent tumor control and meaningful delayed endocrine toxicity warranting long-term surveillance.
Related Concept Videos
 01:26
Cushing Syndrome I: Introduction
 01:19
Cushing Syndrome II: Pathophysiology