A Study on Eloesser Flap Reconstruction: How to Plug the Hole
Related Experiment Video
Updated: Nov 12, 2026
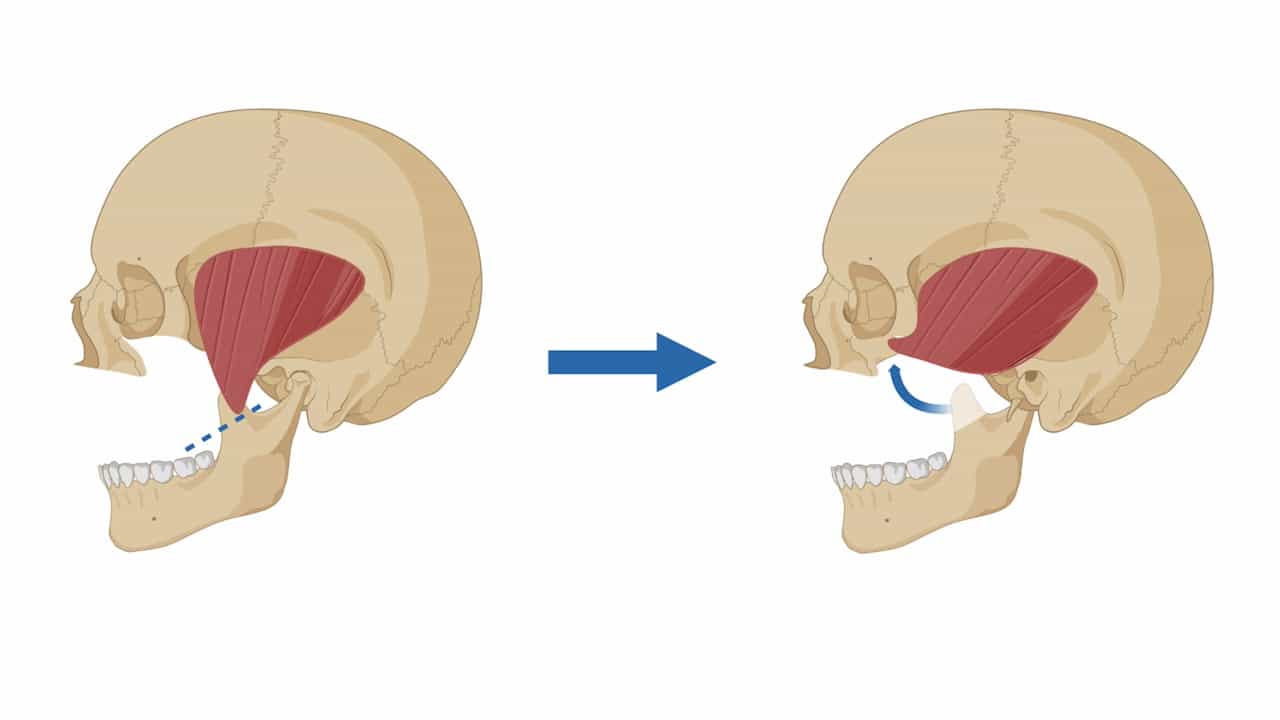
Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Jasmine Lam1,2, Artin Allahverdian2, Bao-Quynh Julian3
1From the Department of Plastic Surgery, Arrowhead Regional Medical Center, Colton, CA.

Background:
Eloesser flap reconstruction remains challenging because prior thoracic surgery, local vasculature disruption, and chronic infection can limit reconstructive options. Reconstruction must restore chest wall mechanics, address bronchopleural fistulae, obliterate pleural dead space, and provide durable coverage. Standardized strategies for reconstruction of Eloesser flap defects remain limited.
Methods:
We reviewed the clinical experience at a single institution in Eloesser flap reconstruction and integrated these findings with a literature review and anatomic considerations. A reconstructive algorithm was developed based on the presence of bronchopleural fistulae, pleural dead space, and defect size. Reconstructive options included omental and muscle flaps for dead space obliteration and musculocutaneous flaps for durable soft-tissue coverage.
Results:
Four patients underwent Eloesser flap reconstruction. The proposed algorithm prioritizes bronchopleural fistulae management before chest wall closure. When residual pleural dead space was present, vascularized tissue was used for obliteration, with the serratus anterior muscle preferred for its thin profile, pliability, and favorable intrathoracic reach. For larger defects, double opposing latissimus dorsi musculocutaneous flaps provide soft-tissue coverage and facilitate epithelialization. This approach enabled simultaneous management of pleural dead space and chest wall defects while preserving thoracic function.
Conclusions:
Reconstruction of Eloesser flap defects requires individualized consideration of fistula status, dead space, defect size, and tissue availability. Our experience supports an approach incorporating vascularized muscle and musculocutaneous flaps, with the serratus anterior offering a reliable option for intrathoracic dead space obliteration. Larger studies are needed to validate this algorithm and define long-term functional outcomes.