Related Experiment Video
Updated: Sep 12, 2026


Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
Bronchiolitis and bronchitis in connective tissue disease. A possible relationship to the use of penicillamine

Rapid onset of severe and irreversbile airflow obstruction developed in two women. One had eosinophilic fasciitis and the other had rheumatoid arthritis. Both were treated with penicillamine. In the first patient, aged 42 years, dyspnea developed after six months of therapy. Her roentgenogram showed hyperinflation. Forced vital capacity expired in one second (FEV1/FVC%) decreased from 75% to 40%, and the residual volume increased by 1 L. In the second patient, aged 54 years, cough and dyspnea developed after ten months of therapy. The FEV1/FVC% was 56%, the FEV1 was 0.9 L, and the roentgenogram was normal. Lung biopsy specimens demonstrated severe and widespread bronchiolitis. An association between obliterative bronchiolitis and rheumatoid arthritis has been reported. Penicillamine may impair healing of bronchiolitis in such patients.
Rapid onset of severe and irreversbile airflow obstruction developed in two women. One had eosinophilic fasciitis and the other had rheumatoid arthritis. Both were treated with penicillamine. In the first patient, aged 42 years, dyspnea developed after six months of therapy. Her roentgenogram showed hyperinflation. Forced vital capacity expired in one second (FEV1/FVC%) decreased from 75% to 40%, and the residual volume increased by 1 L. In the second patient, aged 54 years, cough and dyspnea developed after ten months of therapy. The FEV1/FVC% was 56%, the FEV1 was 0.9 L, and the roentgenogram was normal. Lung biopsy specimens demonstrated severe and widespread bronchiolitis. An association between obliterative bronchiolitis and rheumatoid arthritis has been reported. Penicillamine may impair healing of bronchiolitis in such patients.


Related Concept Videos
 01:22
Connective Tissue Cell Types
Fat cells (adipocytes), smooth muscle cells (myoblasts), and bone cells (osteoblasts) are some connective tissue cell types. Some immune system cells...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
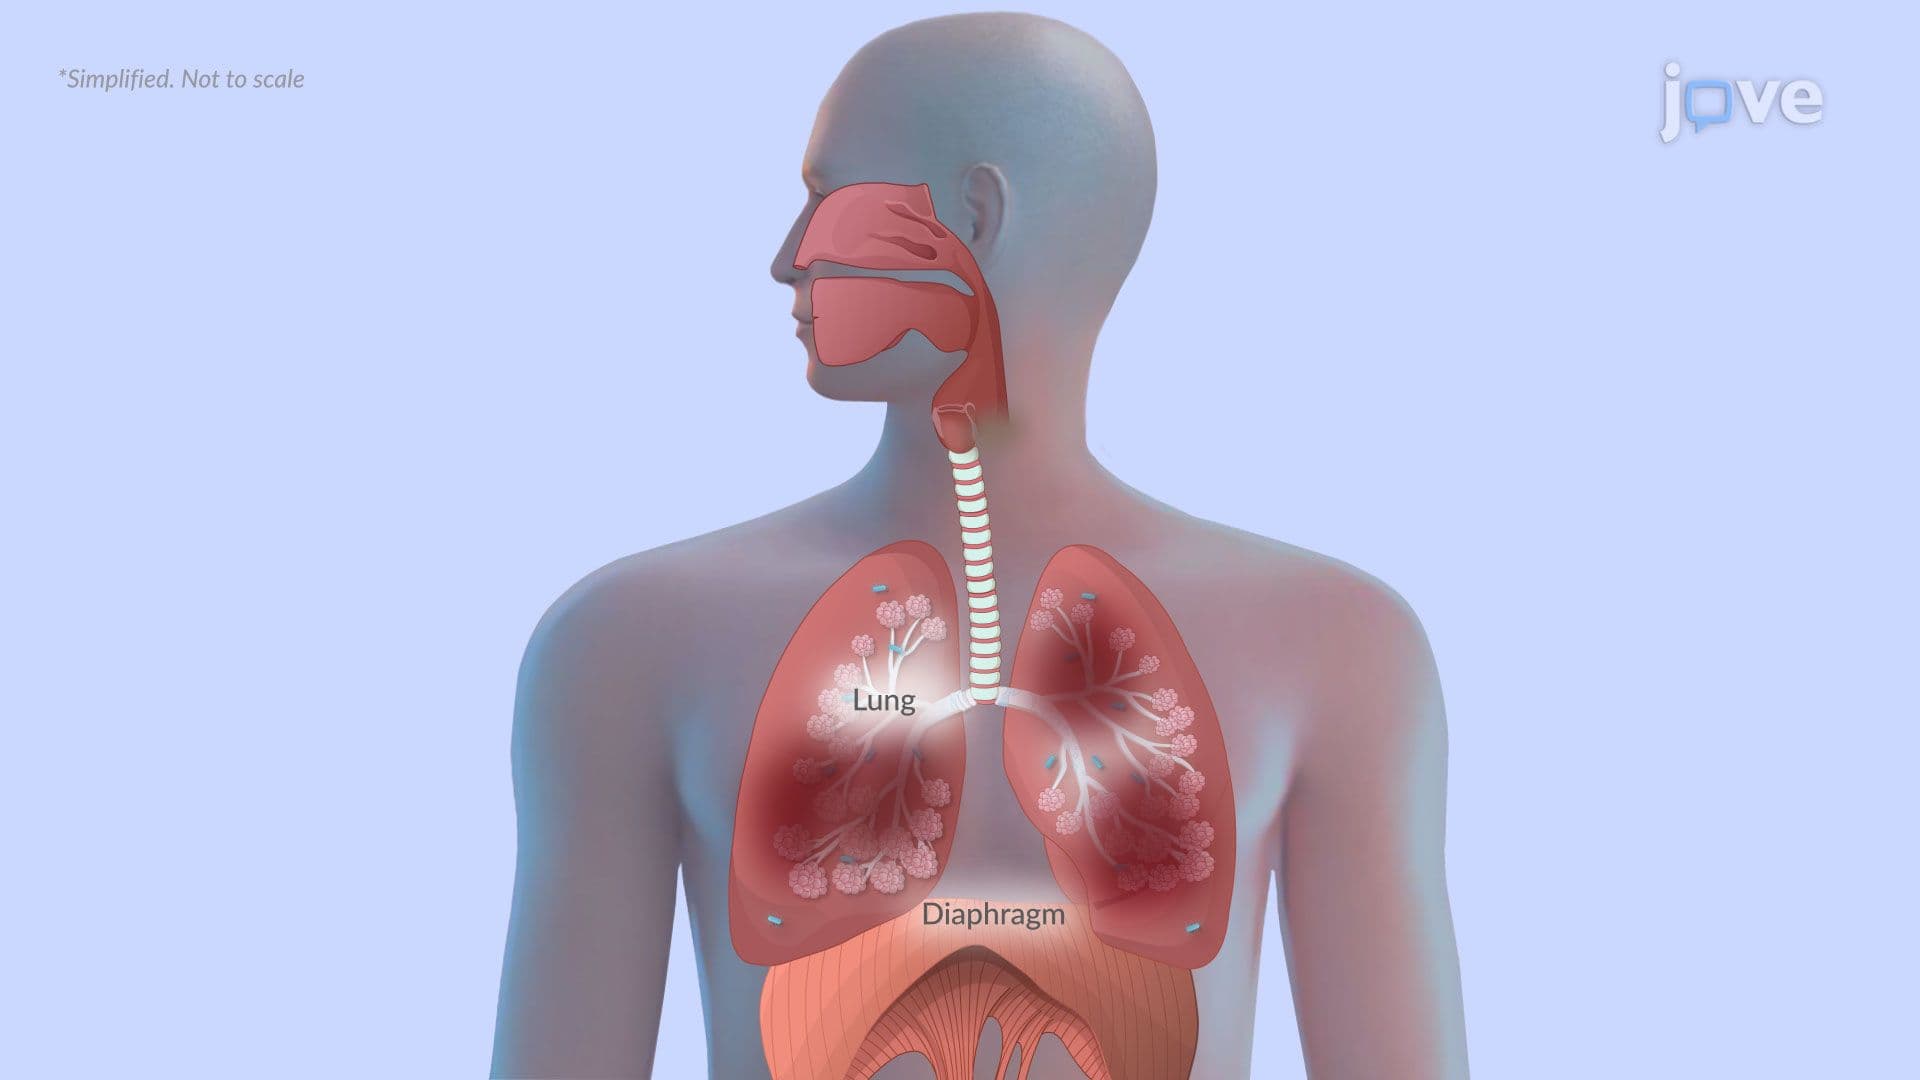 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features