Related Experiment Video
Updated: Aug 5, 2026
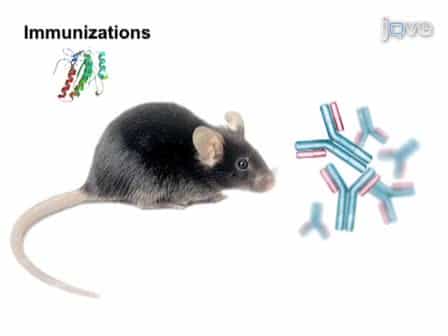

Passive Administration of Monoclonal Antibodies Against H. capsulatum and Others Fungal Pathogens
Published on: February 14, 2011
Long-term parenteral exposure to mercury in patients with hypogammaglobulinaemia

Patients with hypogammaglobulinaemia commonly receive regular long-term replacement therapy with a concentrate of pooled normal human immunoglobulin G (IgG) containing an organic mercury compound (thiomersal) as a preservative. In 26 such patients the total estimated mercury dosage received ranged from 4 to 734 mg (mean 157 mg) over treatment periods of six months to 17 years (mean 6.5 years). Nineteen patients (73%) had raised urine mercury concentrations, but no correlation was found between urine mercury and the age of the patient, the IgG dose, or the duration of treatment. Urine mercury concentrations are often used to control exposure and evaluate risks in exposed subjects. Hence most patients with hypogammaglobulinaemia are theoretically at risk from mercury exposure, although no clinical evidence of toxicity is yet apparent.
Patients with hypogammaglobulinaemia commonly receive regular long-term replacement therapy with a concentrate of pooled normal human immunoglobulin G (IgG) containing an organic mercury compound (thiomersal) as a preservative. In 26 such patients the total estimated mercury dosage received ranged from 4 to 734 mg (mean 157 mg) over treatment periods of six months to 17 years (mean 6.5 years). Nineteen patients (73%) had raised urine mercury concentrations, but no correlation was found between urine mercury and the age of the patient, the IgG dose, or the duration of treatment. Urine mercury concentrations are often used to control exposure and evaluate risks in exposed subjects. Hence most patients with hypogammaglobulinaemia are theoretically at risk from mercury exposure, although no clinical evidence of toxicity is yet apparent.
Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
 01:17
Transmission-based Precautions I: Contact, Enteric, and Droplets
Contact Precautions:
Contact precautions are the measures taken to prevent the transmission of infectious agents, especially epidemiologically important microorganisms such as MRSA or influenza, primarily transmitted through direct or indirect contact with an...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...