Related Experiment Video
Updated: Aug 25, 2026


Measurement of Factor V Activity in Human Plasma Using a Microplate Coagulation Assay
Published on: September 9, 2012
Fibrinogen clearance from the pulmonary interstitium

Previous experiments demonstrated that 125I-human fibrinogen (125-RIF) instilled into the distal airway of the right lower lobe in intact dogs passed through the microairway into the interstitium. This report analyzed the subsequent interstitial clearance of this fibrinogen by analyzing plasma and lymph samples for 125I activity. This activity was separated into clottable, and trichloroacetic acid (TCA) insoluble and soluble components. Clottable and TCA-insoluble 125-RIF in the same ratio appeared in lymph from the right lymphatic duct (RD) and thoracic duct (TD). From standard mixing equations we calculate that 1.4 times as much lymph from the right lower lobe flows into the TD as into the RD. With one exception, clottable 125-RIF appeared in plasma only in the absence of an RD; this suggested the presence of accessory lymphatico-venous communications rather than back flux of 125-RIF at the capillary wall. By injecting 131I-human fibrinogen intravenously, we observed a small reduction in clottability (maximum of 10%) in lymph both from the RD and TD. Equilibration in RD lymph was only 1/5 as fast as albumin, and from the measured equilibration rate constant, and the assumption that interstitial fibrinogen clearance is entirely convective, we estimate that the pulmonary interstitial distribution volume for fibrinogen is 70% that for albumin. Non dialyzable 125-RIF products generated in the distal airway adhered to intracapillary, circulating erythrocytes. These products retained fibrinogen antigenicity, and appeared to be further degraded in the vascular compartment.
Previous experiments demonstrated that 125I-human fibrinogen (125-RIF) instilled into the distal airway of the right lower lobe in intact dogs passed through the microairway into the interstitium. This report analyzed the subsequent interstitial clearance of this fibrinogen by analyzing plasma and lymph samples for 125I activity. This activity was separated into clottable, and trichloroacetic acid (TCA) insoluble and soluble components. Clottable and TCA-insoluble 125-RIF in the same ratio appeared in lymph from the right lymphatic duct (RD) and thoracic duct (TD). From standard mixing equations we calculate that 1.4 times as much lymph from the right lower lobe flows into the TD as into the RD. With one exception, clottable 125-RIF appeared in plasma only in the absence of an RD; this suggested the presence of accessory lymphatico-venous communications rather than back flux of 125-RIF at the capillary wall. By injecting 131I-human fibrinogen intravenously, we observed a small reduction in clottability (maximum of 10%) in lymph both from the RD and TD. Equilibration in RD lymph was only 1/5 as fast as albumin, and from the measured equilibration rate constant, and the assumption that interstitial fibrinogen clearance is entirely convective, we estimate that the pulmonary interstitial distribution volume for fibrinogen is 70% that for albumin. Non dialyzable 125-RIF products generated in the distal airway adhered to intracapillary, circulating erythrocytes. These products retained fibrinogen antigenicity, and appeared to be further degraded in the vascular compartment.


Related Concept Videos
 01:29
Drug Distribution: Plasma Protein Binding
 01:06
Drug Elimination: The Concept of Clearance
Drug clearance is not limited to renal excretion but encompasses all organs involved in drug elimination,...
 01:16
Clot Retraction and Fibrinolysis
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:09
Hepatic Drug Clearance: Restrictive and Nonrestrictive Clearance
Most drugs undergo restrictive clearance, which is proportional to the...
 01:09
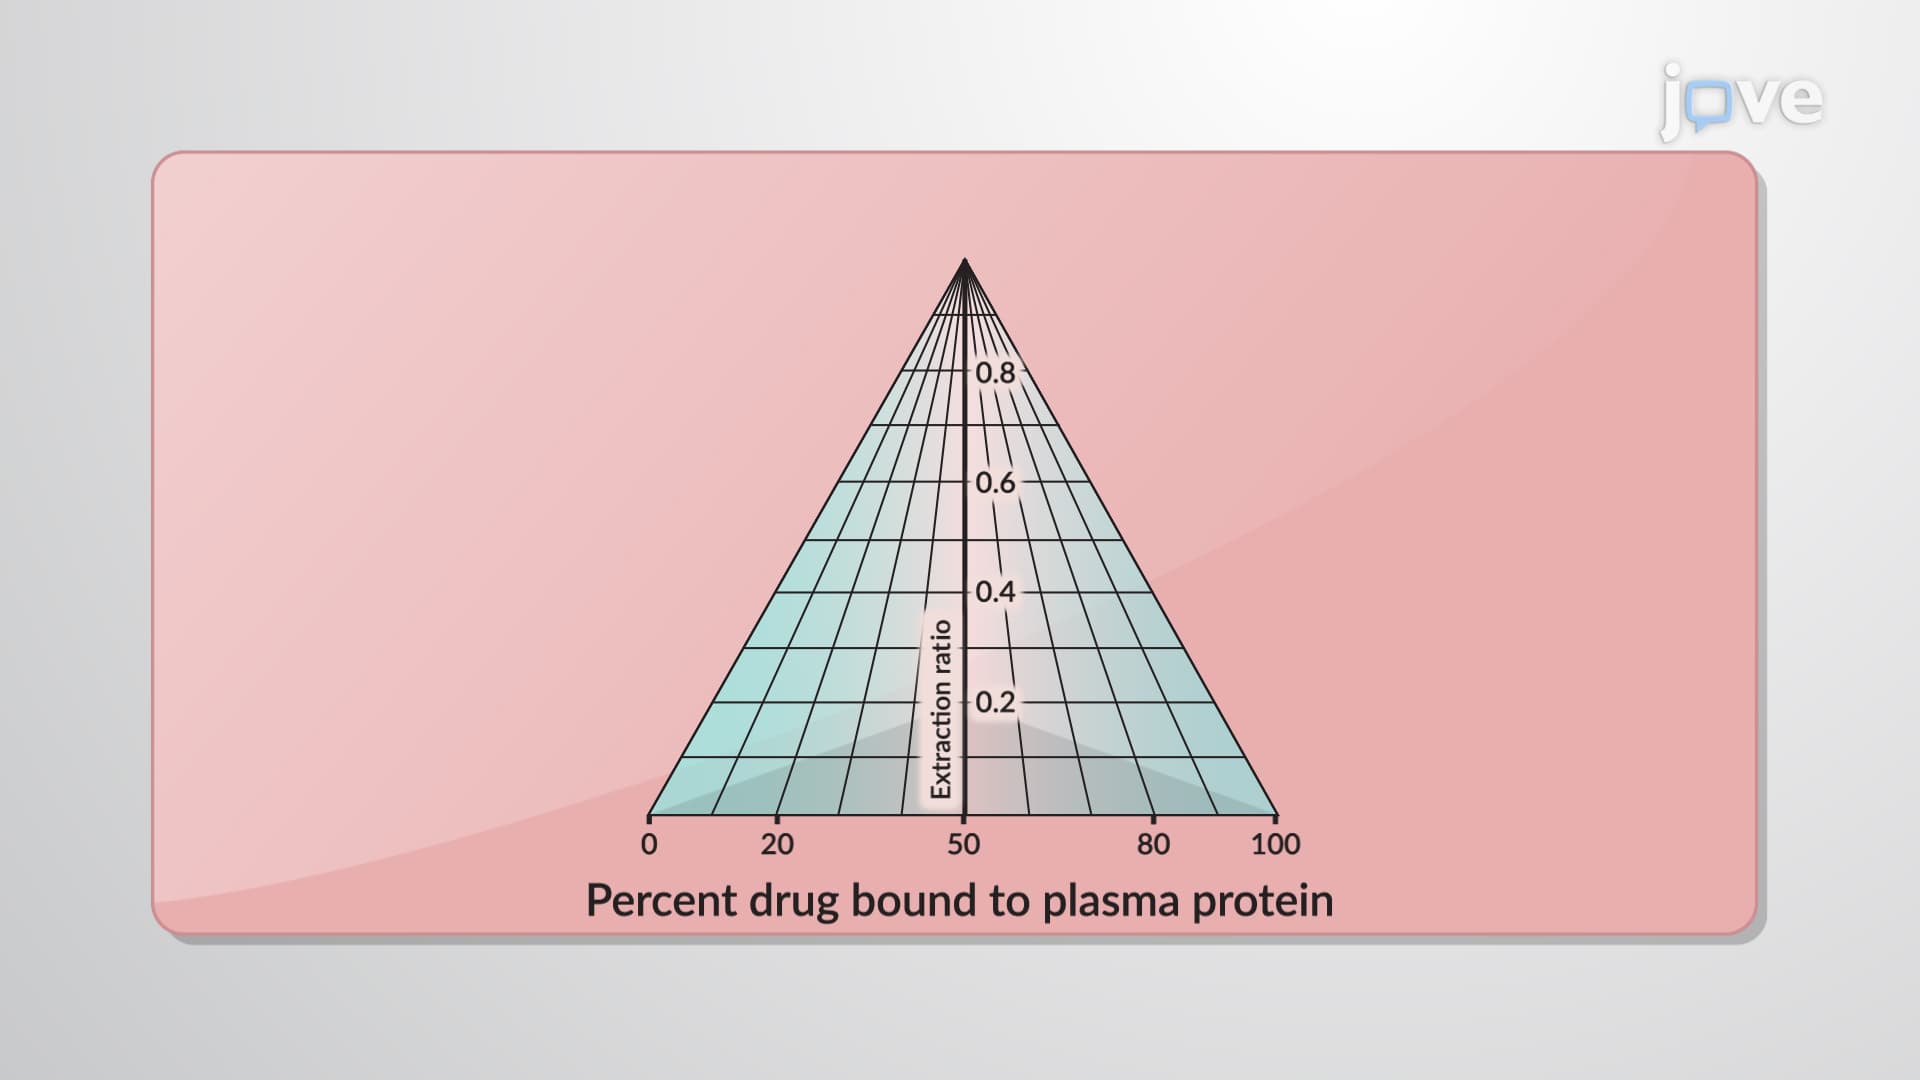
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...