Related Experiment Video
Updated: Aug 12, 2026
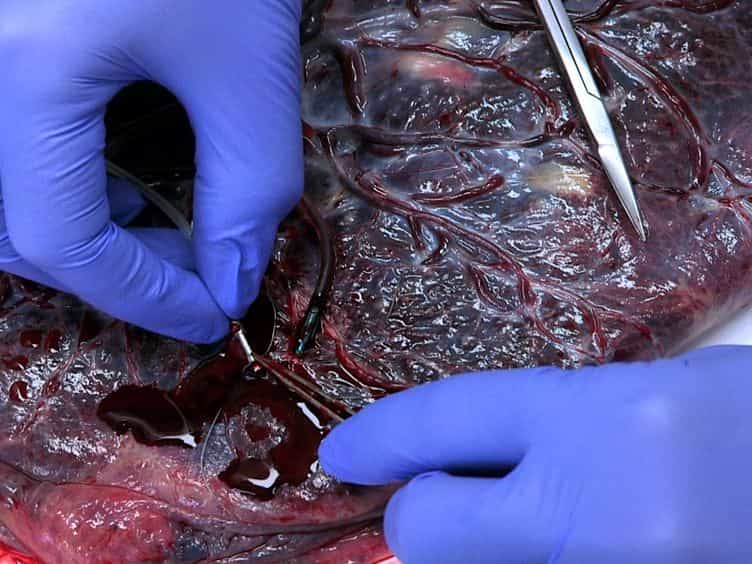

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Placental transfer of lead and its effects on the newborn

Following delivery, blood was taken from 122 mothers and their infants' cords for estimation of lead, haemoglobin, packed cell volume and mean corpuscular haemoglobin concentration. All were resident in Kasanda, a township within a radius of 3000 metres of Brokin Hill Lead Mine and Smelter, Zambia, where the annual mean atmospheric lead concentration was 9.6 microgram/m3 and the soil lead concentration 100-9400 p.p.m. Their mean blood levels were high, being 41.2 microgram and 37 microgram/dl for mothers and infants respectively, with a significant correlation (r = 0.77, P less than 0.001). Thus an infant's blood lead at birth closely follows that of its mother even at high values. The increased lead level transfer, however, did not appear adversely to affect the birth weight or red cell values of the newborn. Cord blood lead levels are being used in Broken Hill to monitor a community's exposure to lead.
Following delivery, blood was taken from 122 mothers and their infants' cords for estimation of lead, haemoglobin, packed cell volume and mean corpuscular haemoglobin concentration. All were resident in Kasanda, a township within a radius of 3000 metres of Brokin Hill Lead Mine and Smelter, Zambia, where the annual mean atmospheric lead concentration was 9.6 microgram/m3 and the soil lead concentration 100-9400 p.p.m. Their mean blood levels were high, being 41.2 microgram and 37 microgram/dl for mothers and infants respectively, with a significant correlation (r = 0.77, P less than 0.001). Thus an infant's blood lead at birth closely follows that of its mother even at high values. The increased lead level transfer, however, did not appear adversely to affect the birth weight or red cell values of the newborn. Cord blood lead levels are being used in Broken Hill to monitor a community's exposure to lead.
More Related Videos


Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:07
Teratogenicity
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism