Spinal cord compression in thalassaemia

Two cases of spinal cord compression resulting from extramedullary haemopoiesis in patients with thalassaemia of intermediate clinical severity are reported. The association between mild thalassaemia with long survival and the risk of spinal cord compression from extramedullary haemopoietic deposits is emphasised.
Related Concept Videos

The Spinal Cord01:54

The Spinal Cord

The spinal cord is the body’s major nerve tract of the central nervous system, communicating afferent sensory information from the periphery to the brain and efferent motor information from the brain to the body. The human spinal cord extends from the hole at the base of the skull, or foramen magnum, to the level of the first or second lumbar vertebra.
Spinal Cord: Cross-sectional Anatomy01:16

Spinal Cord: Cross-sectional Anatomy

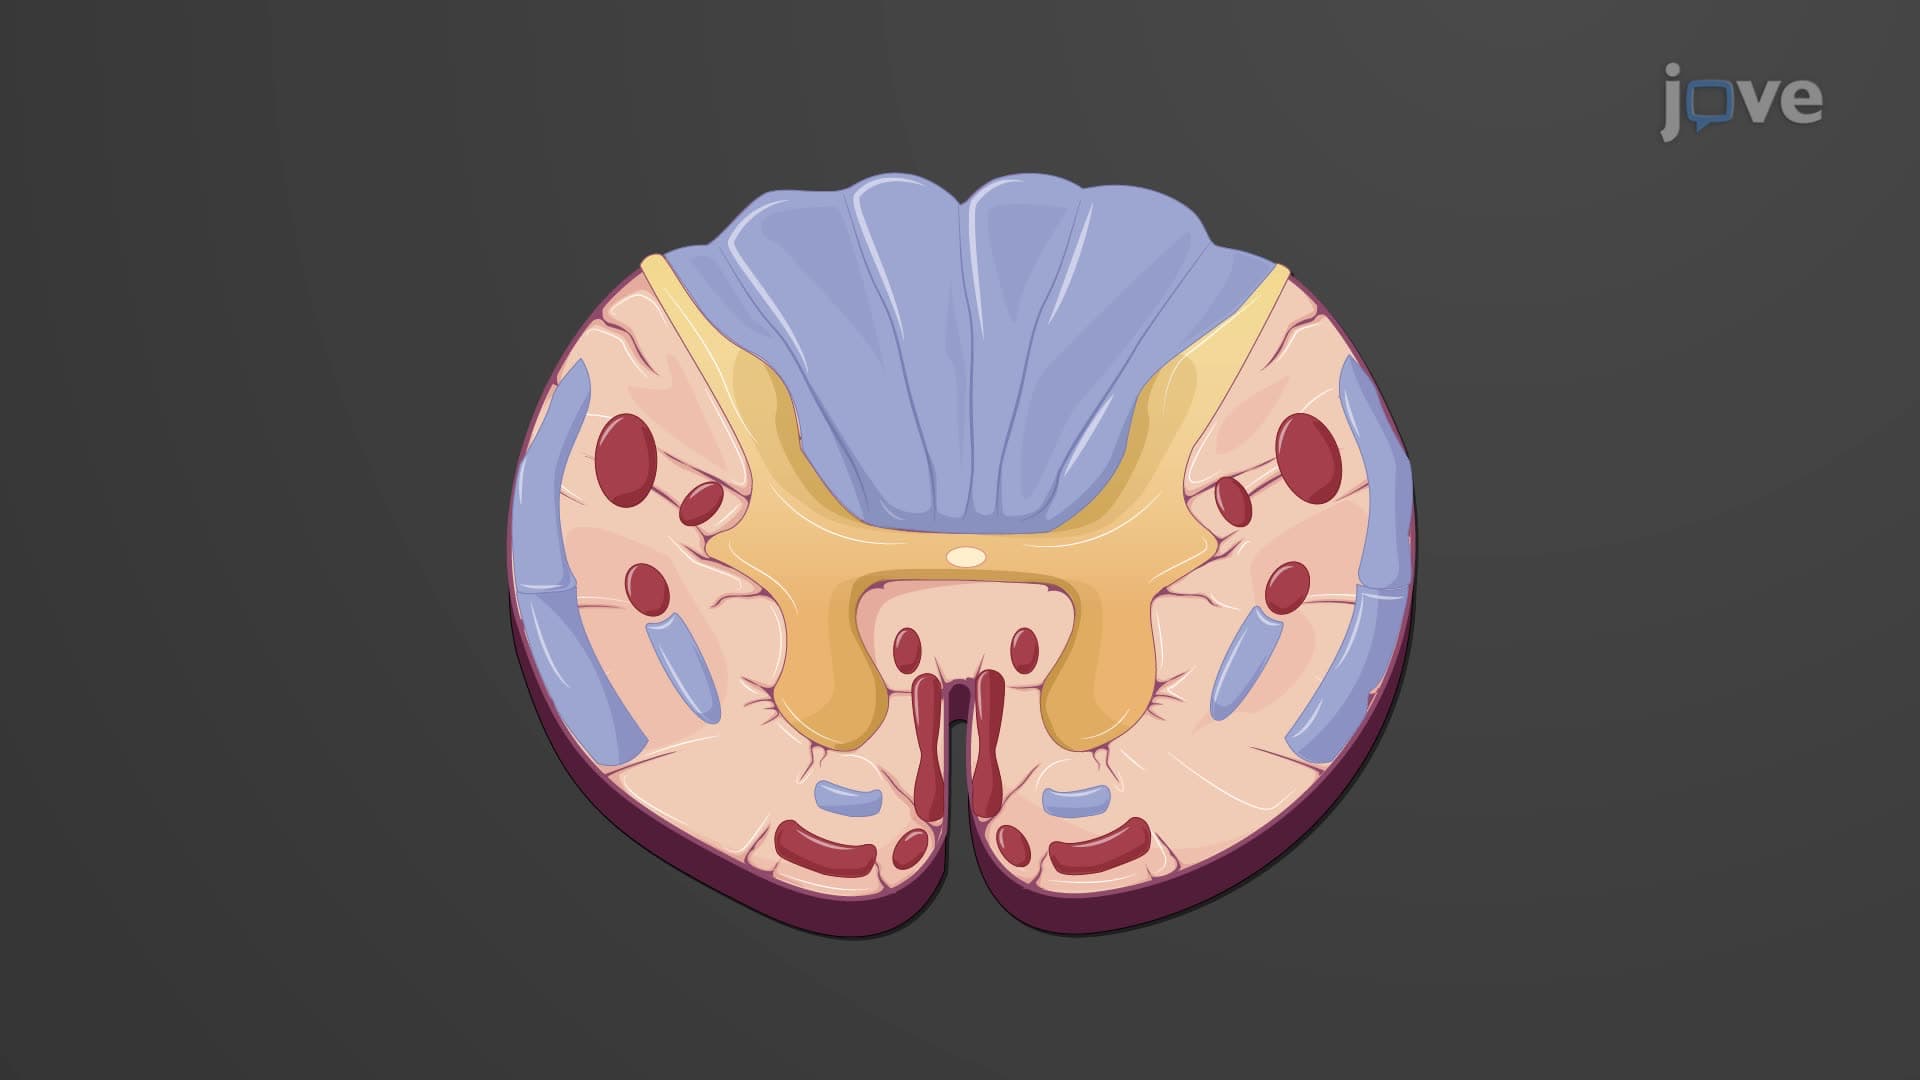
The cross-sectional anatomy of the spinal cord offers a detailed view of its complex structure and function within the central nervous system. At the core of the spinal cord lies the gray matter, characterized by its butterfly or "H"-shaped appearance in cross-section. This central region is enveloped by white matter, with the overall structure divided into symmetrical halves by the dorsal median sulcus and the ventral median fissure.
Gray Matter and its Components
Central to the gray matter is...
Thoracic Aorta01:15

Thoracic Aorta

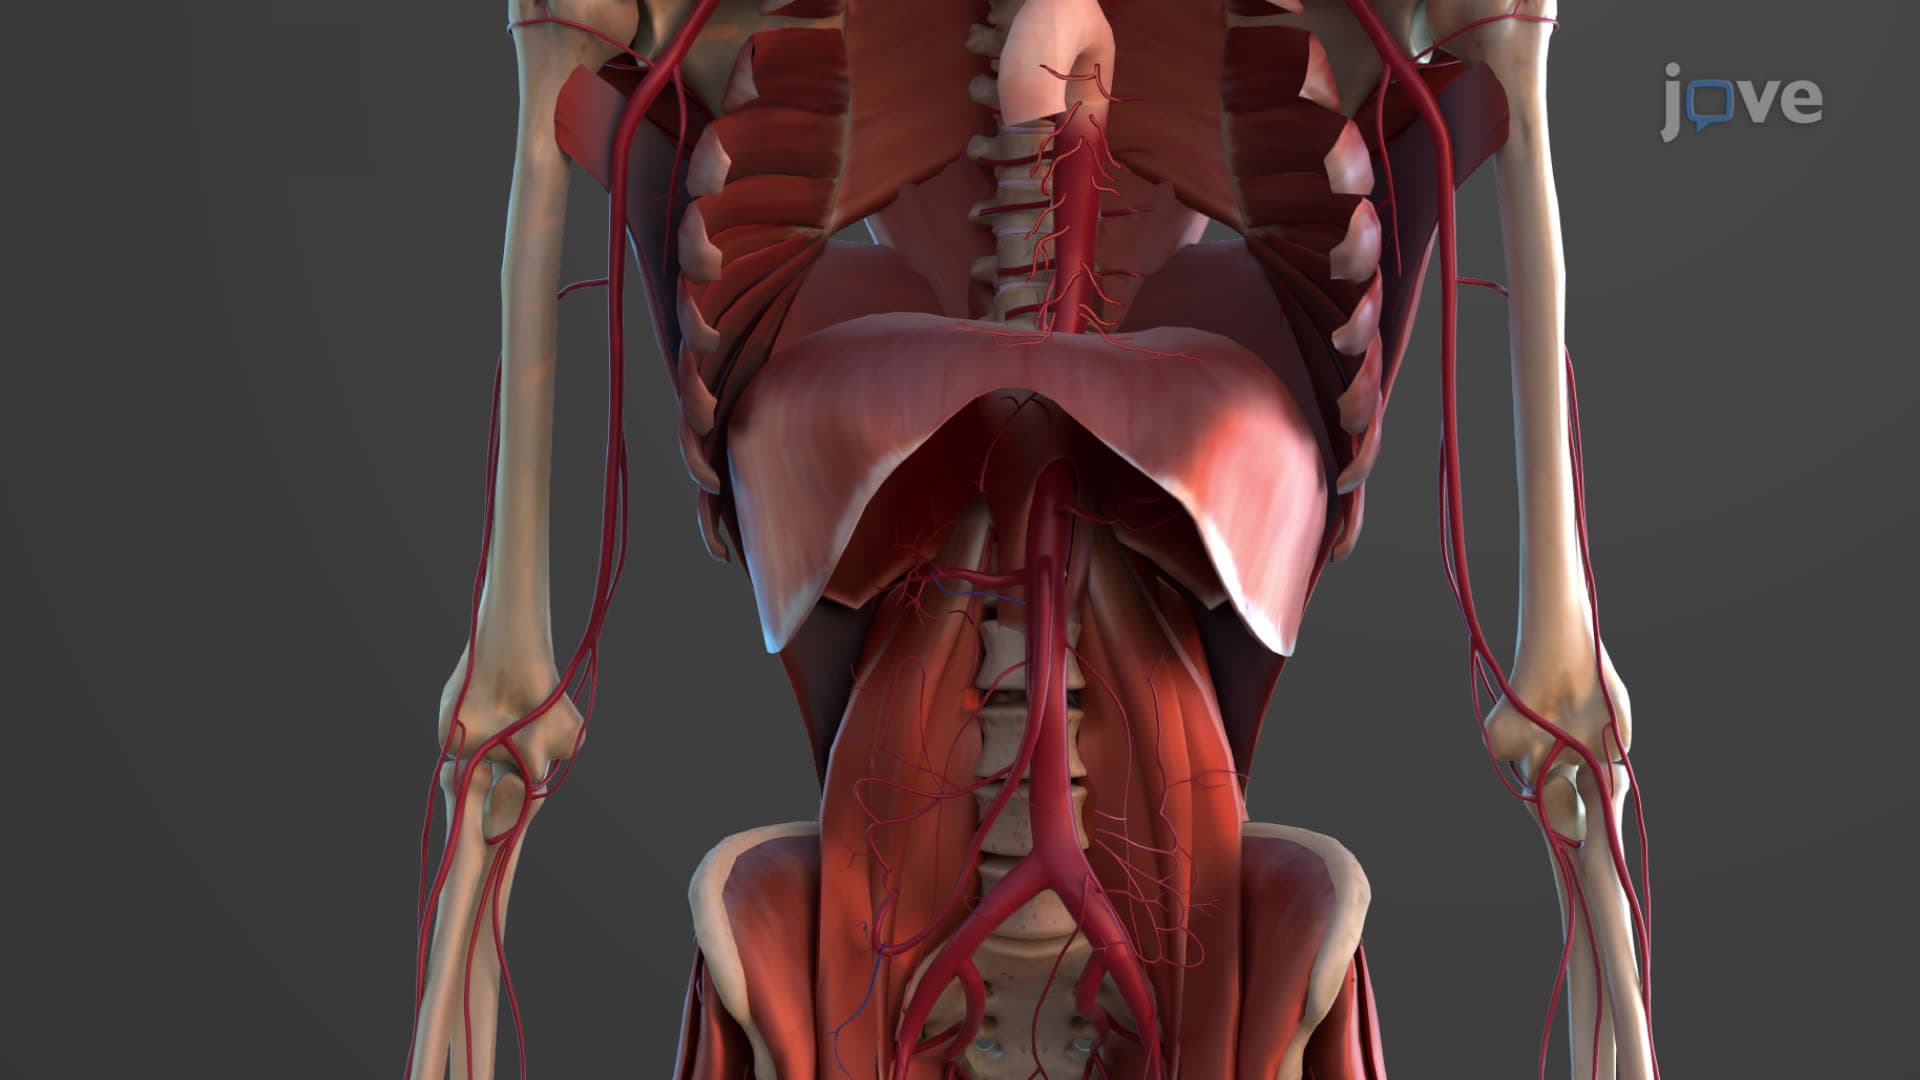
The thoracic section of the aorta begins at the T5 vertebra and extends to the T12 level at the diaphragm, initially progressing through the mediastinum to the left of the spinal column. Throughout its course in the thoracic segment, the thoracic aorta emits various offshoots known collectively as visceral and parietal branches. The branches that predominantly supply blood to visceral organs are termed visceral branches and include bronchial, pericardial, esophageal, and mediastinal arteries,...
Hemorrhagic Stroke ll: Pathophysiology01:29

Hemorrhagic Stroke ll: Pathophysiology
A hemorrhagic stroke develops when a cerebral blood vessel ruptures, allowing blood to escape into the surrounding brain tissue, as in intracerebral hemorrhage (ICH), or into the subarachnoid space, as in subarachnoid hemorrhage (SAH). Because the skull is a rigid compartment, the sudden presence of extravascular blood rapidly increases intracranial pressure and compresses adjacent neural structures, leading to immediate tissue injury and impaired cerebral perfusion.Mass Effect and Primary...
Spinal Cord Injury ll: Pathophysiology01:14

Spinal Cord Injury ll: Pathophysiology

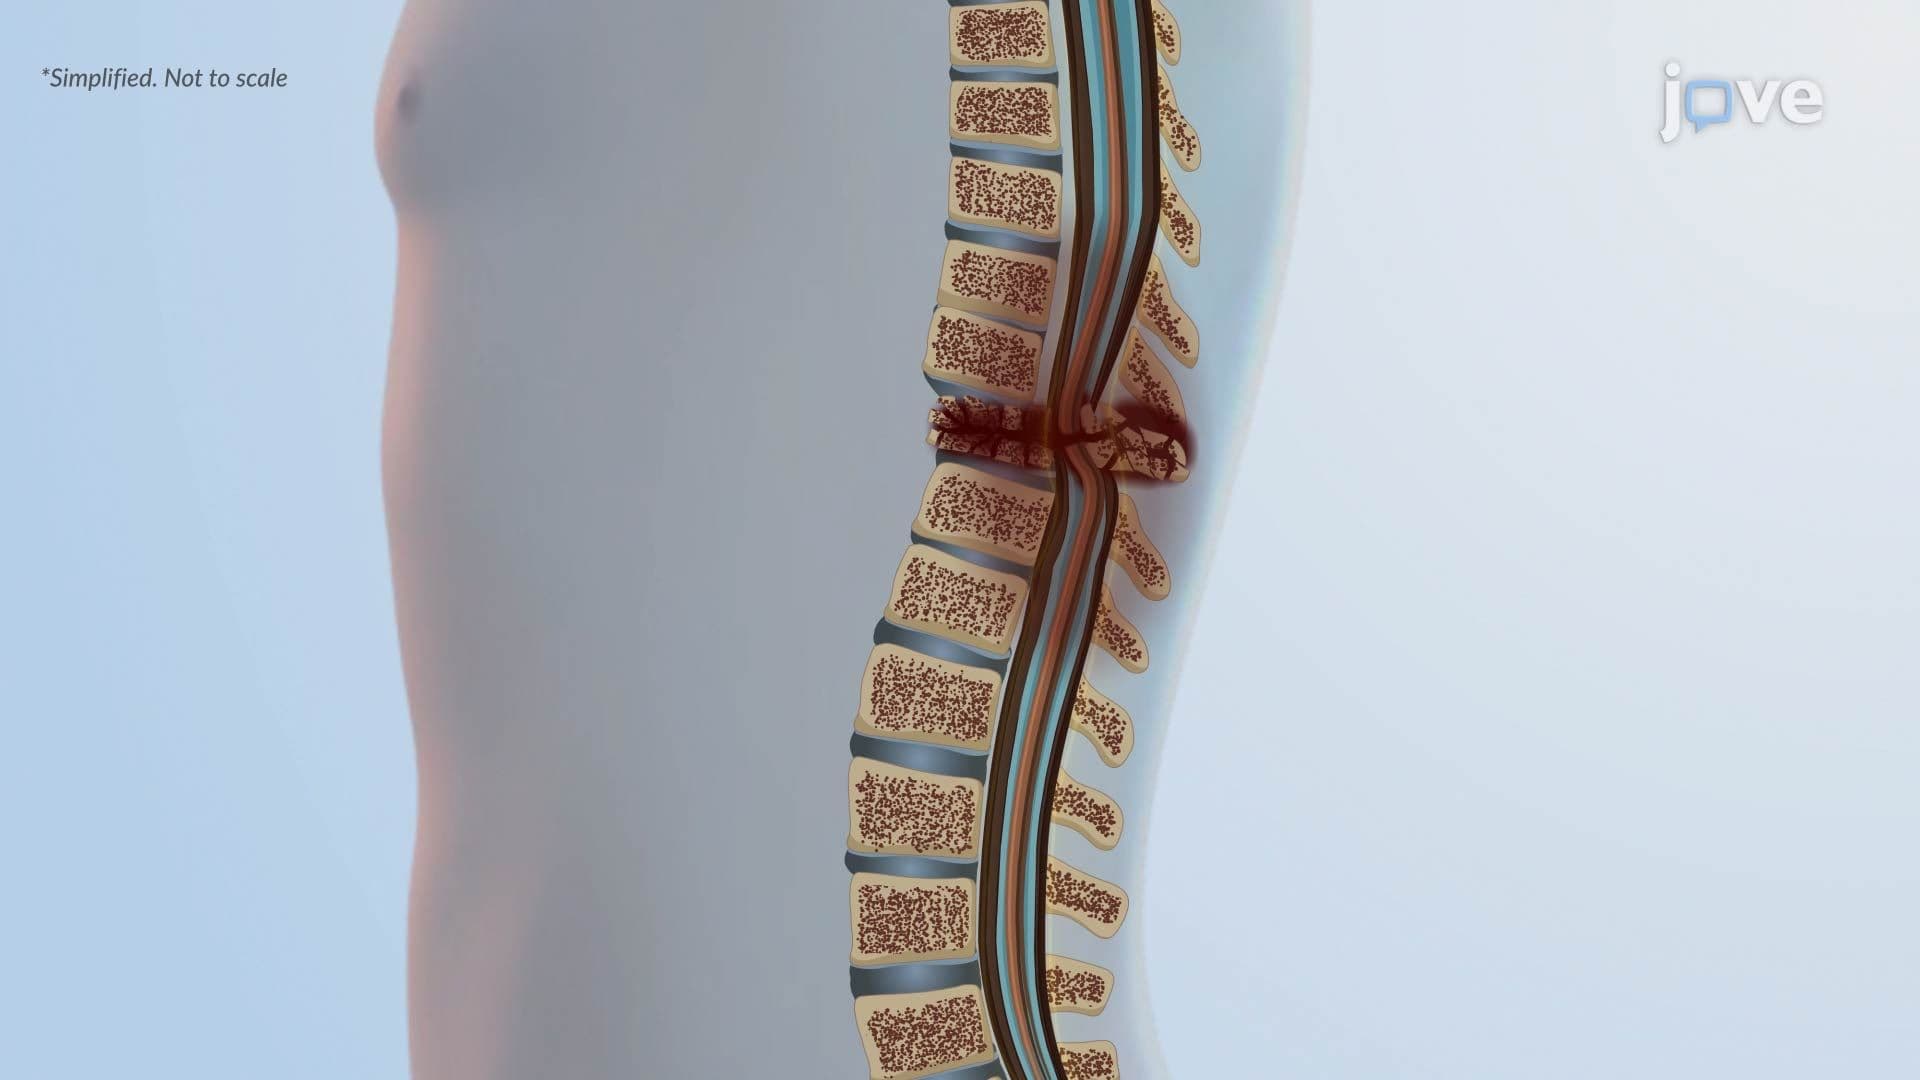
Spinal cord injury progresses through two interconnected phases: primary injury and secondary injury.Primary InjuryPrimary injury happens at the moment of trauma and involves immediate mechanical damage to the spinal cord.Compression happens when broken vertebrae, herniated discs, or accumulating blood (such as a hematoma) press directly against the spinal cord, distorting its normal shape and function. In cases of contusion, the cord is bruised by a blunt force (like penetrating injuries or...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...