Related Experiment Video
Updated: Aug 6, 2026

Biochemical Measurement of Neonatal Hypoxia
Published on: August 24, 2011
Excretion of cyclic 3',5'-adenosine monophosphate in the early newborn period

Insights
Urinary cyclic 3',5'-adenosine monophosphate (cAMP) excretion in newborns is linked to kidney function and gestational age. Higher cAMP levels correlate with better glomerular filtration and longer gestation periods.
Area of Science:
- Neonatal physiology
- Renal function in infants
- Biochemical markers in newborns
Background:
- Cyclic 3",5"-adenosine monophosphate (cAMP) plays a crucial role in cellular signaling.
- Understanding neonatal renal function is vital for assessing infant health.
- Establishing baseline biochemical parameters in newborns aids in early detection of potential issues.
Purpose of the Study:
- To investigate the relationship between urinary cyclic 3',5'-adenosine monophosphate (cAMP) excretion and key renal function indicators in neonates.
- To determine if urinary cAMP levels correlate with creatinine clearance, urinary phosphate excretion, or urine osmolarity in early life.
- To assess the influence of gestational age on urinary cAMP excretion in newborns.
Main Methods:
- Studied 29 infants aged 28-40 weeks gestation during the first few days of life.
- Measured urinary cyclic 3',5'-adenosine monophosphate (cAMP) excretion under basal conditions.
- Assessed urinary cAMP in relation to creatinine clearance, urinary phosphate excretion, and urine osmolarity.
Main Results:
- A direct and significant correlation was found between urinary cAMP excretion and creatinine clearance (r = 0.89, P < 0.001).
- Urinary cAMP excretion also showed a significant positive relationship with gestational age (r = 0.63, P < 0.001).
- No significant relationship was observed between urinary cAMP excretion and urinary phosphate excretion or urine osmolarity.
Conclusions:
- Urinary cyclic 3',5'-adenosine monophosphate (cAMP) excretion in neonates is primarily dependent on the glomerular filtration rate.
- Gestational age is a significant factor influencing urinary cAMP excretion levels in newborns.
- These findings provide insights into the maturation of renal function and cAMP handling in the neonatal period.
Abstract:
The relationship between cyclic 3',5'-adenosine monophosphate (cAMP) excretion and creatinine clearance, urinary phosphate excretion, and urinary osmolarity was studied under basal conditions in 29 babies of 28-40 weeks gestation, during the first few days of life. Urinary cAMP excretion was directly related to creatinine clearance, r = 0.89, P less than 0.001, and gestational age, r = 0.63, P less than 0.001. There was no relationship between urinary cAMP excretion and urinary phosphate excretion or urine osmolarity. These results indicate that urinary cAMP excretion is dependent on the rate of glomerular filtration and gestational age.

Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:09
GPCRs Regulate Adenylyl Cylase Activity
Two...
 01:22
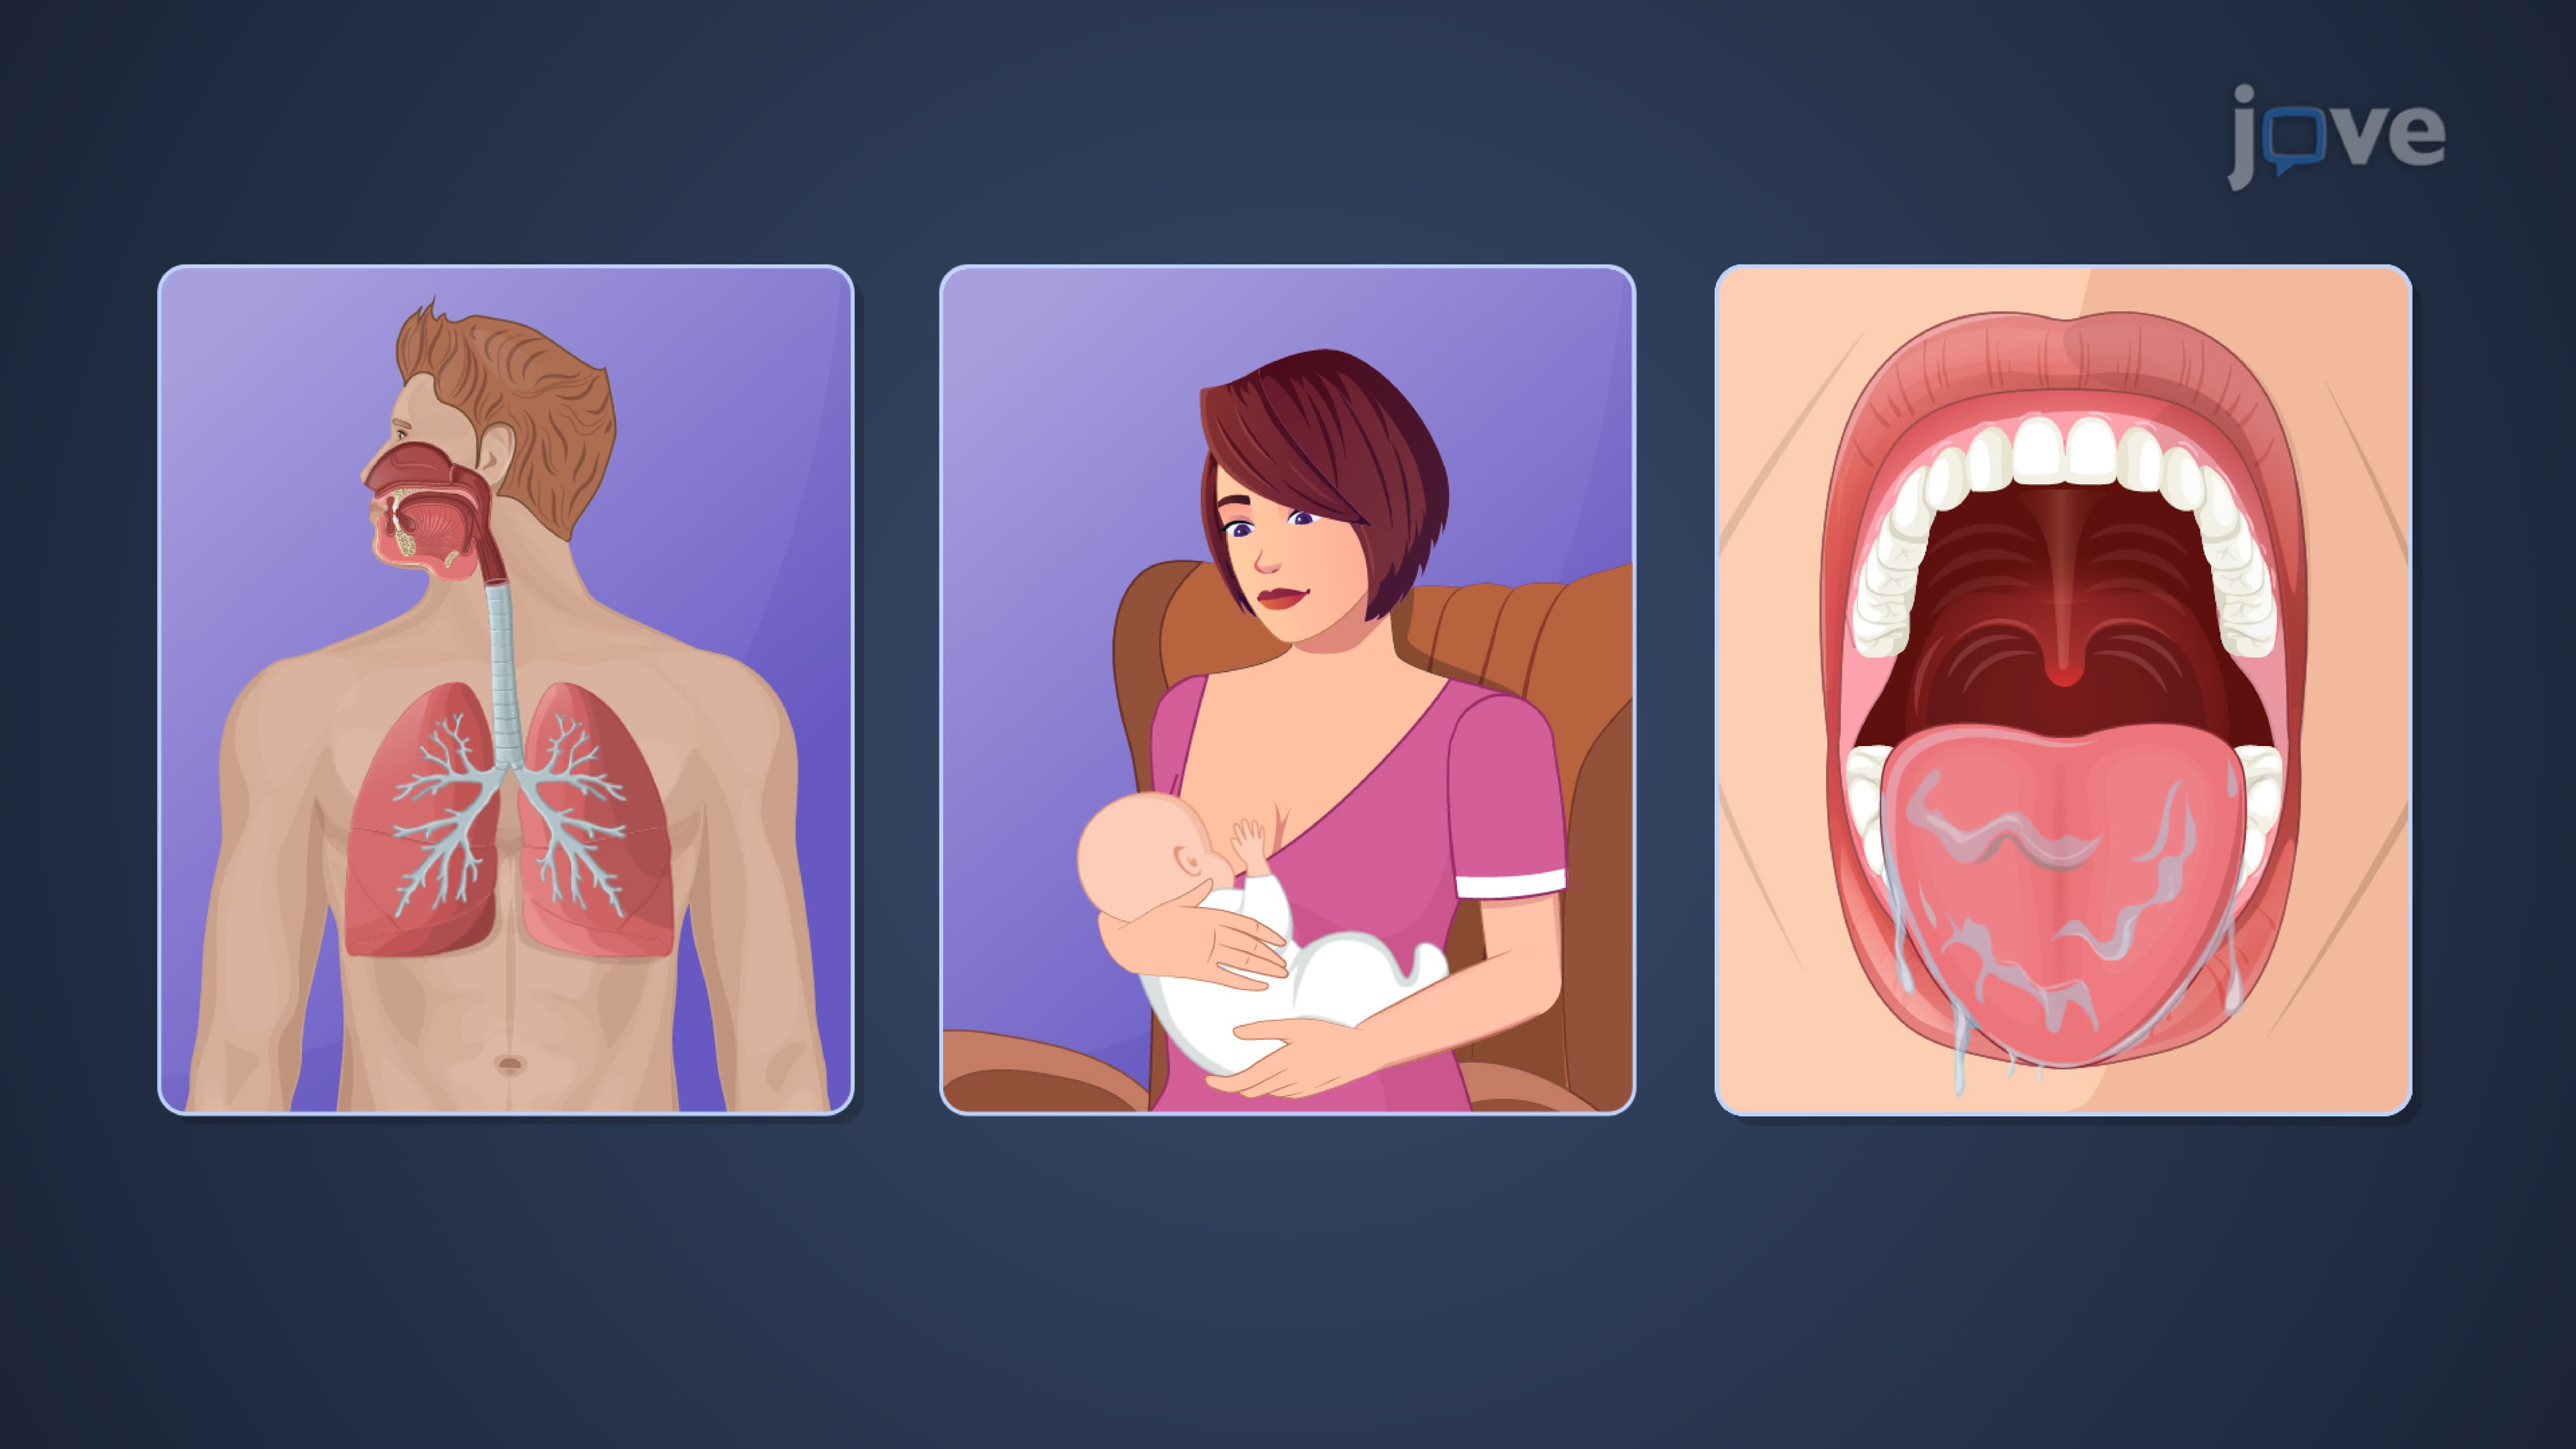
Drug Excretion: Pulmonary and Glandular Routes
Drugs can also be excreted in breast milk, which is crucial for breastfeeding infants. The process...
 01:10
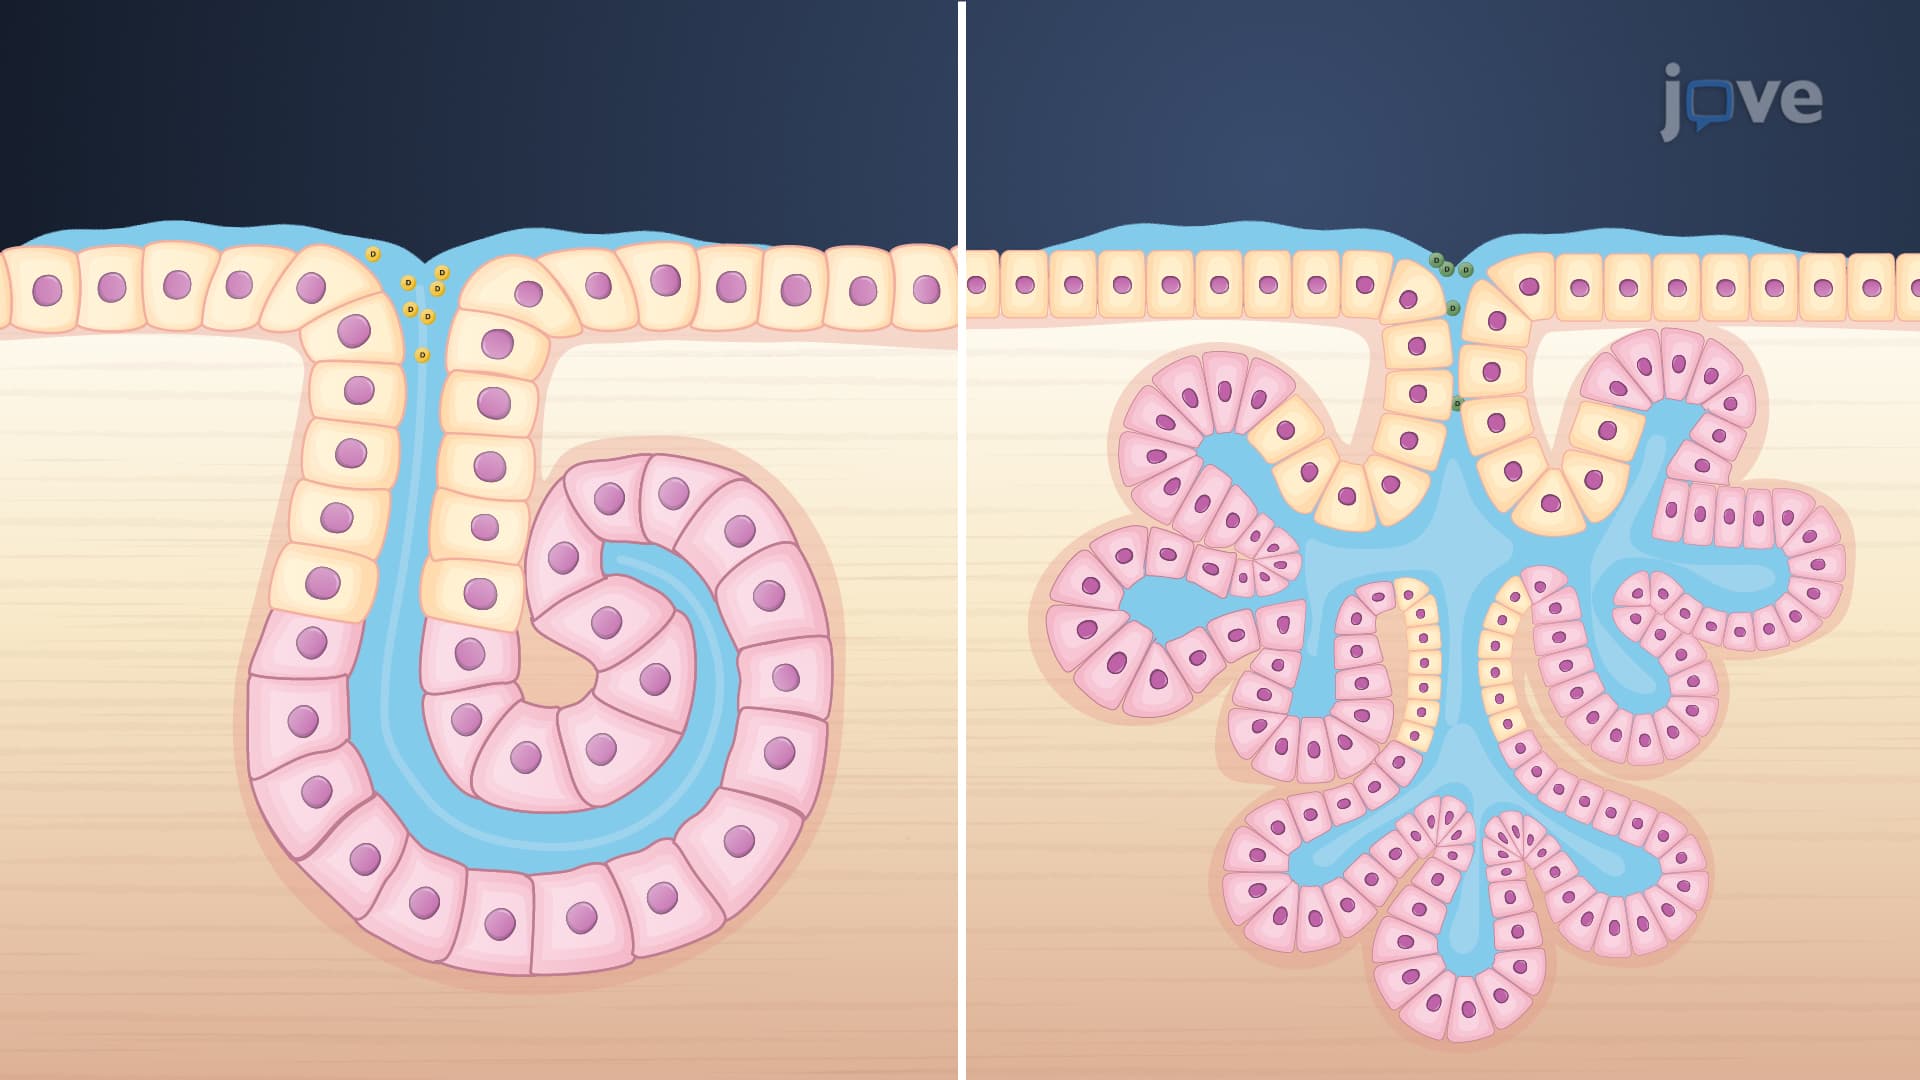
Drug Excretion: Miscellaneous Routes
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion