Related Experiment Video
Updated: Oct 23, 2026
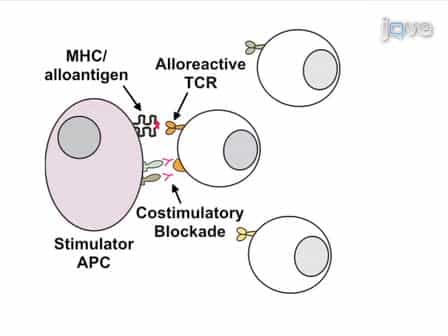
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Abnormal indomethacin-sensitive suppression in peripheral blood mononuclear cells of cancer patients restricts

The capacity of the immunomodulators interleukin-2 (IL-2) and indomethacin to augment phytohemagglutinin (PHA)-induced lymphoproliferation in the peripheral blood mononuclear cells (PBMC) of cancer patients was evaluated. Ficoll-Hypaque-isolated PBMC from 20 patients with disseminated non-lymphoreticular solid tumors were stimulated with PHA in the presence of IL-2, indomethacin, or IL-2 plus indomethacin. Augmentation of PHA responsiveness by each immunomodulator was additive. There was a significant negative correlation between PHA reactivity and immunomodulation by indomethacin. There was no correlation between PHA reactivity and immunomodulation by IL-2. A significant negative correlation was also found between indomethacin-induced augmentation and IL-2-induced augmentation in patients with significantly impaired reactivity to PHA. Still, the combined effects of IL-2 and indomethacin could not prevent the suppressive effects of prostaglandin E2 added to PHA-stimulated cultures containing both immunomodulators. These results suggest that the presence of abnormal indomethacin-sensitive immunoregulation in PBMC from cancer patients limits lymphocyte responsiveness to IL-2 and suggests that these two immunomodulators might be combined in certain cancer patient therapies.
The capacity of the immunomodulators interleukin-2 (IL-2) and indomethacin to augment phytohemagglutinin (PHA)-induced lymphoproliferation in the peripheral blood mononuclear cells (PBMC) of cancer patients was evaluated. Ficoll-Hypaque-isolated PBMC from 20 patients with disseminated non-lymphoreticular solid tumors were stimulated with PHA in the presence of IL-2, indomethacin, or IL-2 plus indomethacin. Augmentation of PHA responsiveness by each immunomodulator was additive. There was a significant negative correlation between PHA reactivity and immunomodulation by indomethacin. There was no correlation between PHA reactivity and immunomodulation by IL-2. A significant negative correlation was also found between indomethacin-induced augmentation and IL-2-induced augmentation in patients with significantly impaired reactivity to PHA. Still, the combined effects of IL-2 and indomethacin could not prevent the suppressive effects of prostaglandin E2 added to PHA-stimulated cultures containing both immunomodulators. These results suggest that the presence of abnormal indomethacin-sensitive immunoregulation in PBMC from cancer patients limits lymphocyte responsiveness to IL-2 and suggests that these two immunomodulators might be combined in certain cancer patient therapies.


Related Concept Videos
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:25
Inflammatory Bowel Disease III: Crohn's Disease