[Parathormone and renal excretion in healthy controls and patients with nephrolithiasis (author's transl)]

Klinische Wochenschrift
|February 1, 1980
PubMed

Related Concept Videos

Renal Drug Excretion: Overview01:15

Renal Drug Excretion: Overview

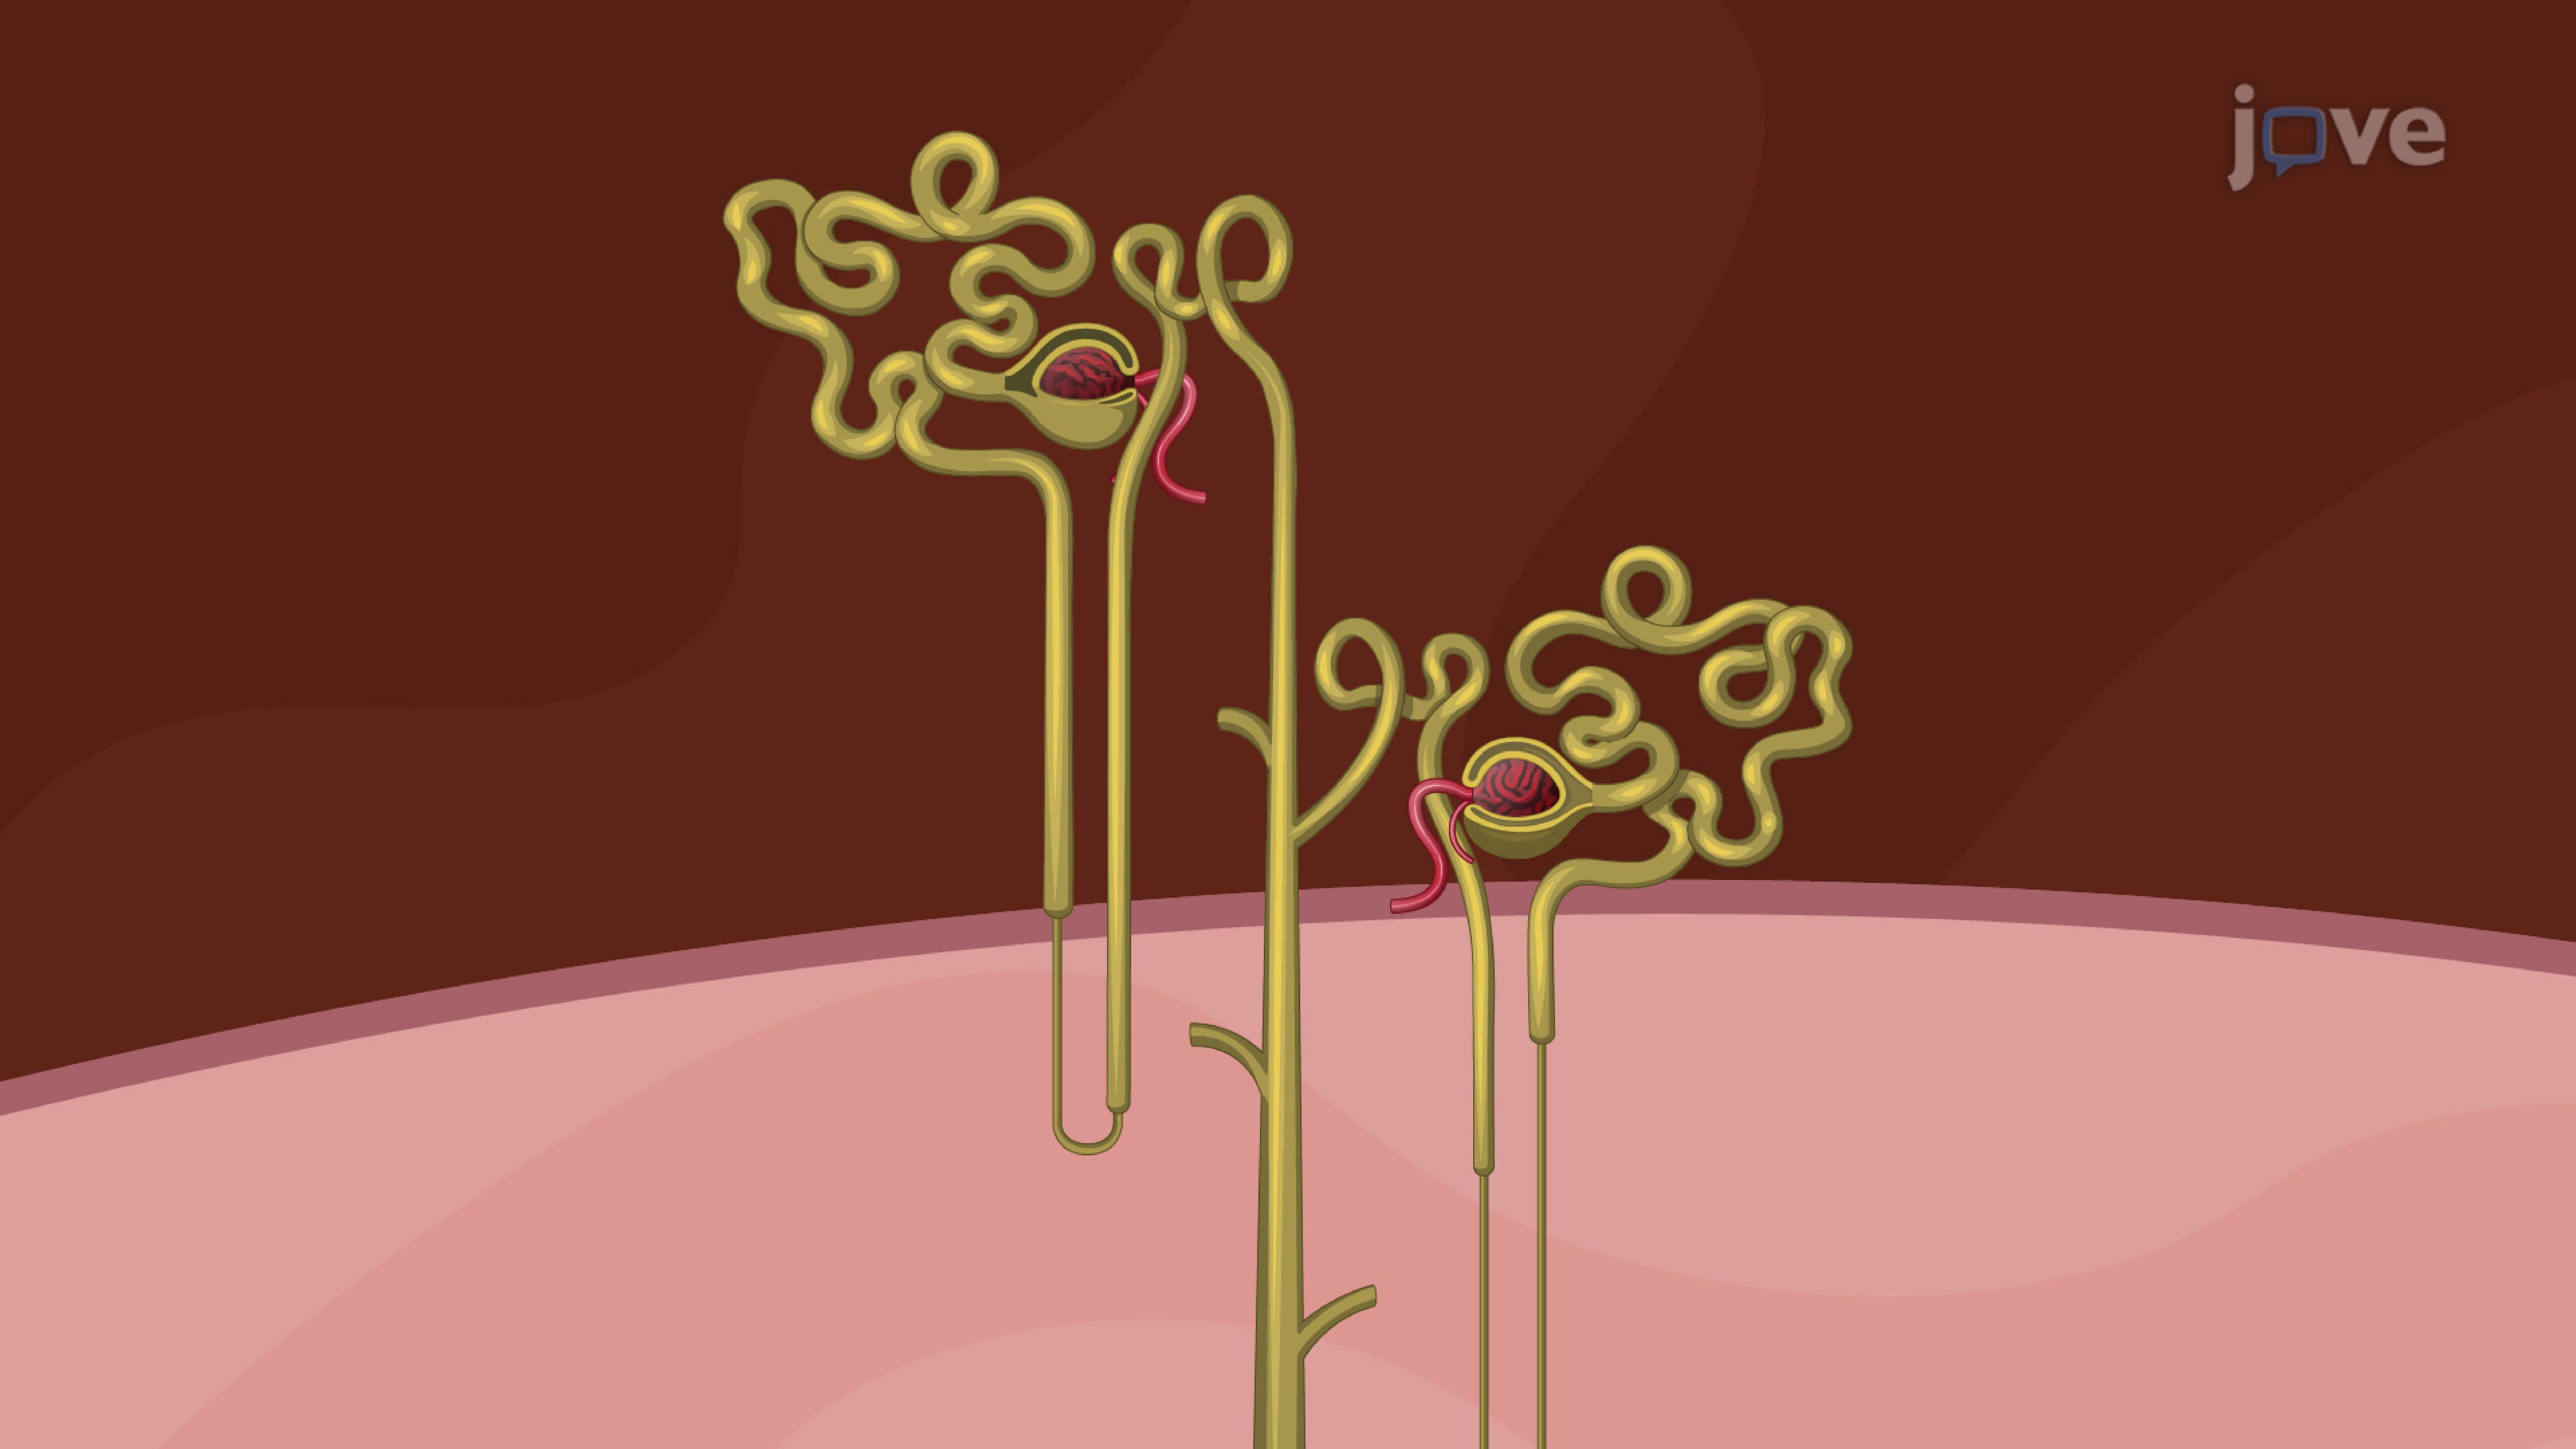
As primary excretory organs, the kidneys maintain homeostasis by removing waste substances from the bloodstream. They comprise over a million units called nephrons, which serve as the kidney's functional units.
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...

Renal Drug Excretion: Tubular Reabsorption01:25

Renal Drug Excretion: Tubular Reabsorption

Tubular reabsorption, a process occurring post-glomerular filtration of drugs in the renal tubule, is a critical determinant of drug half-life. During the process of renal excretion, as the glomerular filtrate progresses to the distal convoluted tubule (DCT), drugs that are highly permeable, lipophilic, and nonionized undergo passive reabsorption from the tubular fluid into the surrounding peritubular capillaries. This reabsorption process restricts their elimination through the kidneys. This...
Renal Drug Excretion: Tubular Secretion01:28

Renal Drug Excretion: Tubular Secretion
Active tubular secretion is a robust, energy-demanding process that utilizes carrier systems to transport drugs into renal tubules. The active renal secretion systems include the organic anion transporter (OAT) for weak acids and the organic cation transporter (OCT) for weak bases. Structurally similar drugs can compete for the same transporter, potentially leading to drug accumulation and toxicity. However, this principle can be exploited therapeutically. One example is probenecid (Probalan),...
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa01:22

Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa

The pH of urine, the drug's pKa, and the urine flow rate are vital parameters for drug reabsorption and excretion. Urinary pH varies between 4.6 and 8.0 and is influenced by diet, drug intake, and the patient's pathophysiology. It affects a drug's ionization state and reabsorption. For instance, carbohydrate-rich food produces alkaline urine promoting drug excretion, while proteins and certain medications like ascorbic acid lead to acidic urine enhancing reabsorption.
The pKa of a drug,...
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations01:26

Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations

Renal calculi, commonly termed kidney stones, are crystalline solid masses that form in the kidneys but can occur at any point within the urinary system, encompassing the kidneys, ureters, bladder, and urethra.The pathophysiology of renal stones involves several key factors: supersaturation of the urine with stone-forming constituents, changes in urine pH, a decrease in urine volume, and the presence of substances that promote or inhibit stone formation.Supersaturation of Urine: This is the...
Urinary Tract Calculi III: Medical Management01:30

Urinary Tract Calculi III: Medical Management

The diagnosis of renal calculi involves several imaging techniques, including non-contrast CT scans and ultrasound. These methods help visualize kidney stones, assess their size and location, and detect possible obstructions. Additionally, Measuring urine pH is useful for diagnosing specific stone types, such as struvite (alkaline pH) and uric acid stones (acidic pH). Cystine stones are primarily linked to cystinuria, a genetic condition. A urinalysis helps detect blood in the urine (hematuria)...