Related Experiment Video
Updated: Sep 13, 2026
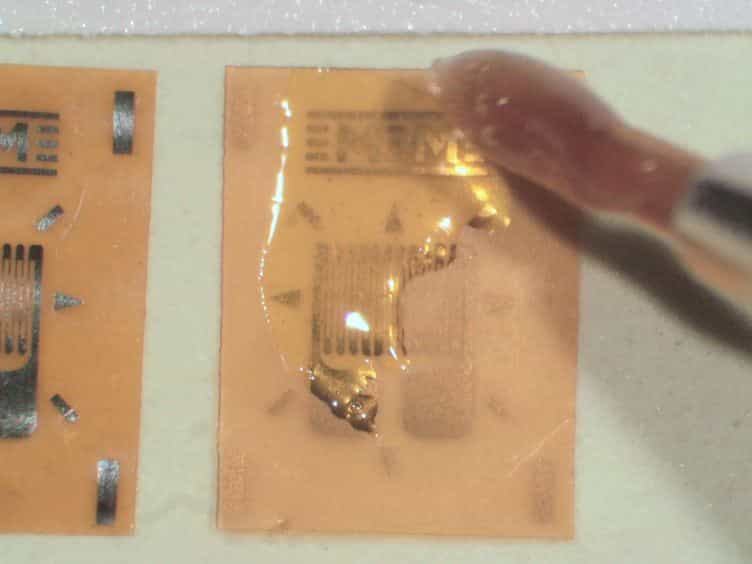

Fabrication and Implantation of Miniature Dual-element Strain Gages for Measuring In Vivo Gastrointestinal Contractions in Rodents.
Published on: September 18, 2014
Increased sensitivity of gastrin release to adrenaline in duodenal ulcer

Abstract:
Serum gastrin concentrations were measured in patients with duodenal ulcer and controls before, during, and after one-hour intravenous infusion of various doses of adrenaline (0.12 microgram to 6 microgram/min). Gastrin concentrations in the basal state were significantly increased in duodenal ulcer patients compared to controls. The maximal rise in serum gastrin concentrations was obtained at a dose of 4 microgram/min adrenaline in both groups of subjects, and the increase was significantly higher in duodenal ulcer patients than in controls. Adrenaline increased predominantly the gastrin III component (gastrin-17 like) in both duodenal ulcer patients and controls. The threshold level of adrenaline-induced gastrin release was significantly lower in duodenal ulcer patients: intravenous infusion of adrenaline in a dose of 0.12 microgram and 0.25 microgram/min increased serum gastrin concentrations 23 and 43%, respectively, but had no effect in controls. Rises in plasma adrenaline concentrations were similar in both groups of subjects in response to the various doses of adrenaline employed. Only the smallest dose of adrenaline (0.12 microgram/min) resulted in clearly physiological variations in plasma adrenaline concentrations. The results indicate that endogenous adrenaline may stimulate the secretion of gastrin during physiological conditions in patients with duodenal ulcer.
More Related Videos
 03:48
Effects of Desmodium caudatum on Gastrointestinal Hormones and Intestinal Flora in Rats with Gastritis
Published on: March 1, 2024
 03:05
Establishment and Evaluation of a Risk Prediction Model for Pathological Escalation of Gastric Low-Grade Intraepithelial Neoplasia
Published on: February 16, 2024
Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
 01:29
Intestinal Phase of Digestion
The arrival of the chyme in the small intestine distends the duodenum, which triggers the enterogastric reflex. This distension...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.