A comparative study of atenolol and penbutolol in hypertensive patients

Insights

Atenolol and penbutolol equally lowered blood pressure in hypertensive patients. Atenolol caused more bradycardia, but both drugs were well-tolerated without serious side effects or weight changes.

Area of Science:

  • Cardiology
  • Pharmacology
  • Clinical Trials

Background:

  • Hypertension is a prevalent cardiovascular condition requiring effective pharmacological management.
  • Beta-blockers are a cornerstone therapy for hypertension, with various agents available.

Purpose of the Study:

  • To compare the efficacy and safety of atenolol and penbutolol in patients with moderate hypertension.
  • To assess blood pressure reduction, side effect profiles, and tolerability of both medications.

Main Methods:

  • A randomized controlled, double-blind clinical trial involving 45 patients with moderate hypertension.
  • Patients received either atenolol 100 mg or penbutolol 40 mg for 6 weeks.
  • Blood pressure, body weight, and adverse events, including bradycardia, were monitored.

Main Results:

  • Both atenolol and penbutolol demonstrated equal effectiveness in reducing blood pressure.
  • No significant changes in body weight were observed during the treatment period.
  • Serious side effects were not reported; however, bradycardia was more frequent with atenolol compared to penbutolol.

Conclusions:

  • Atenolol and penbutolol are equally effective antihypertensive agents for moderate hypertension.
  • Penbutolol may be associated with a lower incidence of bradycardia than atenolol.
  • Both medications were generally well-tolerated, with no adverse reactions upon withdrawal.

Related Concept Videos

Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers01:25

Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers

β-adrenergic antagonists, or β-blockers, modulate the sympathetic nervous system by targeting β-adrenoceptors and inhibiting catecholamine-mediated sympathetic responses. β-blockers differ in their adrenoceptor subtype affinity, lipophilicity, and α-blocking capabilities. The history of β-blocker development began with the prototype, dichloroisoprenaline, which exhibited partial agonist activity. As a result, propranolol was developed as a pure antagonist but nonselective agent, paving the way...
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers01:27

Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers

β-receptor blockers significantly impact the cardiovascular system by counteracting catecholamine-induced sympathetic responses. These medications decrease heart rate, contractility, and cardiac output, potentially leading to cardiac depression, life-threatening bradycardia, and death. Therapeutically, β-blockers function as mild antihypertensives and are utilized in treating angina pectoris and cardiac arrhythmias. However, nonselective β-blockers inhibit β2-receptors in bronchial smooth...
Adrenergic Antagonists: ɑ and β-Receptor Blockers01:31

Adrenergic Antagonists: ɑ and β-Receptor Blockers
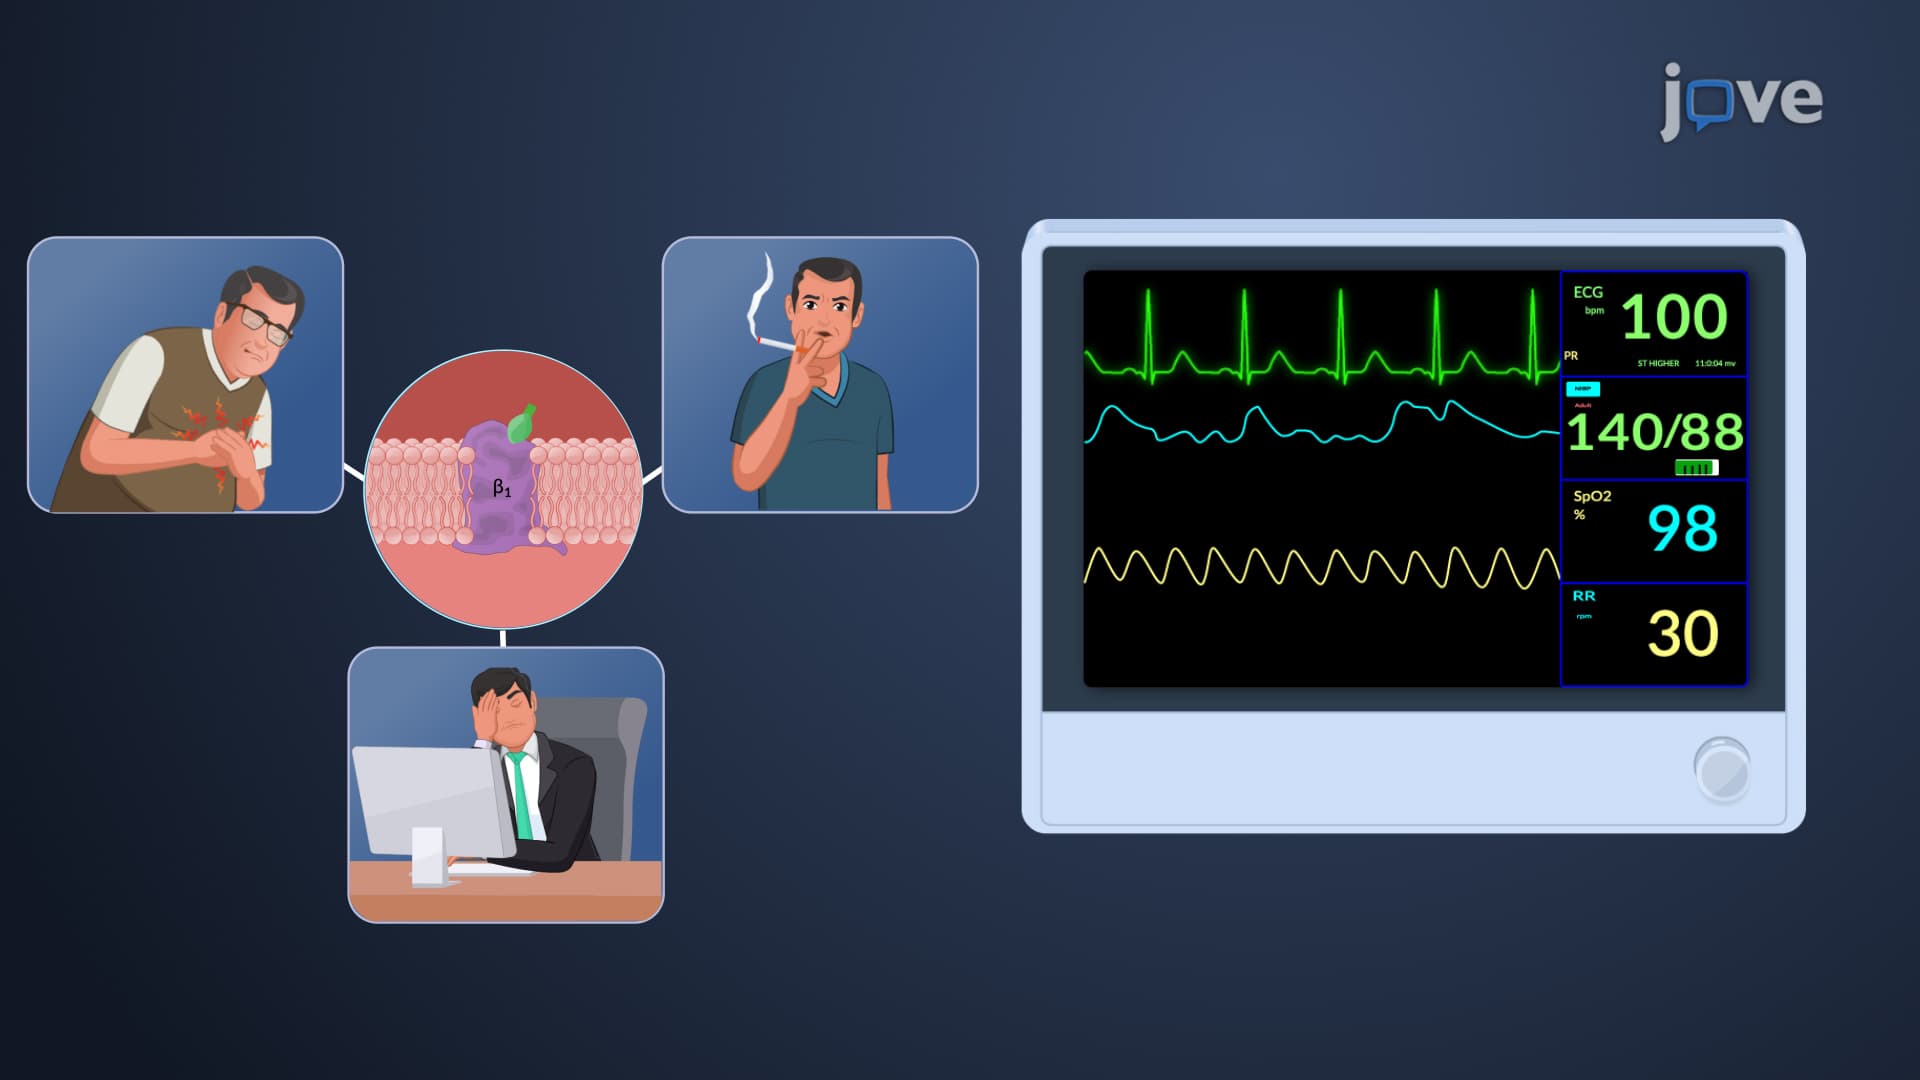
Third-generation β-blockers, such as labetalol and carvedilol, represent a significant advancement in managing cardiovascular conditions. Unlike conventional β-blockers, which can induce peripheral vasoconstriction, third-generation drugs block α1 adrenoceptors. This promotes vasodilation through several mechanisms, such as increased nitric oxide production, inhibition of calcium ion entry, opening of potassium ion channels, and antioxidant action. Labetalol, for instance, is clinically...
Antihypertensive Drugs: Action of β1 Blockers01:17

Antihypertensive Drugs: Action of β1 Blockers
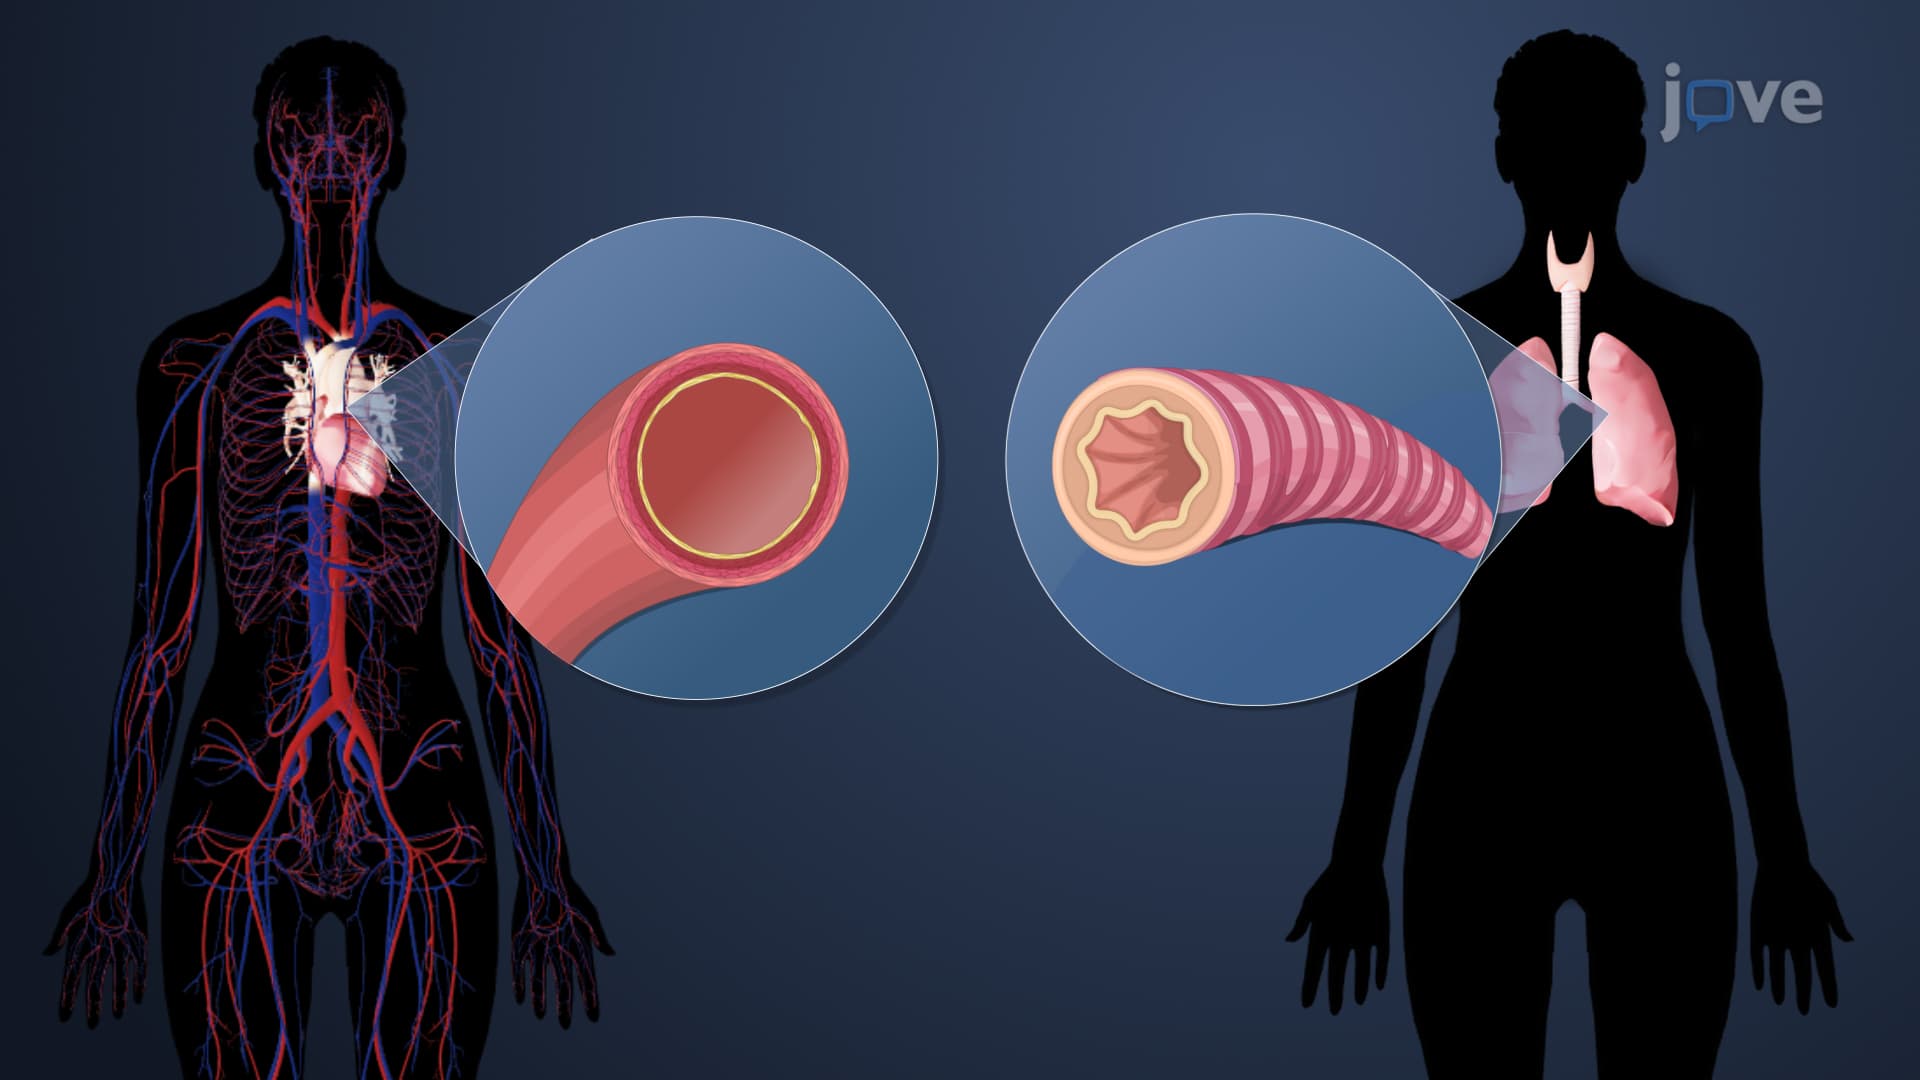
β1-receptors are primarily located in the heart and kidneys. In cardiac myocytes, these receptors interact with neurotransmitters released by the sympathetic nervous system during heightened activity or danger. As a result, β1-receptors get activated, initiating a series of biochemical processes. Excessive activation of beta receptors due to chronic stress can abnormally increase heart rate and contractility, resulting in high blood pressure or hypertension. To counteract this, β1-blockers...
Antihypertensive Drugs: Types of β-Blockers01:28

Antihypertensive Drugs: Types of β-Blockers

β receptors are classified into three subclasses: β1, β2, and β3. β1 receptors are primarily located in the heart and kidneys. When they get activated, they increase heart rate, contractility, and renin release. This process enhances blood pressure and aids in stress management. In contrast, β2 receptors are situated mainly in the lungs, blood vessels, and skeletal muscles. Upon activation, they trigger smooth muscle relaxation, causing bronchodilation and vasodilation. This widens airways and...
Antihypertensive Drugs: Angiotensin II Receptor Blockers01:30

Antihypertensive Drugs: Angiotensin II Receptor Blockers

In the renin-angiotensin-aldosterone system, a hormone called angiotensin II plays a crucial role. It binds to the AT1 receptors in vascular smooth muscles coupled with Gq proteins. The activation of these receptors activates an enzyme called phospholipase C, which releases two molecules: inositol trisphosphate and diacylglycerol. These molecules cause a chain reaction that leads to the phosphorylation of myosin light chains and promotes interaction between actin and myosin, leading to smooth...