
The complicated septic abdominal wound

Abstract:
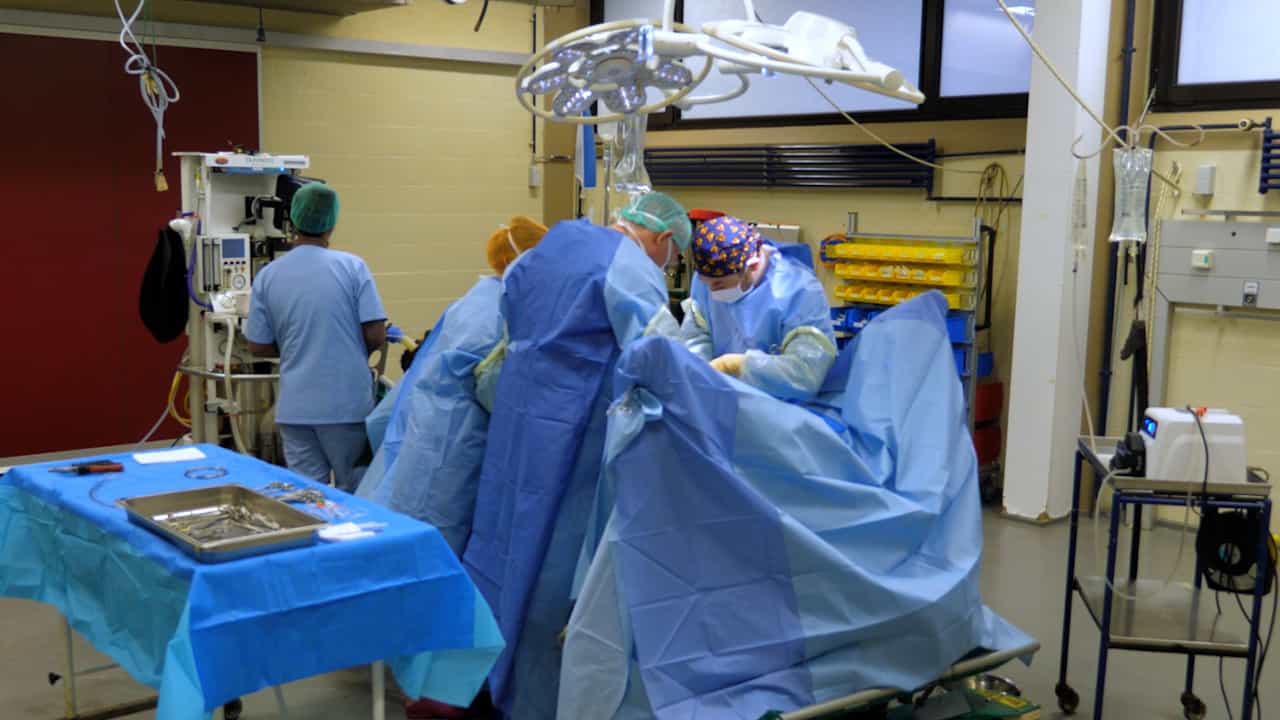
Since 1975, we have treated 21 patients with severe postoperative liquefaction fascial necrosis of the abdominal wall (group A, 13 patients), postoperative fascial necrosis with an associated intestinal fistula(e) within the wound (group B, three patients) and postoperative fascial necrosis with multiple internal bowel fistulae causing continuing peritoneal contamination (group C, five patients). Management in group A included general exploratory laparatomy, drainage of intra-abdominal abscesses, debridement of necrotic fascia, and loose closure of the wound with polyethylene (Marlex) mesh. Treatment in group B consisted of suture closure of exposed bowel fistulae with skin flap coverage. Group C was treated with diverting jejunostomy and suture closure of distal fistulae to avoid hazardous dissection and preserve bowel length. Overall survival was 71%.

Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:26
Aneurysm III: Interprofessional Care
 01:24
Healing II: Complications
 01:07
Intestinal Obstruction II: Pathophysiology
 01:19
Appendicitis