Related Experiment Video
Updated: May 7, 2026
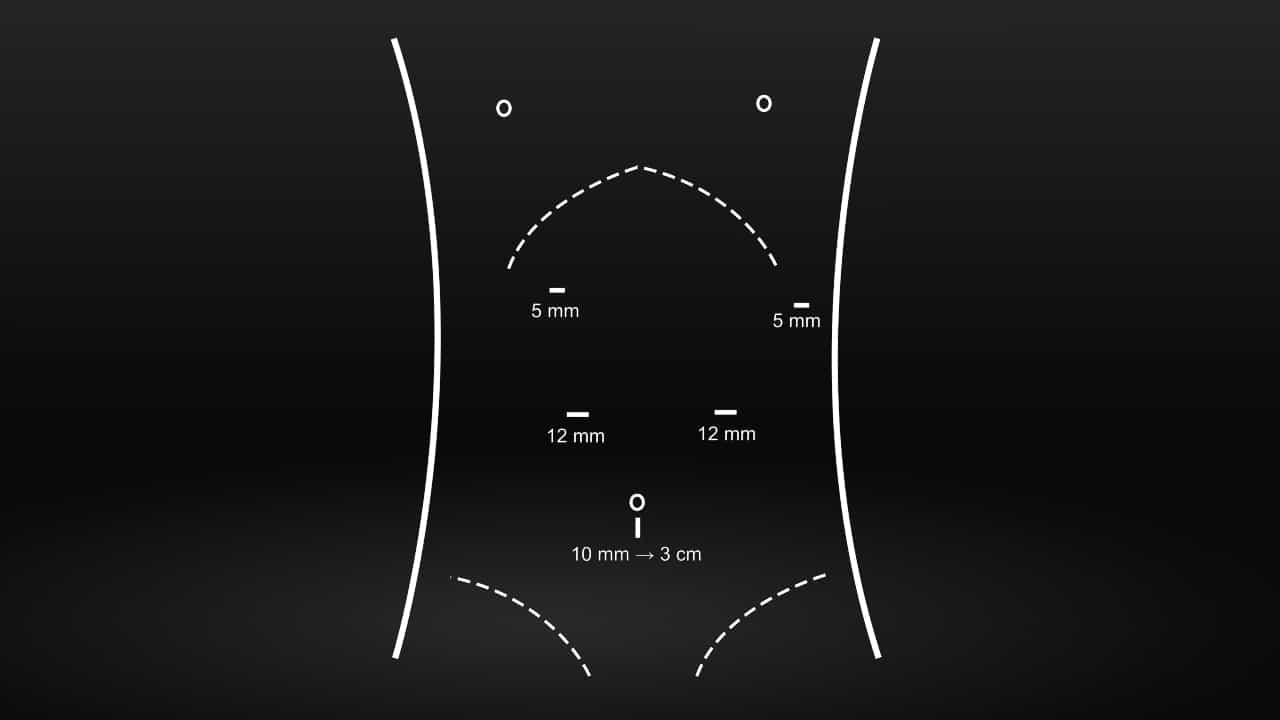
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Clinical outcome after percutaneous transhepatic obliteration of esophageal varices

Abstract:
A 4.5-yr experience with percutaneous transhepatic obliteration of gastroesophageal varices in 49 patients is reviewed with respect to technical success, control of active hemorrhage, rebleeding frequency, survival, and complications to better define clinical guidelines regarding its application. The procedure was successfully completed in 94% (46 of 49) of patients, and complete obliteration of all variceal feeder vessels was achieved in approximately one-half (52%). Variceal hemorrhage was controlled in three-quarters (76%) of actively bleeding patients, and recurrent hemorrhage occurred in 65% of patients at mean follow-up of 33 wk. Complete obliteration of all variceal feeder vessels was found not to be necessary from a technical standpoint, because the frequency of control of active hemorrhage and rebleeding were not significantly different in those patients having partial as compared with complete obliteration. In comparison with the reported outcome following standard medical therapy of bleeding varices, survival after variceal obliteration appears similar, but death from hemorrhage may be reduced. The interval to rebleeding is longer in patients having elective variceal obliteration after medical control of hemorrhage than in actively bleeding patients undergoing urgent obliteration of varices. The complication rate of obliteration was acceptable, but Child's class C patients with uncontrolled hemorrhage were a subgroup that experienced high mortality and derived little benefit from obliteration. Variceal obliteration is most appropriate in the bleeding but medically stabilized patient or the inoperable patient with recurrent bleeding. Active bleeding is most often controlled and recurrent bleeding may be prevented for several months, thus allowing consideration of elective shunt surgery.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care