Related Experiment Video
Updated: Aug 19, 2026

Isolation of Human Atrial Myocytes for Simultaneous Measurements of Ca2+ Transients and Membrane Currents
Published on: July 3, 2013
Imipramine binding to alpha-1-acid glycoprotein in normal subjects and cardiac patients

The relationship between binding ratio of imipramine and plasma alpha 1-acid glycoprotein (AAG) was determined in normal subjects, patients with chest pain syndrome, and patients after myocardial infarction. Binding ratio of imipramine was determined by equilibrium dialysis and plasma AAG concentration was determined by radial immunodiffusion. Plasma AAG concentrations ranged from 56 to 80 mg/dl (mean = 65 +/- 9 mg/dl) in 12 normal subjects, from 86 to 228 mg/dl (mean = 125 +/- 37 mg/dl) in 12 patients with chest pain syndrome, and from 78 to 350 mg/dl (mean = 181 +/- 69 mg/dl) in 12 patients after myocardial infarction. Plasma AAG concentrations in the three patient groups differed. Binding ratio ranged from 5.6 to 19.8 (mean = 12 +/- 3.5). Binding ratio of imipramine significantly correlated with plasma AAG concentration, but not with plasma albumin. In addition, binding ratio of imipramine and pure AAG was significantly related, indicating AAG is an important determinant for imipramine binding. If plasma AAG concentration increases or changes rapidly, plasma drug concentration and drug effect may be unpredictable. Under these circumstances an estimate of free drug fraction may be clinically helpful and can be estimated from the formula. y = 7.95 + 0.03 X AAG.
The relationship between binding ratio of imipramine and plasma alpha 1-acid glycoprotein (AAG) was determined in normal subjects, patients with chest pain syndrome, and patients after myocardial infarction. Binding ratio of imipramine was determined by equilibrium dialysis and plasma AAG concentration was determined by radial immunodiffusion. Plasma AAG concentrations ranged from 56 to 80 mg/dl (mean = 65 +/- 9 mg/dl) in 12 normal subjects, from 86 to 228 mg/dl (mean = 125 +/- 37 mg/dl) in 12 patients with chest pain syndrome, and from 78 to 350 mg/dl (mean = 181 +/- 69 mg/dl) in 12 patients after myocardial infarction. Plasma AAG concentrations in the three patient groups differed. Binding ratio ranged from 5.6 to 19.8 (mean = 12 +/- 3.5). Binding ratio of imipramine significantly correlated with plasma AAG concentration, but not with plasma albumin. In addition, binding ratio of imipramine and pure AAG was significantly related, indicating AAG is an important determinant for imipramine binding. If plasma AAG concentration increases or changes rapidly, plasma drug concentration and drug effect may be unpredictable. Under these circumstances an estimate of free drug fraction may be clinically helpful and can be estimated from the formula. y = 7.95 + 0.03 X AAG.
More Related Videos
 14:24
Percutaneous Contrast Echocardiography-guided Intramyocardial Injection and Cell Delivery in a Large Preclinical Model
Published on: January 21, 2018
 11:53
Simultaneous Isolation and Culture of Atrial Myocytes, Ventricular Myocytes, and Non-Myocytes from an Adult Mouse Heart
Published on: June 14, 2020
Related Concept Videos
 01:21
G-Protein Gated Ion Channels
Sensory organs,...
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
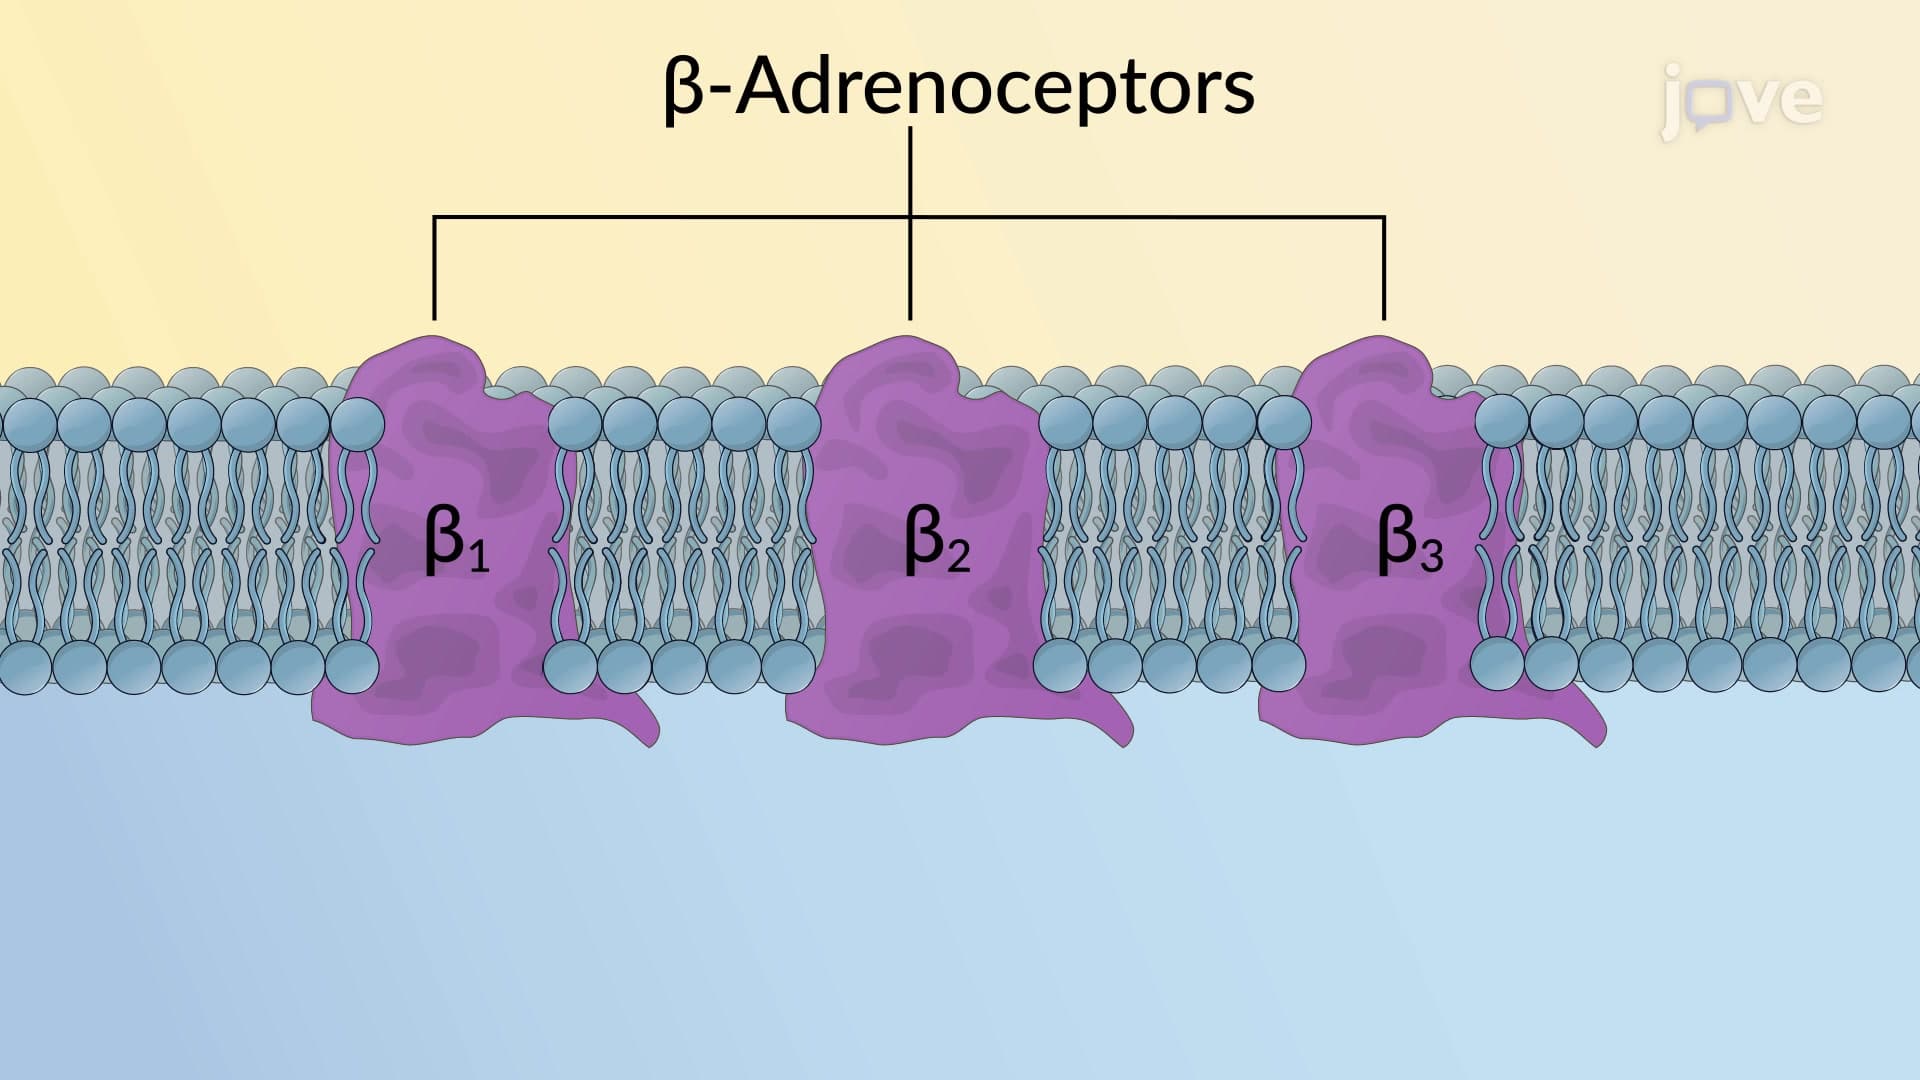
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:16
Adrenergic Agonists: Chemistry and Structure-Activity Relationship
Aromatic ring substitutions: Substituting the aromatic ring with –OH groups at positions 3 and 4 yields catecholamines (e.g., epinephrine), which have a high affinity for adrenoceptors. Hydrogen bonding between –OH groups and receptors enhances adrenergic activity.
Separation of the aromatic...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:21
Drugs Affecting Neurotransmitter Release or Uptake