Related Experiment Video
Updated: Jul 29, 2026

Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment (RMCA) in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Functional residual capacity and severity of respiratory distress syndrome in infants

Abstract:
Infants with respiratory distress syndrome (RDS) have insufficient surfactant systems and decreased functional residual capacity (FRC). This study attempts to relate FRC with severity of disease course. Measurements were made on 36 newborn infants with clinically diagnosed RDS. All infants were intubated and breathing on continuous positive airway pressure (CPAP) at the time studied. Infant CPAP levels were adjusted to 10 cm H2O; then FRC and arterial blood gas measurements were made. The infants were grouped according to their FRC per birth weight (BW). Volumes larger than or equal to 2 SD (larger than or equal to 42 ml/kg) of normal term infants not on CPAP were placed in the "large FRC" group. Volumes within +/- 2 SD (15-41 ml/kg) were in the "medium FRC: group, and infants smaller than or equal to 2 SD (< 14 ml/kg) of normal were in the "small FRC" group. The severity of RDS disease course was judged by the time duration the infants were managed on CPAP and FIO2 > 0.21 and by the maximum CPAP and FIO2 levels used. Twelve infants (33%) had small FRC, 18 (50%) medium FRC, and 6 (17%) large FRC. The time duration the infants with large FRC were on CPAP was significantly less than infants with medium FRC and the medium FRC group time was less than the small FRC group. The time duration on increased FIO2 and maximum FIO2 level used on the large FRC group was less than the medium and small FRC groups. Thus, FRC/BW appears related to the severity of RDS disease course. It is possible that the infants with FRC/BW larger than or equal to 42 ml/kg had pneumonia and were misdiagnosed as RDS. If so, FRC monitoring could have assisted in their diagnosis. BW and gestational ages of the groups were not different. Thus, variables other than these two play an important role in the degree of atelectasis occurring in infants with RDS. In patient management, where frequent changes in airway pressure and FIO2 are made, knowing the FRC/BW as well as blood gas values could aid the clinician in his choice of CPAP and FIO2 levels.
More Related Videos
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
 06:11
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Related Concept Videos
 01:15
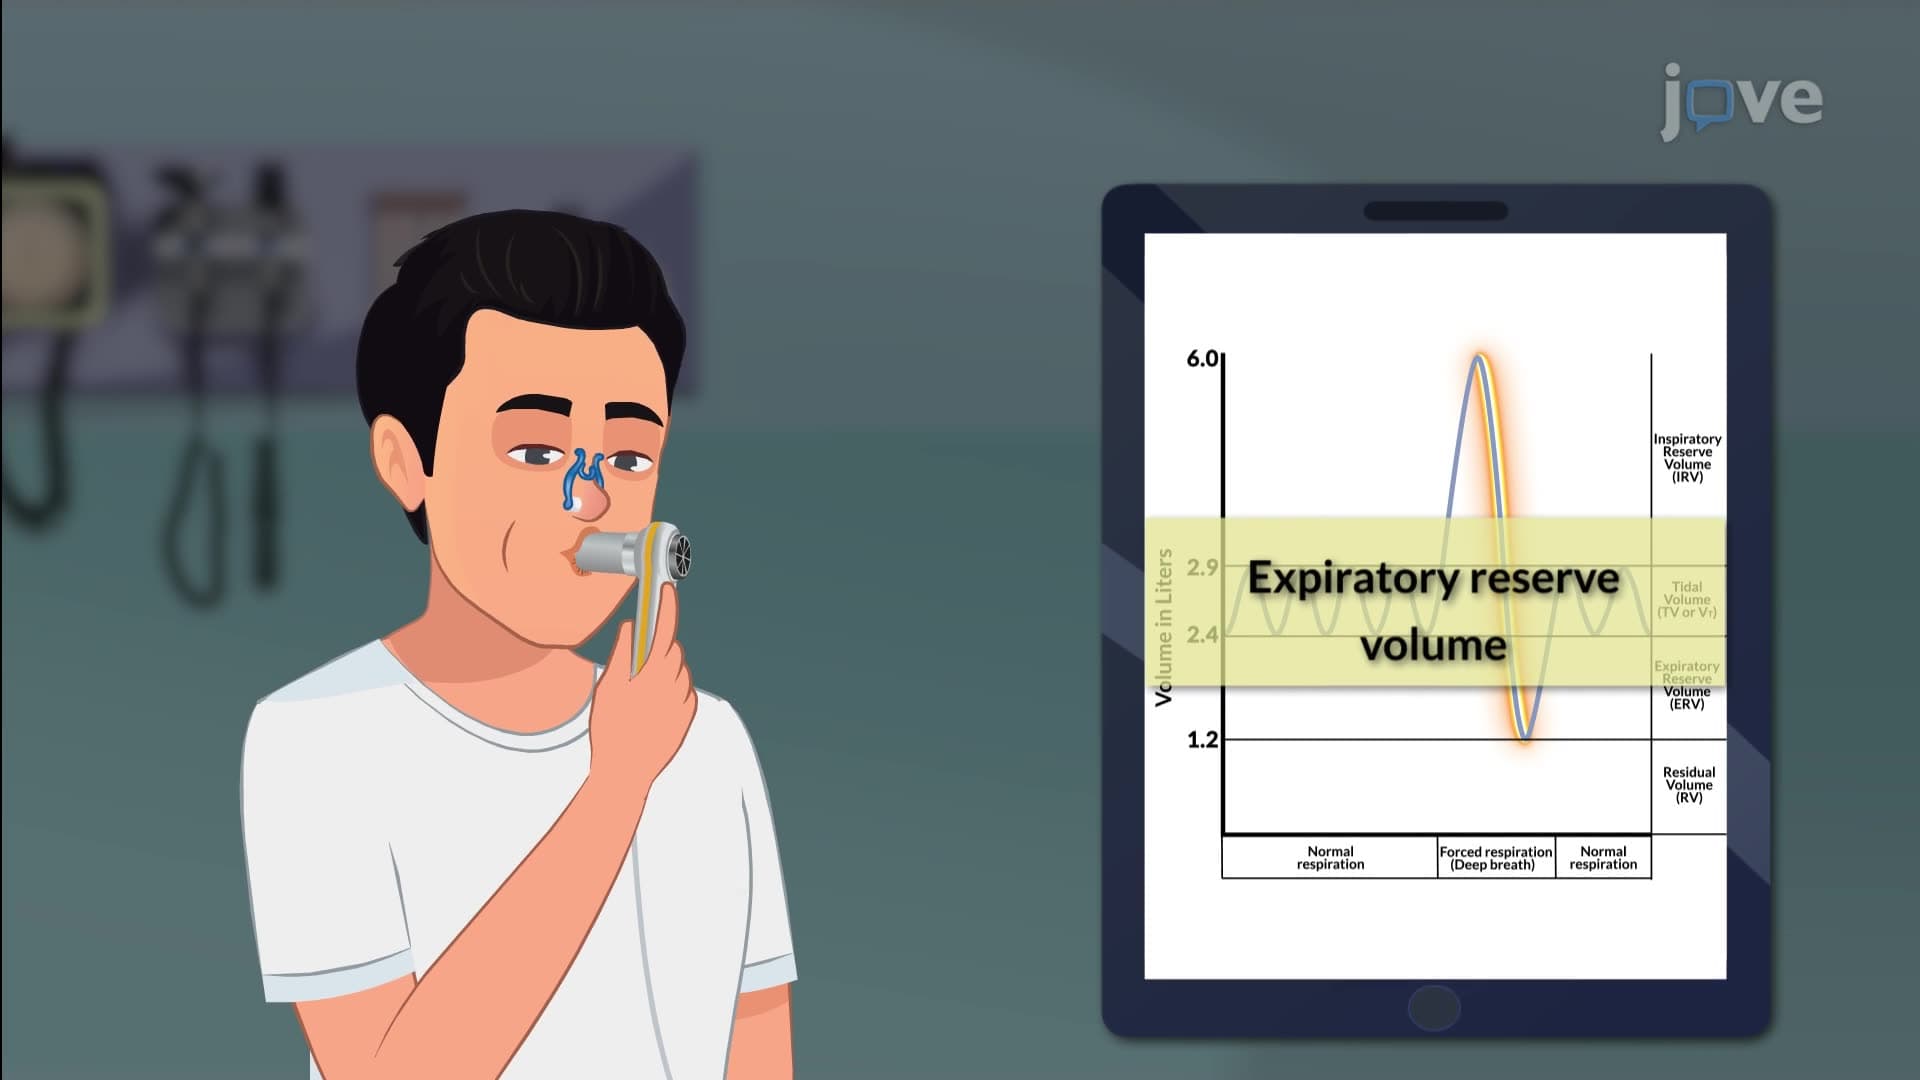
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:22
Respiratory Volumes and Capacities
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...