Related Experiment Video
Updated: Sep 23, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Serum immunoreactive trypsin after secretin stimulation in chronic pancreatitis

Serum immunoreactive trypsin (IRT) response to secretin injection was studied in 13 patients with chronic pancreatitis with different degrees of exocrine dysfunction and in 10 control subjects. The maximal increase of serum IRT from basal values and the integrated trypsin output (ITO) after secretin administration were significantly correlated with the output of chymotrypsin into the duodenum during caerulein-secretin infusion (p < 0.01), but not with the output of lipase nor of bicarbonate. Serum IRT response to secretin stimulation was greater in 4 of the 5 patients with chronic pancreatitis with mild to moderate exocrine dysfunction than in the control group, suggesting an increased regurgitation of IRT into the blood stream by the pancreas, probably due to some degree of obstruction to pancreatic secretory flow in absence of severe acinar cell damage. Conversely, the response of serum IRT after secretin administration in 7 of the 8 patients with severe exocrine pancreatic deficiency was lower than in control subjects, probably because of the advanced distruction of the acinar pancreatic tissue. The response of serum IRT to secretin stimulation seems to vary following pancreatic function impairment and might reflect the degree of pancreatic exocrine dysfunction in chronic pancreatitis.
Serum immunoreactive trypsin (IRT) response to secretin injection was studied in 13 patients with chronic pancreatitis with different degrees of exocrine dysfunction and in 10 control subjects. The maximal increase of serum IRT from basal values and the integrated trypsin output (ITO) after secretin administration were significantly correlated with the output of chymotrypsin into the duodenum during caerulein-secretin infusion (p < 0.01), but not with the output of lipase nor of bicarbonate. Serum IRT response to secretin stimulation was greater in 4 of the 5 patients with chronic pancreatitis with mild to moderate exocrine dysfunction than in the control group, suggesting an increased regurgitation of IRT into the blood stream by the pancreas, probably due to some degree of obstruction to pancreatic secretory flow in absence of severe acinar cell damage. Conversely, the response of serum IRT after secretin administration in 7 of the 8 patients with severe exocrine pancreatic deficiency was lower than in control subjects, probably because of the advanced distruction of the acinar pancreatic tissue. The response of serum IRT to secretin stimulation seems to vary following pancreatic function impairment and might reflect the degree of pancreatic exocrine dysfunction in chronic pancreatitis.


Related Concept Videos
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Acute Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
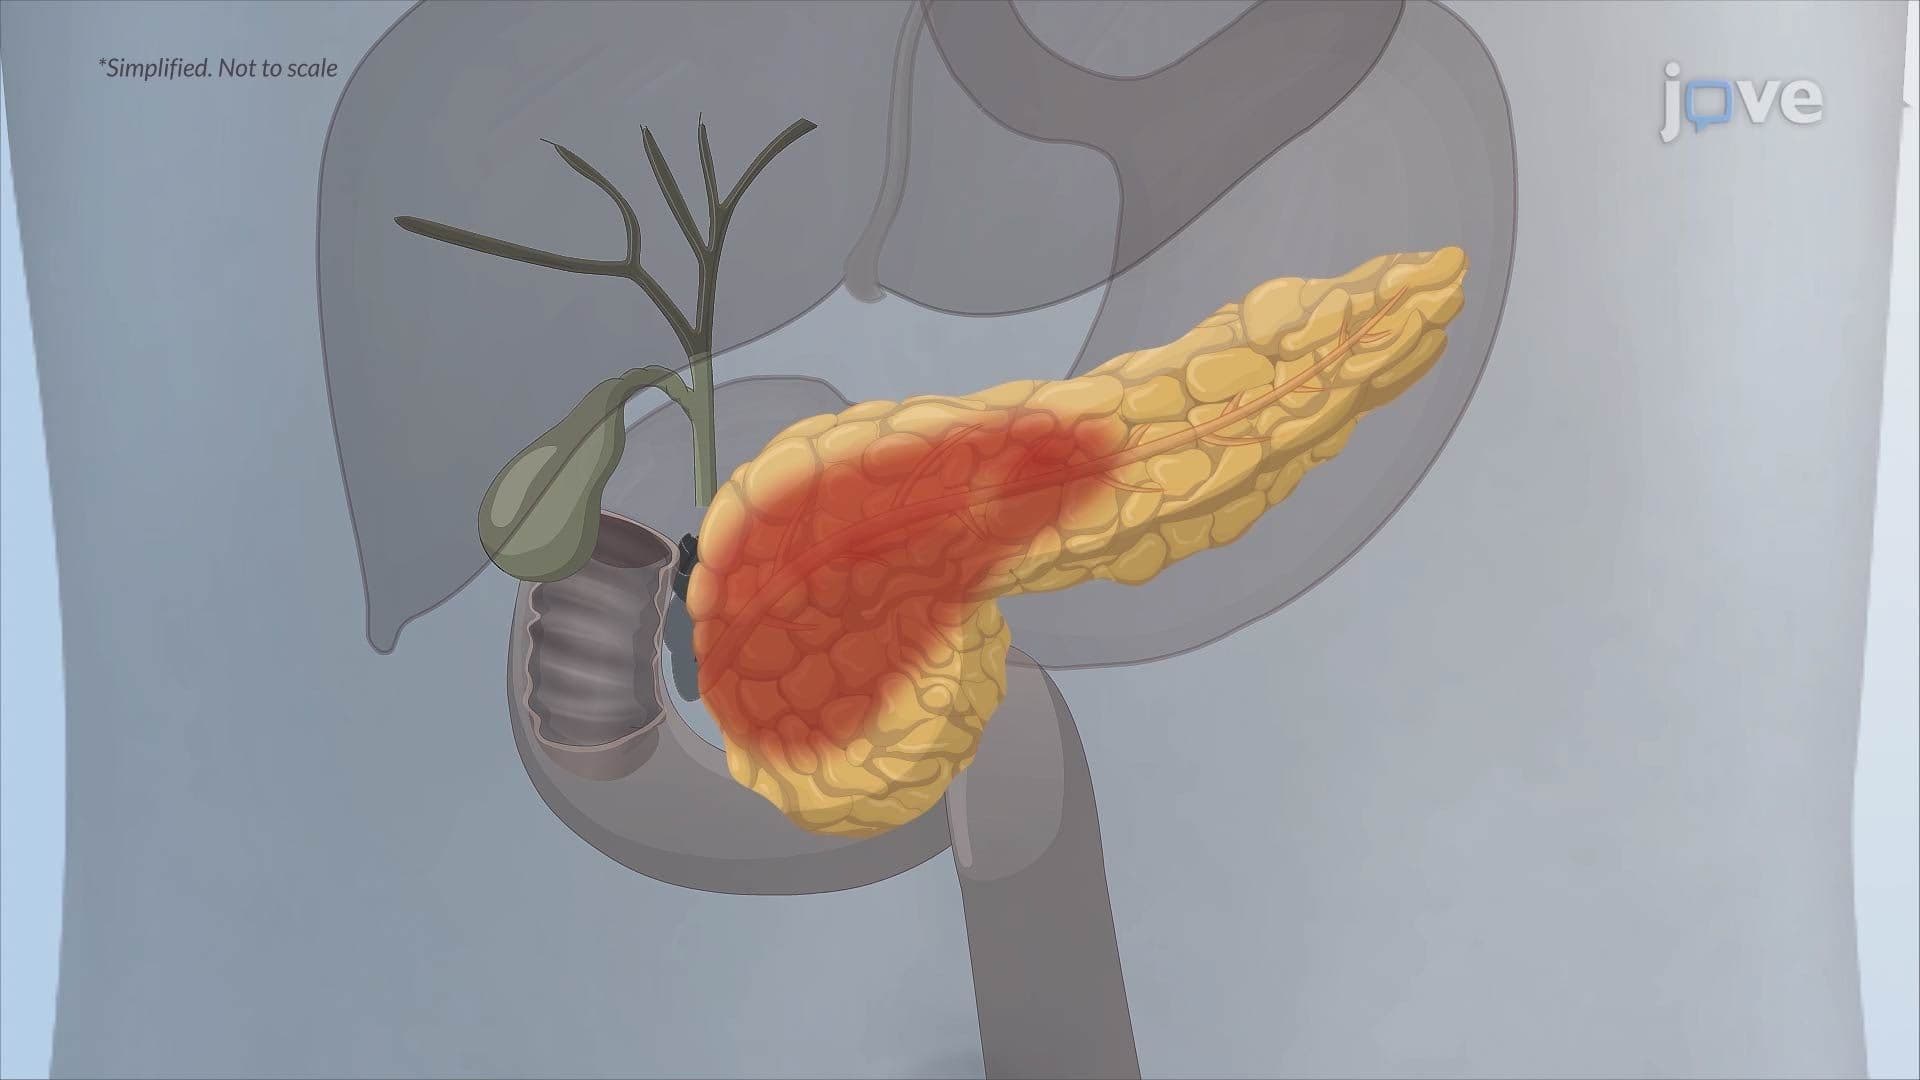 01:25
Chronic Pancreatitis I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology