Related Experiment Video
Updated: Oct 23, 2026

Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
Pulmonary microembolism as a cause of acute respiratory failure

Abstract:
Clinical and autopsy studies have shown an association between pulmonary microembolism and acute respiratory failure after trauma or sepsis. Prophylaxis and treatment with the aim of decreasing the fibrin deposition in the lungs were associated with a decrease in the incidence and death rate of this syndrome. Small fibrin degradation products (peptides) are accumulated in the lungs and are only slowly cleared from this organ, especially during states of fibrinolysis inhibition. These peptides may contribute to the pulmonary damage in several ways. They act by interfering with other vasoactive substances as bradykinin, histamine and products of the arachidonic acid cascade. Products of the cyclooxygenase pathways as thromboxane A2 play a major role in early microembolism whereas lipoxygenase products seem to be involved in delayed microembolism. Pulmonary microembolism thus seems to be one important, but certainly not the only pathogenetic factor in acute "idiopathic" respiratory failure. Other factors such as pulmonary contusion, aspiration of gastric contents or blood, or oxygen toxicity, might well be contributory in some cases. Pulmonary microemboli containing fibrin and leukocytes are probably also involved as contributory agents in some cases in the large group of acute respiratory failure due to "known factors".
Insights
Pulmonary microembolism, linked to fibrin deposition, contributes to acute respiratory failure. Reducing fibrin in lungs lowers incidence and mortality, suggesting a key role for microembolism in respiratory distress.
Area of Science:
- Pulmonary Medicine
- Pathophysiology
- Critical Care
Background:
- Acute respiratory failure (ARF) is a critical condition often following trauma or sepsis.
- Pulmonary microembolism (PME) has been clinically and pathologically associated with ARF.
- Fibrin deposition in lung microvasculature is implicated in the pathogenesis of ARF.
Purpose of the Study:
- To investigate the role of pulmonary microembolism in acute respiratory failure.
- To explore the impact of reducing fibrin deposition on ARF incidence and mortality.
- To elucidate the mechanisms by which fibrin degradation products contribute to pulmonary damage.
Main Methods:
- Review of clinical and autopsy studies.
- Analysis of the effects of prophylactic and therapeutic interventions aimed at decreasing fibrin deposition.
- Examination of the accumulation and clearance of fibrin degradation products in lung tissue.
- Investigation of the role of vasoactive substances and arachidonic acid cascade products.
Main Results:
- Association found between PME and ARF post-trauma or sepsis.
- Interventions reducing lung fibrin deposition decreased ARF incidence and mortality.
- Small fibrin degradation products accumulate in lungs, especially during inhibited fibrinolysis.
- These peptides interfere with vasoactive substances, contributing to pulmonary damage.
Conclusions:
- Pulmonary microembolism is a significant, though not sole, pathogenetic factor in "idiopathic" ARF.
- Fibrin-containing microemboli and leukocytes may contribute to ARF in cases with known causes.
- Understanding PME mechanisms is crucial for managing ARF, particularly in sepsis and trauma patients.

Related Concept Videos
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III
 01:29
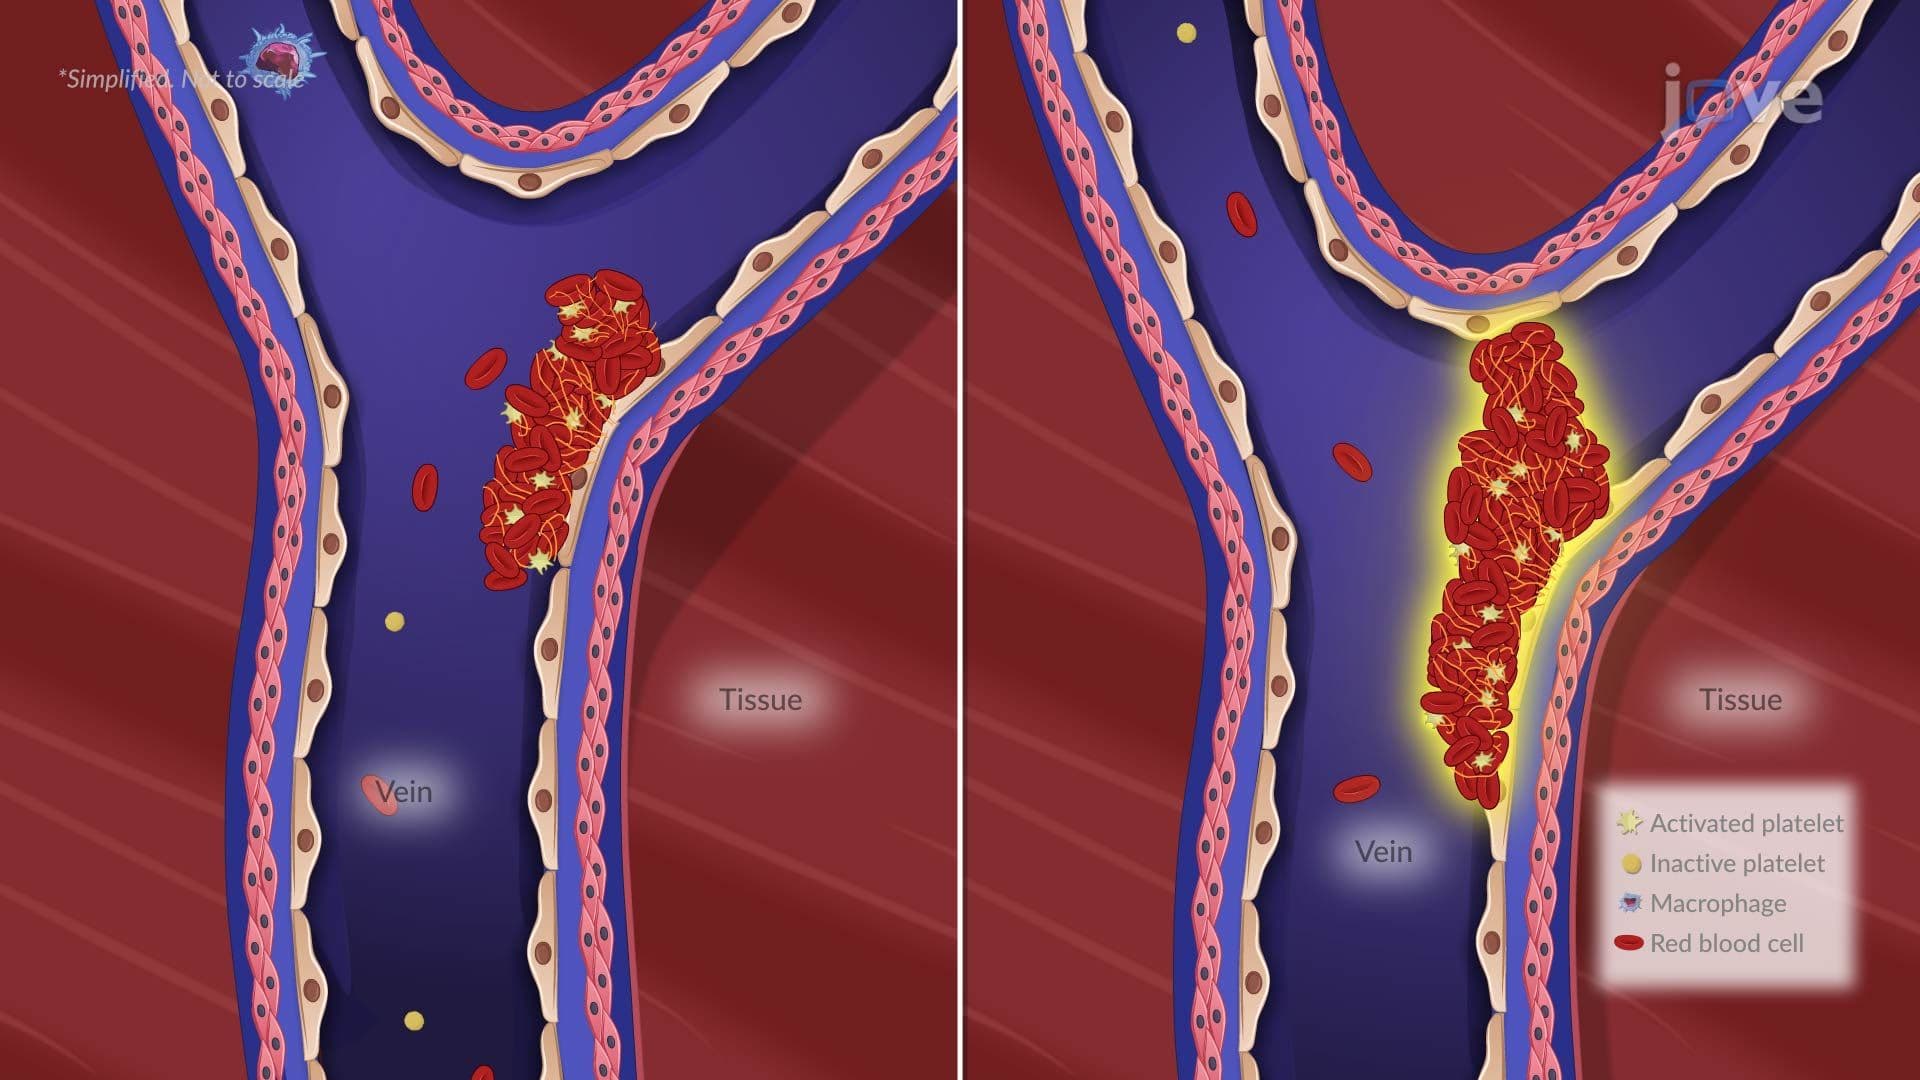
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:19
Pulmonary Embolism I: Introduction