Related Experiment Video
Updated: Aug 15, 2026
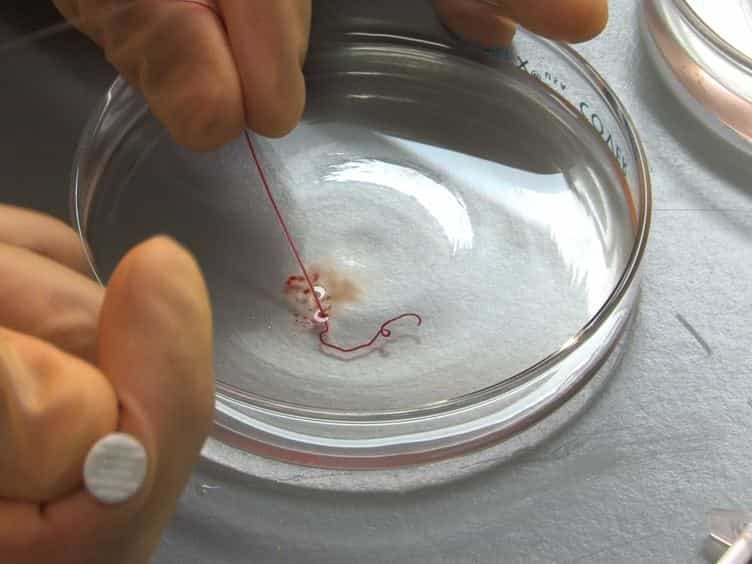

Embolic Middle Cerebral Artery Occlusion (MCAO) for Ischemic Stroke with Homologous Blood Clots in Rats
Published on: September 17, 2014

Insights
Cerebral embolism risk from rheumatic heart disease, myocardial infarction, and atrial fibrillation is significant. Anticoagulation therapy effectively reduces embolism incidence and recurrence in these cardiac conditions.
Area of Science:
- Cardiology
- Neurology
- Vascular Medicine
Background:
- Cerebral embolism is a serious complication of several cardiac conditions.
- Rheumatic heart disease (RHD), atherosclerotic heart disease (myocardial infarction, atrial arrhythmias), and nonvalvular atrial fibrillation (AF) are primary cardiac sources.
- Understanding the natural history of embolism from these sources is crucial for prevention.
Purpose of the Study:
- To review the natural history of cerebral embolism originating from common cardiac conditions.
- To evaluate the efficacy of anticoagulation in reducing embolism and recurrence.
- To provide recommendations for anticoagulation use and timing.
Main Methods:
- Literature review of studies on cardiac conditions and cerebral embolism.
- Analysis of data on embolism incidence, recurrence, and the impact of anticoagulation.
- Review of data on valvulotomy and prosthetic valve placement in RHD.
Main Results:
- Rheumatic heart disease with mitral stenosis is a significant source of emboli, with 10-20% experiencing systemic embolism and high recurrence rates.
- Myocardial infarction leads to systemic emboli in 5-12% of patients, with significant recurrence.
- As many as 10-20% of patients with nonrheumatic AF experience systemic emboli.
- Anticoagulation reduces embolism in RHD to 10-20% of natural incidence and recurrence rates.
- Anticoagulation reduces embolism in myocardial infarction to 25% of natural incidence.
- The effect of anticoagulation on nonrheumatic AF embolism is unknown.
Conclusions:
- Anticoagulation is highly effective in mitigating the risk of cerebral embolism and recurrence in RHD and myocardial infarction.
- Further research is needed to determine the role of anticoagulation in nonrheumatic AF.
- Recommendations for anticoagulation strategies are based on current evidence for these cardiac conditions.
Abstract:
The cardiac conditions most commonly associated with cerebral embolism are rheumatic heart disease (RHD), atherosclerotic heart disease (myocardial infarction and atrial arrhythmias) and other kinds of nonvalvular atrial fibillation (AF). The natural history of cerebral embolism from these cardiac sources is reviewed. Virtually all rheumatic hearts producing emboli have mitral stenosis, but not all of them are in AF. Of patients with RHD, 10--20% will experience a systemic embolus, and approximately half will have a recurrence, usually early. Of patients with a myocardial infarction, 5--12% will have a clinically apparent systemic embolus, and one-third to one-half have a recurrence, usually early. As many as 10--20% of patients with nonrheumatic AF have a systemic embolus. Anticoagulation reduces systemic embolism to 10--20% of the natural incidence in RHD, and it reduces embolic recurrences to 10--20% of the natural recurrence rate. Anticoagulation diminishes the incidence of emboli in myocardial infarction to 25% of the natural incidence. It is not known what effect anticoagulation has on the incidence of embolism in nonrheumatic AF. The data regarding the effect of valvulotomy and prosthetic valve placement in RHD are briefly reviewed. Recommendations are made for the use and timing of anticoagulation based on the available data.


Related Concept Videos
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:15
Ischemic Stroke l: Introduction