Related Experiment Video
Updated: Jul 6, 2026
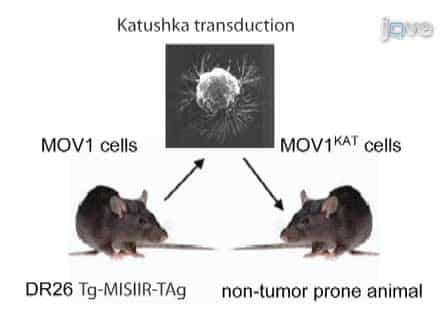

An Orthotopic Model of Serous Ovarian Cancer in Immunocompetent Mice for in vivo Tumor Imaging and Monitoring of Tumor Immune Responses
Published on: November 28, 2010
The natural history and treatment of ovarian cancer

Abstract:
Several advances in the understanding of the biology and treatment of ovarian cancer over the past five years have changed the pessimistic view of this disease that was formerly commonplace. A cornerstone of the management of patients with ovarian cancer is careful pathological staging both prior to and at the cessation of therapy. Patients with all grades of Stage I lesions except the well-differentiated ones should have some form of adjuvant therapy, although the best choice is still unclear. Similarly, Stage II patients, though few in number, have only a 50% change of surviving five years without some adjuvant treatment. Since the best choice is unclear, it would be ideal if such all patients could be treated in a study setting. Every early stage patient treated off study slows the identification of definitive therapy. For the majority of patients with advanced disease, the treatment of choice is aggressive debulking surgery followed by combination chemotherapy. After six cycles of therapy, patients should be restaged sequentially moving all the way to repeat laparotomy, if necessary, to find residual disease before therapy is discontinued. If no disease is found, we randomize patients to either careful follow-up or six cycles of intraperitoneal adjuvant therapy in an effort to prevent relapse. If residual disease is found at restaging (but less disease than at the beginning of treatment), the patient is given six more cycles of combination chemotherapy, though often at reduced doses because of cumulative bone marrow toxicity. After the twelfth cycle of chemotherapy, restaging is repeated. If disease is still present, it is unlikely that the primary therapy will be curative; however, therapy is continued until progressive disease demands a change. The ongoing joint study sponsored by the Ovarian Cancer Study Group and the Gynecologic Oncology Group in early stage disease should assist the clinician in determining the role of adjuvant single-agent chemotherapy or radioisotopes. Given the poor prognosis associated with bulky residual Stage II disease, such patients might benefit from adjuvant combination chemotherapy. In advanced disease, a number of ongoing trials are attempting to evaluate the role of radiation therapy in minimal residual Stage III disease and to improve the efficacy of combination chemotherapy. The work along with research aimed at understanding etiology and prevention and speeding diagnosis may further improve the outlook of victims of this disease.
Related Concept Videos
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 02:56
Treatment Resistant Cancers
02:56Treatment Resistent Cancers
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:30
Cancer Vaccines
Cancer vaccines come in two categories: preventive (prophylactic) and treatment (active). Preventive vaccines, such as the Human Papillomavirus (HPV) vaccine, protect against viruses that cause certain...
 01:21
Cancer Survival Analysis