[Renal tolerance for aminoglycosides]
Related Experiment Video
Updated: Oct 22, 2026
Use of a Hanging-weight System for Isolated Renal Artery Occlusion
Published on: July 19, 2011

Abstract:
Tissue pharmakinetics, morphology of renal lesions and clinical picture of aminoglycoside-induced tubulopathy are described. Almost completely filtered by the glomerulus, they are eliminated in active form and about a third are reabsorbed along the proximal convoluted tubule, thus reaching maximum concentration in the renal cortex in the sixth hour as the drug disappears from the circulation. They are located inside the lysosomes of the convoluted tubule cells where some typical formations called myeloid bodies are present. Cellular lesions are, however, only produced by high doses after, first, clinical manifestations of tubular disturbance such as polyuria, tubular proteinuria, enzymuria, followed, if the toxic insult persists, by renal insufficiency. This can present clinically as progressive renal function deterioration dependent on the dose-time factor. This deterioration is usually not oliguric and it may also present as a sudden oliguric renal insufficiency. The now fully documented risk factors are discussed as well as the duration of treatment (not more than 11 days), the dosage (3 mg/kg/die), the dosage intervals, the age factor (the elderly being shown to be more highly sensitive to the drug), the association with other aminoglycosides or diuretics or cephalosporin. It is very important to diagnose already existing nephropathies or renal insufficiency, in which case dosages must be appropriately reduced. The nephrological history of the patient and control of urea and creatinine clearances before the start of treatment (in addition, obviously, to functional control of the eighth pair of cranial nerves) are essential for all patients receiving courses of aminoglycoside therapy. It is also necessary to check renal function by daily measurements of creatinaemia and urine. These precautions are valid for all aminoglycosides including those that have come on to the market most recently.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
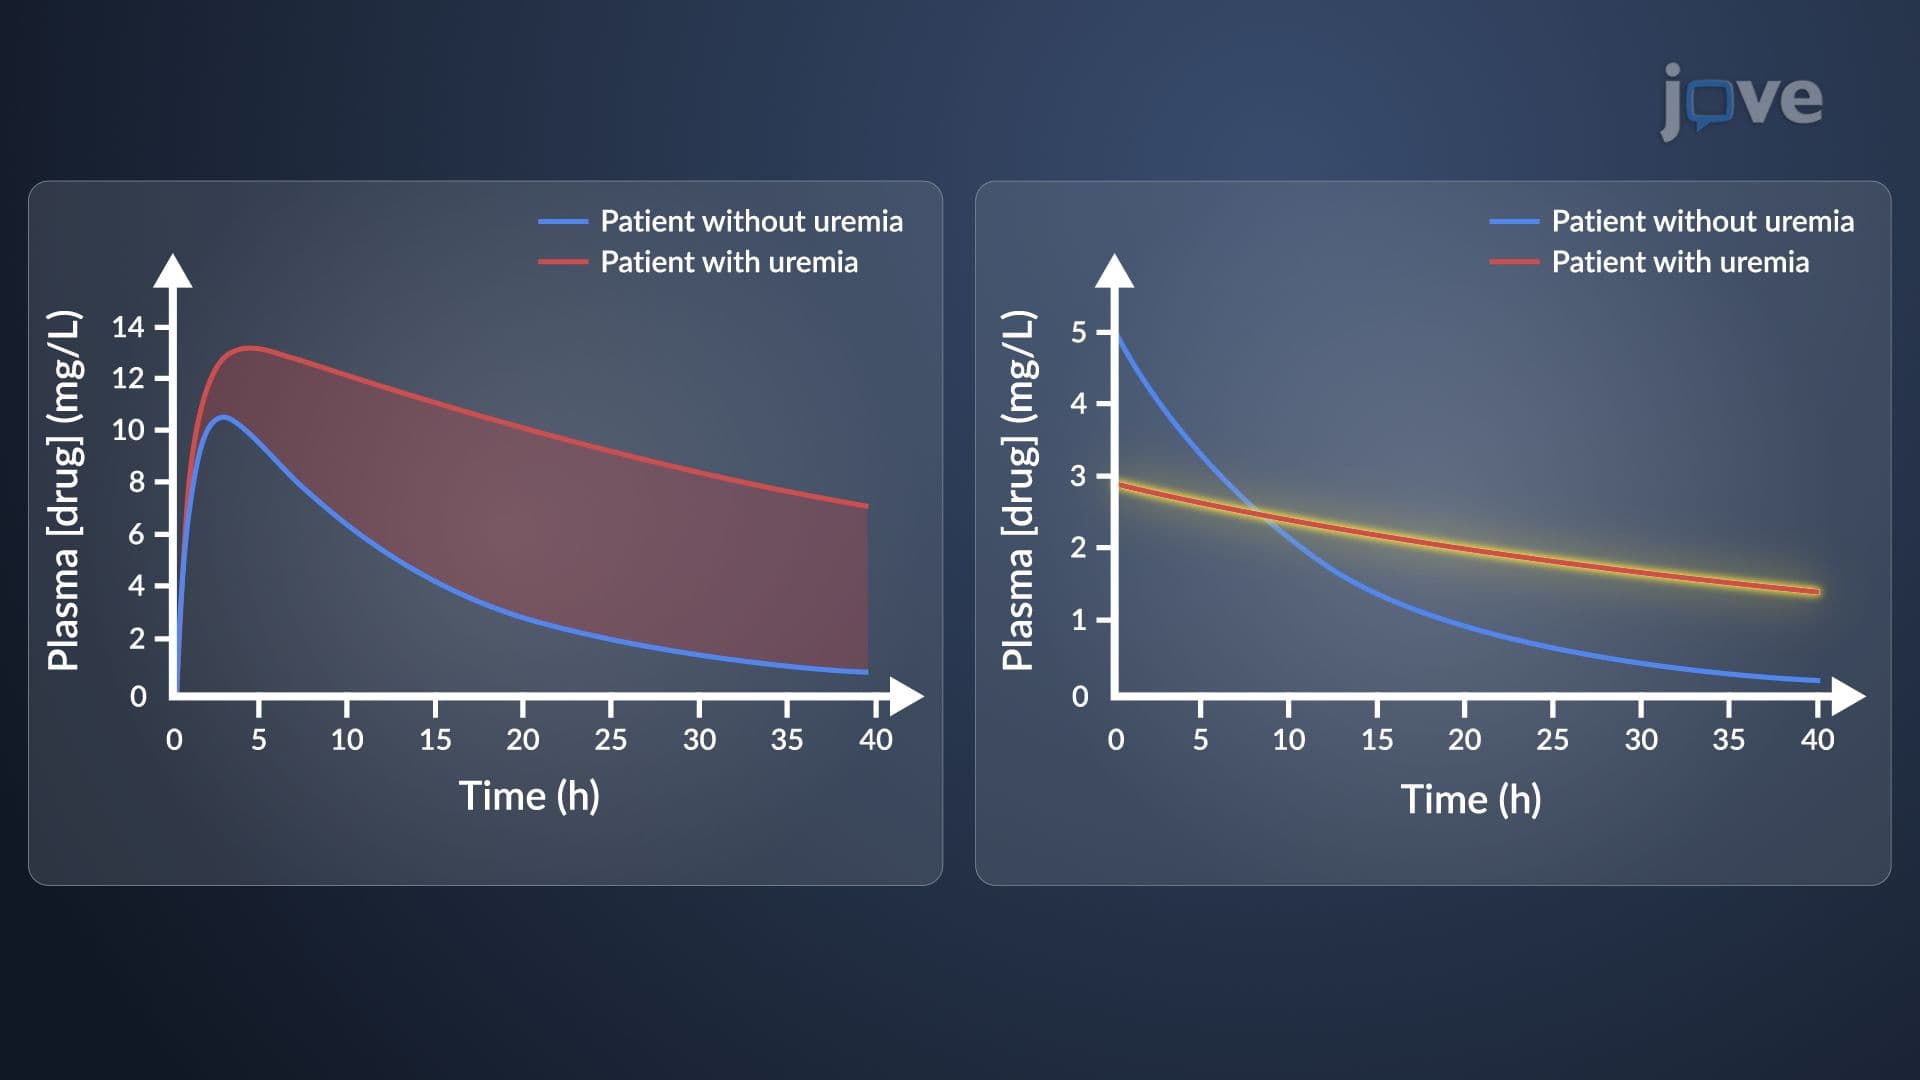
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
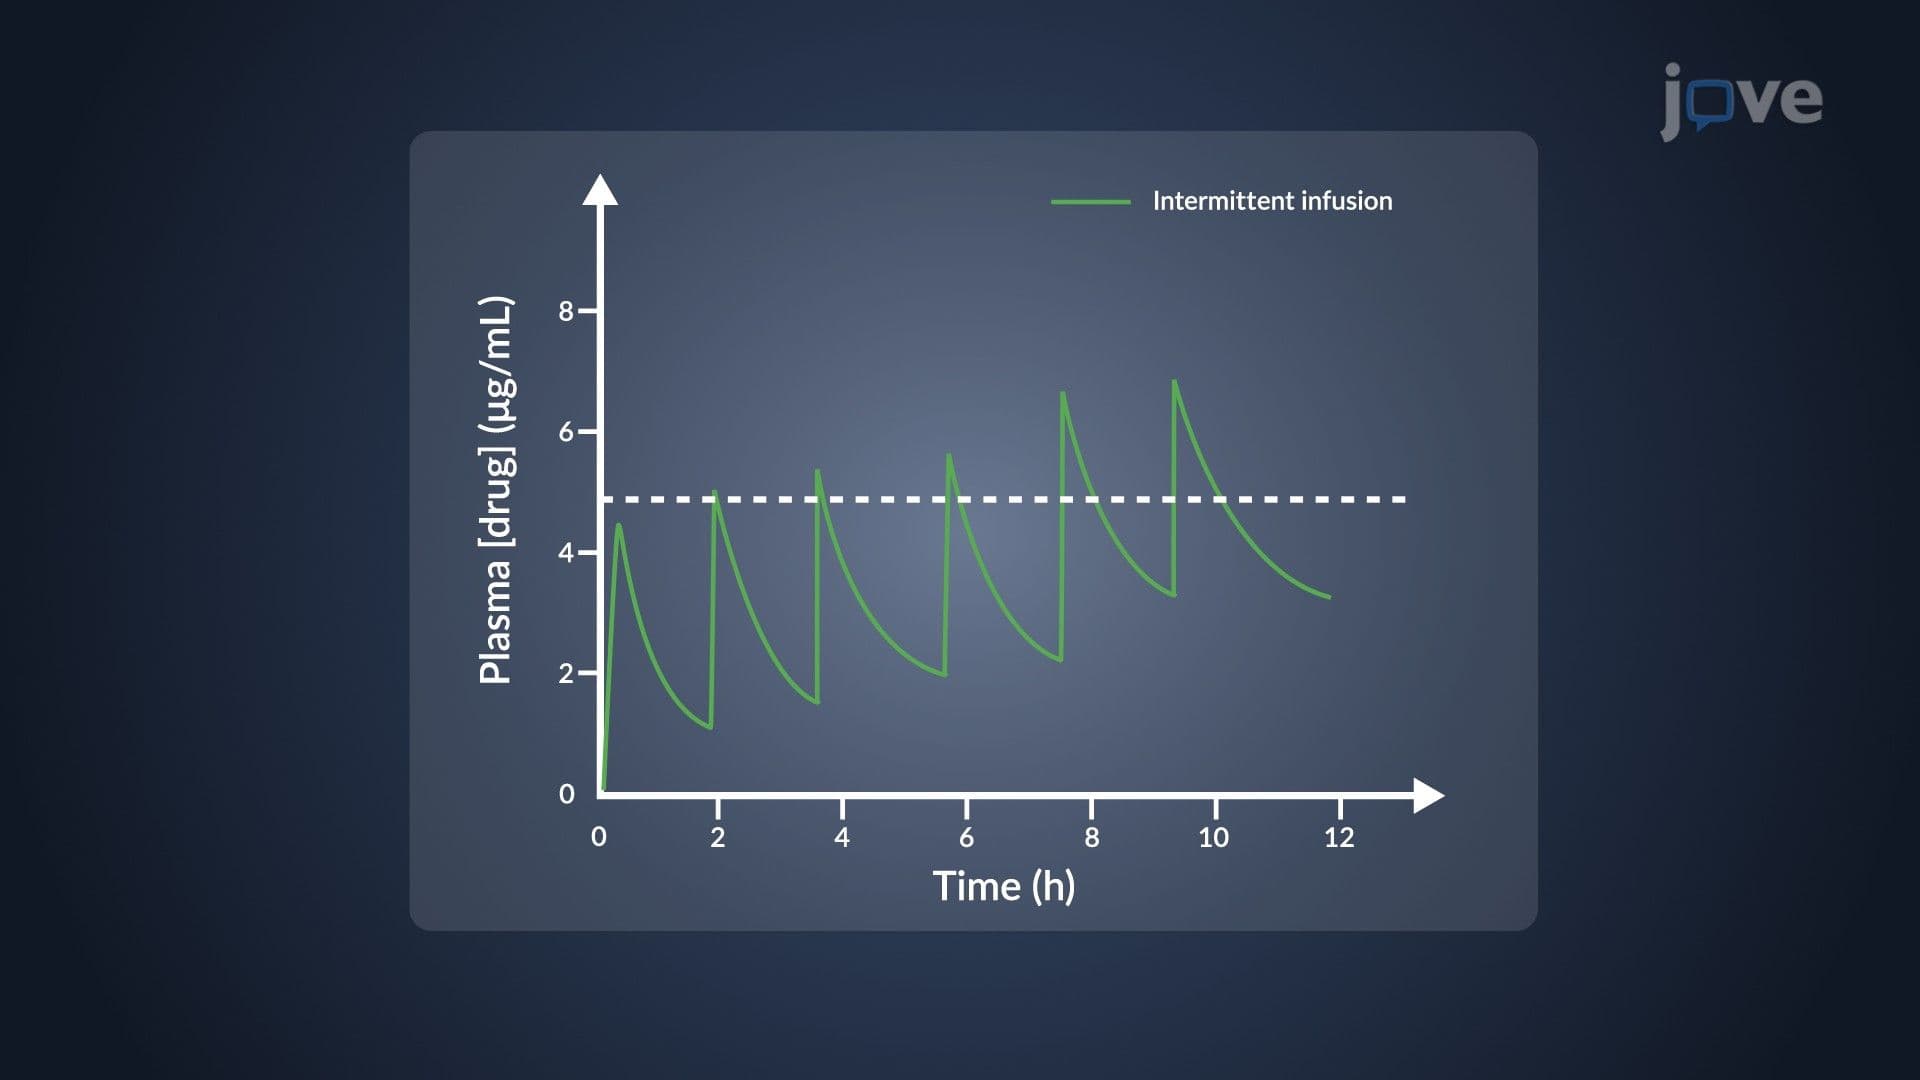
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:20
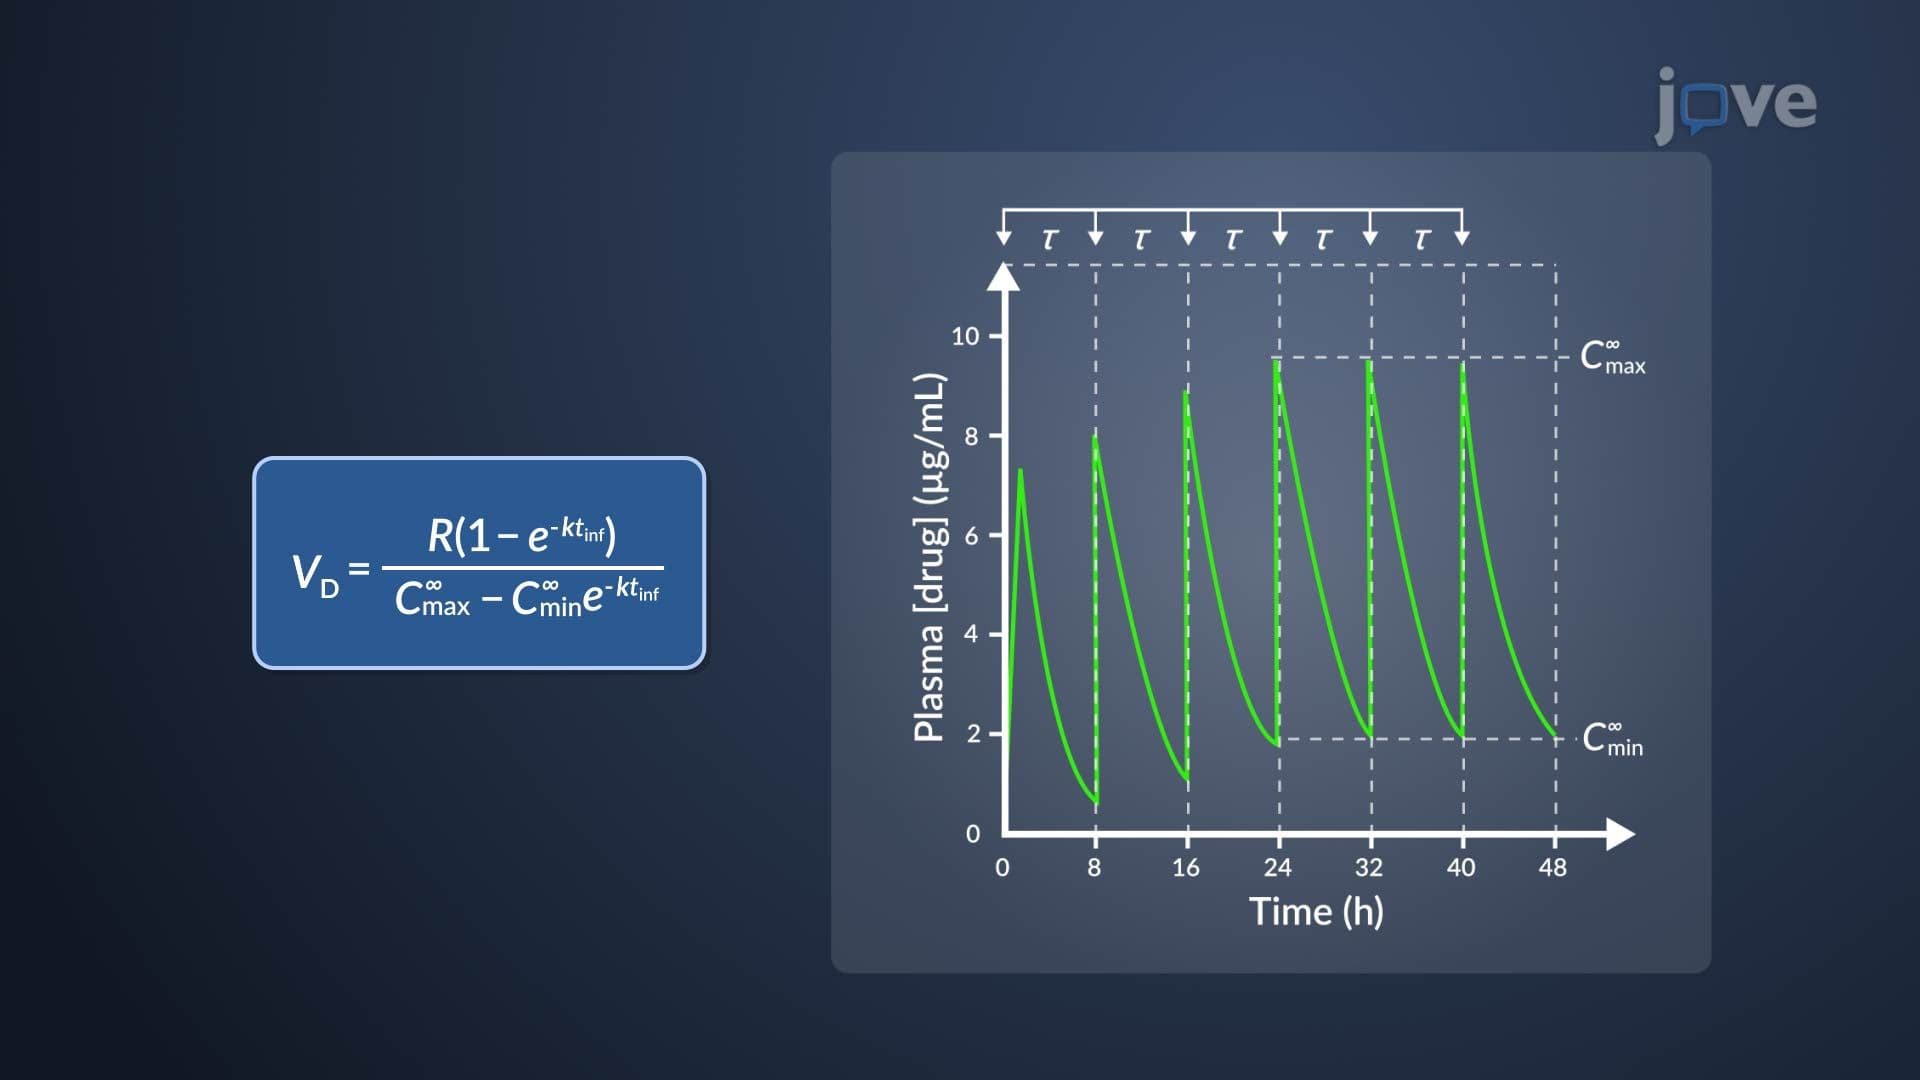
Estimation of k and VD of Aminoglycosides
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:25
Inhibitors of Bacterial Protein Synthesis