Related Experiment Video
Updated: Oct 23, 2026
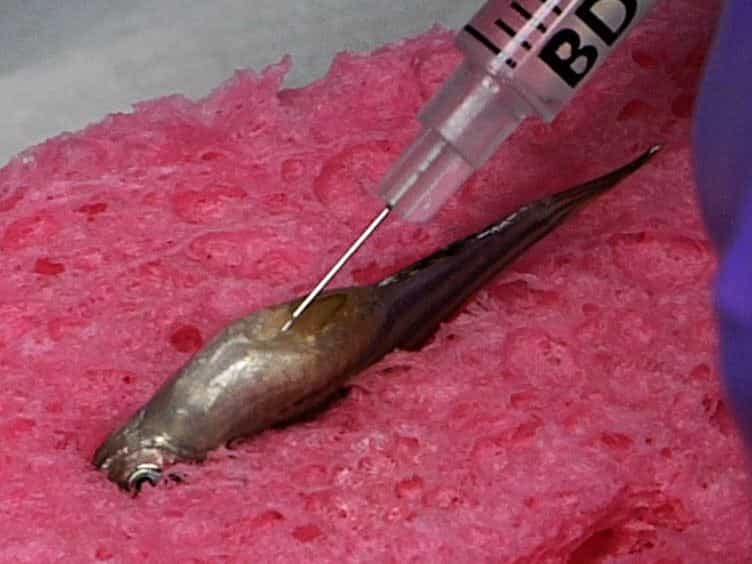
Analysis of Nephron Composition and Function in the Adult Zebrafish Kidney
Published on: August 9, 2014
Postnatal development of tubular phosphate reabsorption

Insights
Infants show higher plasma phosphate levels than children due to immature kidney function. This study highlights differences in renal phosphate handling during early development.
Area of Science:
- Pediatric Nephrology
- Renal Physiology
- Developmental Biology
Background:
- Renal phosphate handling is crucial for maintaining mineral homeostasis.
- Understanding postnatal development of kidney function is essential for pediatric health.
- Phosphate levels and excretion patterns change significantly from infancy to childhood.
Purpose of the Study:
- To investigate the developmental changes in renal phosphate handling from infancy to childhood.
- To compare plasma phosphate, urinary phosphate excretion, and tubular reabsorption between infants and children.
- To explore the relationship between fractional phosphate reabsorption and plasma phosphate levels across different age groups.
Main Methods:
- Short-term clearance investigations were performed on 51 infants (0.5-12 months) and 143 children (1-15 years).
- Measurements included plasma phosphate (Pp), urinary phosphate excretion, endogenous phosphate clearance, and net tubular phosphate reabsorption (Tp).
- Glomerular filtration rate (CIn) was assessed to calculate fractional phosphate reabsorption (Tp/CIn).
Main Results:
- Infants exhibited higher plasma phosphate, urinary phosphate excretion, and endogenous phosphate clearance compared to children.
- Net tubular phosphate reabsorption (Tp) was lower in infancy, primarily due to a lower glomerular filtration rate (CIn).
- Fractional phosphate reabsorption (Tp/CIn) was significantly higher in infants than in children, with a strong correlation to plasma phosphate.
Conclusions:
- Infants have higher plasma phosphate concentrations than children, even at similar fractional phosphate reabsorption levels.
- Lower glomerular filtration rate (CIn) in young infants likely contributes to phosphate retention.
- These findings underscore the distinct renal phosphate handling mechanisms during early postnatal development.
Abstract:
In 51 infants (0.5-12 months) and 143 children (1-15 years), the postnatal development of renal phosphate handling could be studied by short term clearance investigations. The infants demonstrated significantly higher values of plasma phosphate (Pp), urinary phosphate excretion and endogenous phosphate clearance than the children. Net tubular phosphate reabsorption (Tp) was low infancy due to low glomerular filtration rate (CIn). The fractional phosphate reabsorption (Tp/CIn), however, was significantly higher in infancy than in childhood. There was a close correlation between fractional phosphate reabsorption and plasma phosphate for both children and infants. When the regression lines of Pp to Tp/CIn were analyzed separately for children and infants, a parallel shift was recognized, which means that at each level of Tp/CIn infants had higher plasma phosphate concentrations than children. Evaluation of available data suggests that the shift was very probably related to low CIn in the young infants which may lead to further retention of phosphate.
More Related Videos
 08:46
Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
 06:32
Development of Human Renal Tubular Epithelial Cell Primary Cultures in Monolayers and Three-Dimensional Conditions
Published on: June 13, 2025
Related Concept Videos
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
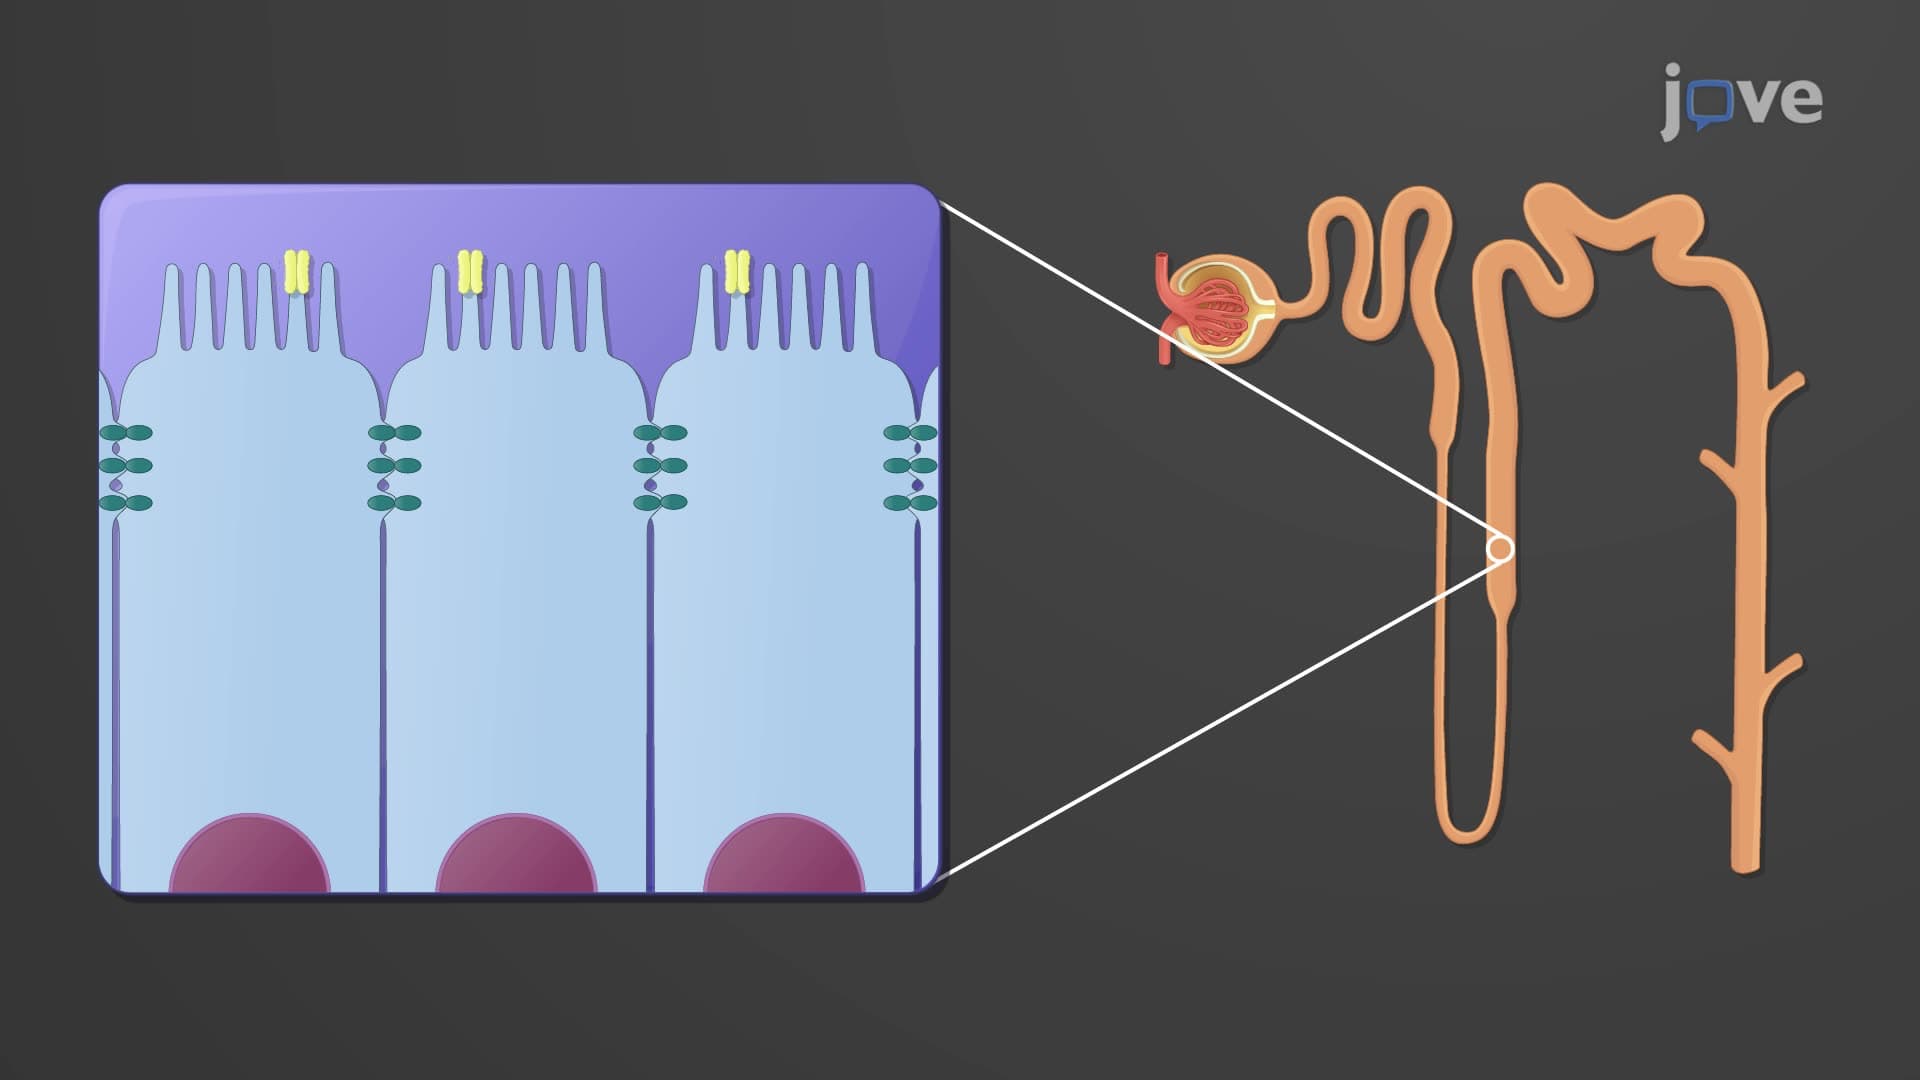
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:28
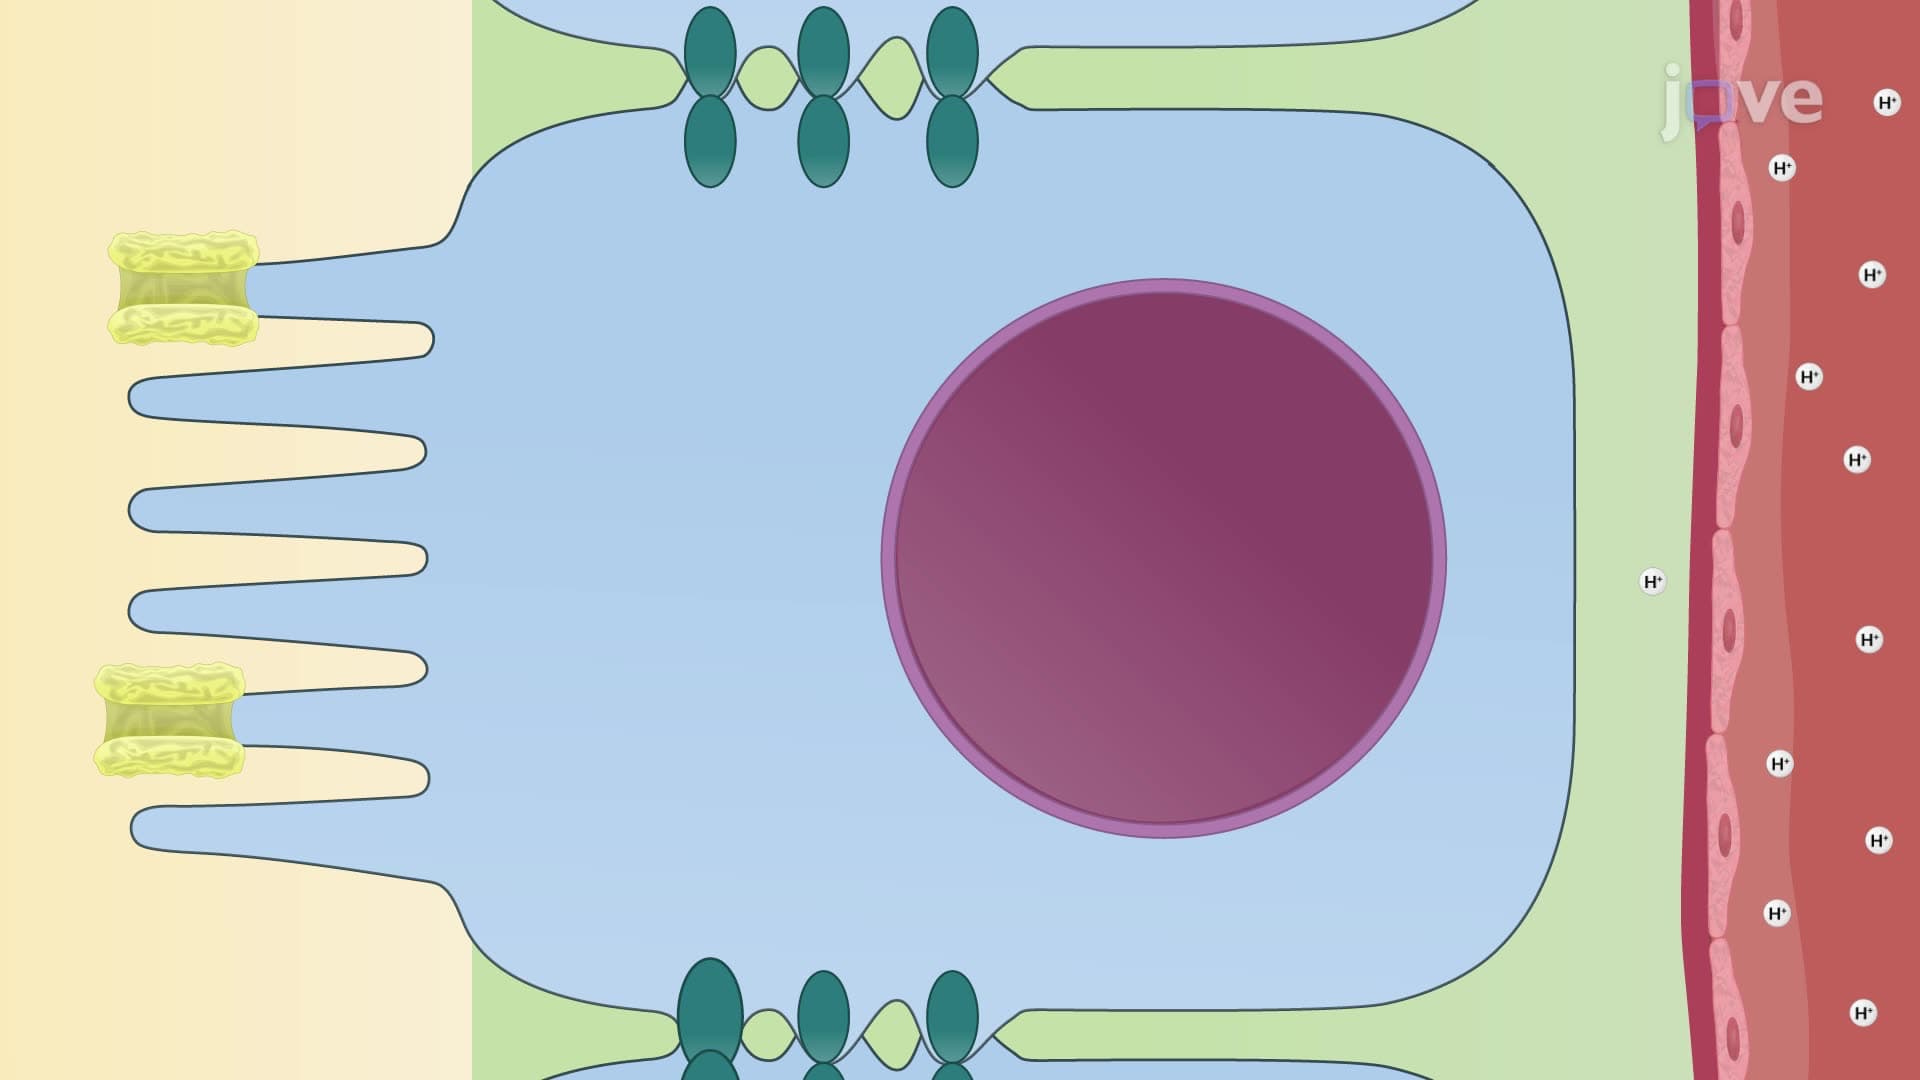
Tubular Reabsorption and Secretion
Tubular reabsorption is a selective process that starts when the filtrate enters the proximal tubules. It involves substances traveling through the transcellular route (through the tubule cell and peritubular...
 01:28
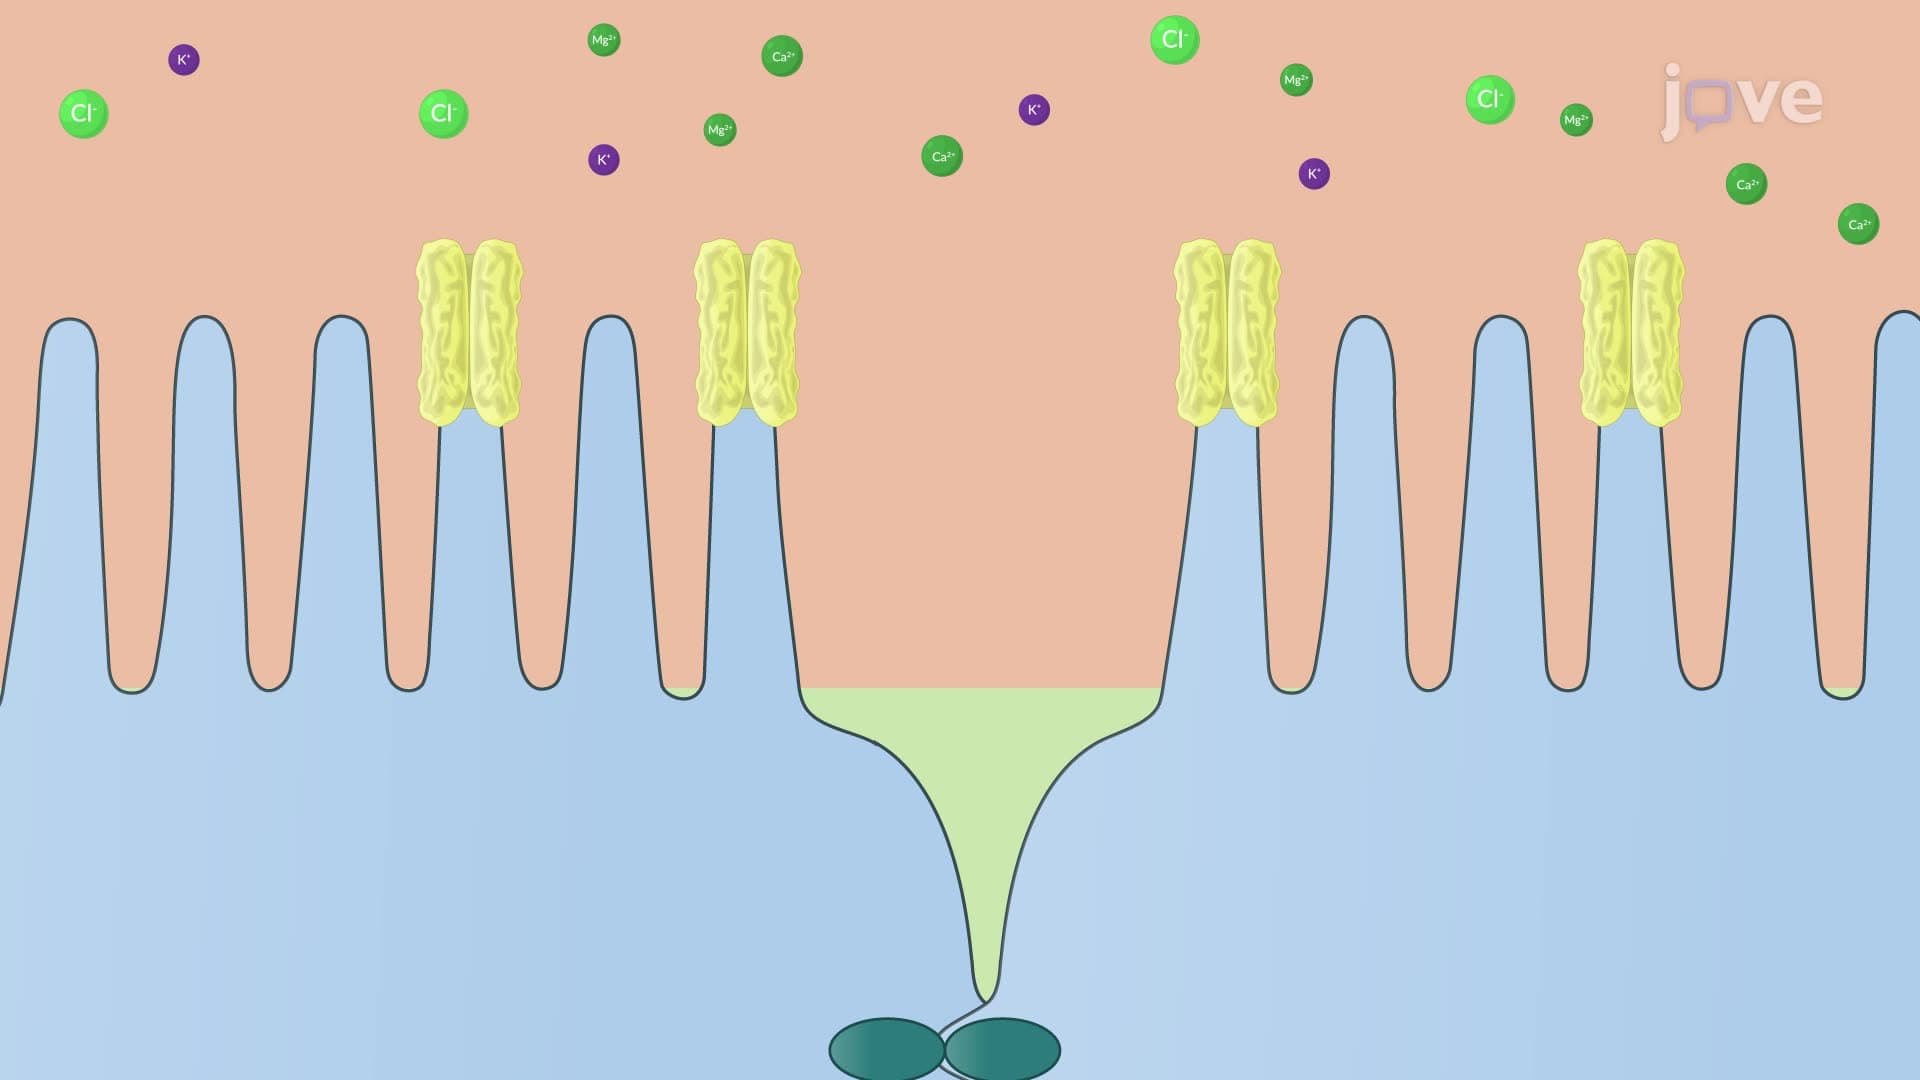
Reabsorption and Secretion in the PCT
Transport mechanisms involving sodium ions (Na+) contribute significantly to solute reabsorption. These mechanisms include symport and antiport processes.
A key example is the...
 01:17
Reabsorption and Secretion in the Loop of Henle
 01:26
Reabsorption and Secretion in the DCT and Collecting Duct
The distal part of the DCT, along with the...
 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion