Related Experiment Video
Updated: Sep 27, 2026


Long-Term Catheterization of the Intestinal Lymph Trunk and Collection of Lymph in Neonatal Pigs
Published on: March 5, 2016
Primary intestinal lymphangiectasia. Case report with radiological and ultrastructural study

Insights
Primary intestinal lymphangiectasia in a teen caused peripheral edema. Dietary changes restricting long-chain triglycerides resolved the edema, stabilizing weight and activity.
Area of Science:
- Gastroenterology
- Pediatrics
- Vascular Biology
Background:
- Primary intestinal lymphangiectasia is a rare condition characterized by lymphatic system abnormalities in the gut.
- It often presents with protein-losing enteropathy, leading to hypoalbuminemia and edema.
Observation:
- A 16-year-old male presented with a 6-week history of peripheral edema.
- Clinical findings included lymphopenia, hypoalbuminemia, steatorrhea, abnormal stool 51Cr-albumin, and imaging showing dilated intestinal lymphatics and lymph node defects.
Findings:
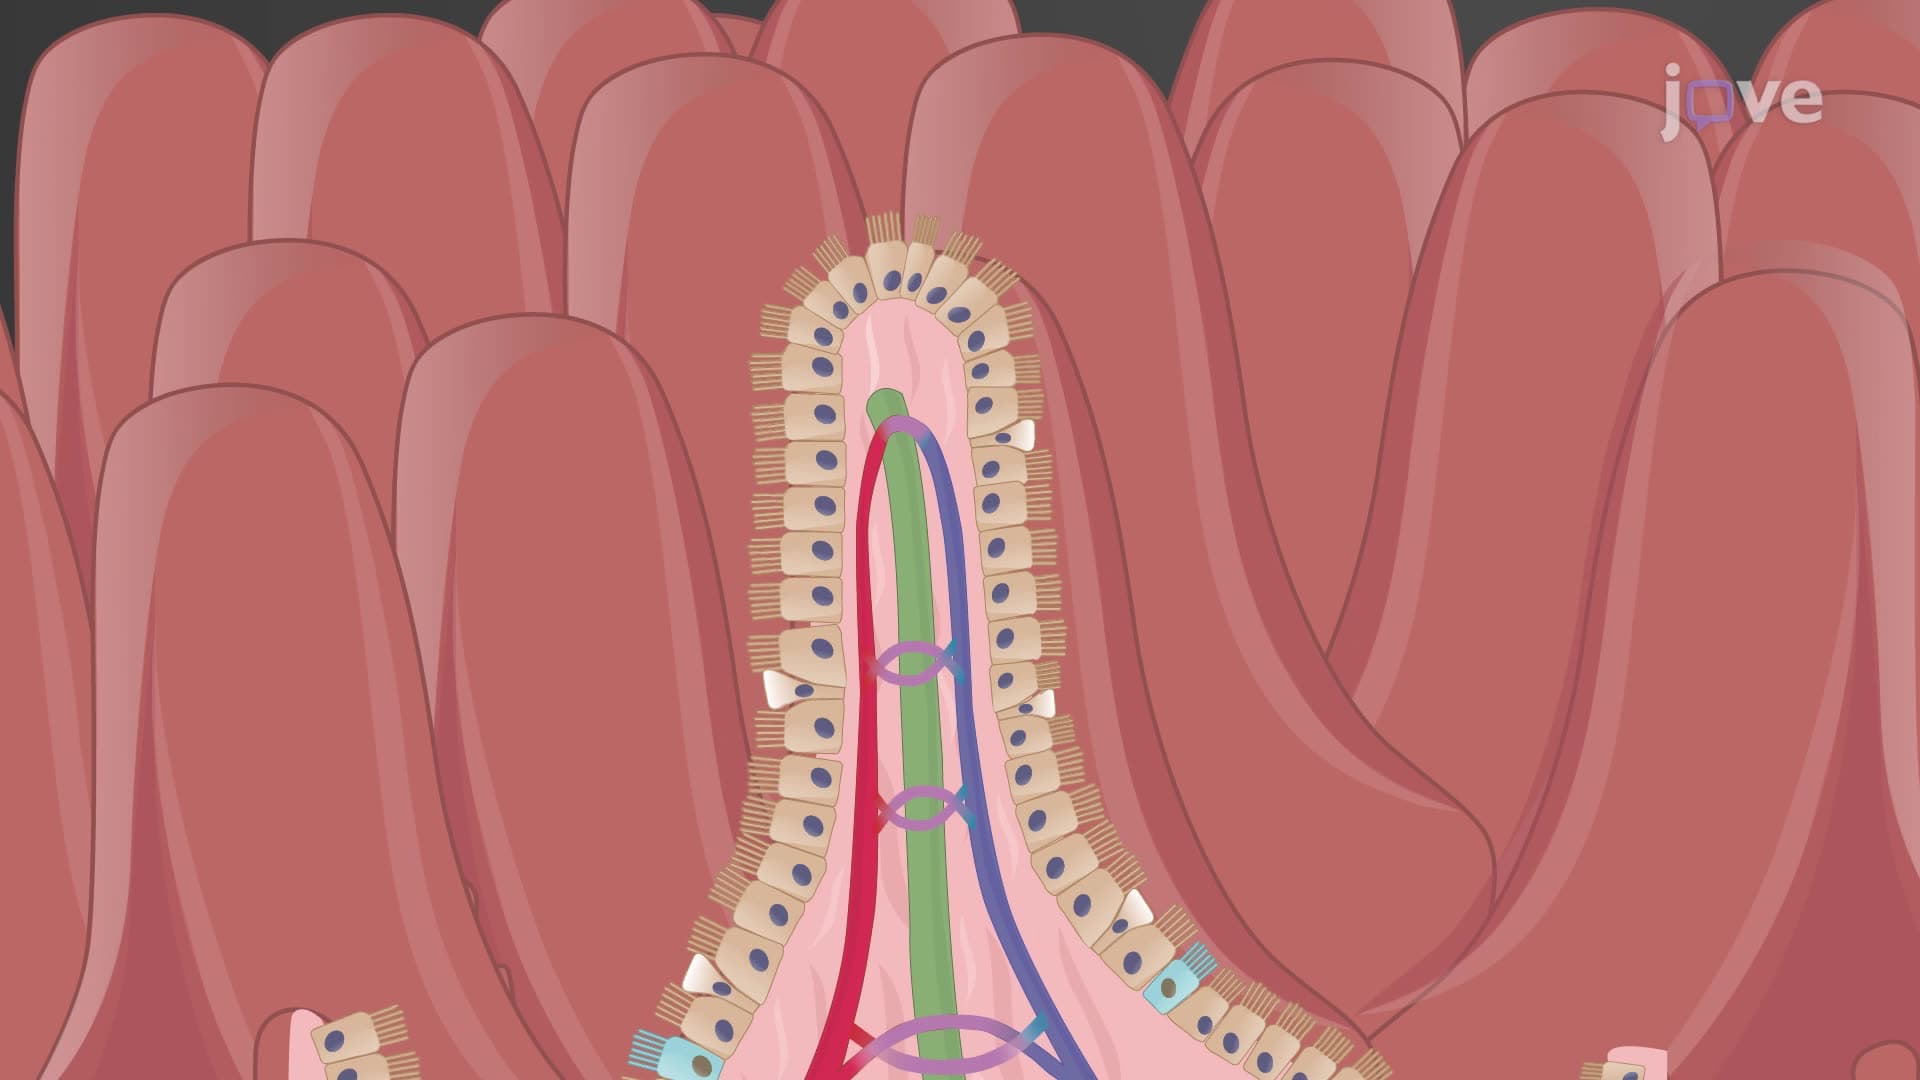
- Small intestinal biopsies revealed dilated lacteals and enterocyte abnormalities.
- Electron microscopy confirmed enlarged lacteals and intercellular vacuoles.
- Exploratory laparotomy identified dilated serosal lymphatic vessels but no masses.
Implications:
- Dietary management, specifically restricting long-chain triglycerides, effectively treated the patient's edema.
- This case highlights the importance of nutritional intervention in managing intestinal lymphangiectasia.
- Early diagnosis and appropriate treatment can lead to significant clinical improvement and normalization of activity.
Abstract:
A 16-year-old boy with primary intestinal lymphangiectasia presented with peripheral edema of 6 weeks duration. Laboratory and radiological studies included absolute lymphopenia, hypoalbuminemia, steatorrhea, abnormal stool 51Cr-albumin value, edema of small intestinal folds, dilated mesenteric lymphatics, as well as bilateral filling defects in external and common iliac lymph nodes. Abdominal CT scan revealed a possible periaortic mass. Small intestinal biopsies demonstrated normal villous architecture with dilated lacteals, and electron microscopy revealed enterocytes with normal as well as blunted microville, enlarged, dilated lacteals and intercellular vacuoles. An exploratory laparatomy was performed and revealed no masses but dilated serosal lymphatic vessels. Medical treatment, including marked restriction of long chain triglyceride intake, resulted in loss of peripheral edema, weight stabilization, and normal activity.