
Clinical significance of exercise-induced ST segment elevation. Correlative angiographic study in patients with

Insights
ST segment elevation during exercise is a key indicator of left ventricular dysfunction in patients with prior myocardial infarction. This stress test finding accurately detects advanced wall motion abnormalities, aiding in diagnosis.
Area of Science:
- Cardiology
- Exercise Physiology
- Diagnostic Imaging
Background:
- Coronary artery disease (CAD) significantly impacts left ventricular function.
- Electrocardiographic (ECG) changes during exercise can reveal underlying cardiac issues.
- Assessing left ventricular wall motion abnormalities is crucial for patient prognosis.
Purpose of the Study:
- To investigate the relationship between ST elevation during treadmill exercise, CAD severity, and left ventricular (LV) wall motion abnormalities.
- To determine the diagnostic value of ST elevation in identifying LV dysfunction post-myocardial infarction.
- To explore the correlation between ST elevation patterns and the extent/location of myocardial infarction and disease.
Main Methods:
- Analysis of 680 patients divided into three groups based on CAD and prior myocardial infarction (MI).
- Treadmill exercise stress testing with 12-lead ECG monitoring.
- Coronary angiography to assess CAD severity and stenoses.
- Echocardiography or ventriculography to evaluate LV wall motion.
Main Results:
- ST elevation during exercise was observed in 1% of patients with CAD, 2% with CAD, and 52% with CAD and prior MI.
- A strong positive correlation existed between ST elevation and LV dysfunction (akinesia, dyskinesia, aneurysm) in patients with prior MI.
- The stress test demonstrated 55% sensitivity and 100% specificity for detecting wall motion abnormalities, with sensitivity increasing with LV dysfunction severity.
- Maximal ST elevation (≥3 mm) was linked to dyskinesia or aneurysm.
- ST elevation incidence correlated with MI location: 85% in anterior MI vs. 33% in inferior MI.
Conclusions:
- ST segment elevation during exercise is a sensitive and specific marker for advanced left ventricular asynergy in patients with prior myocardial infarction.
- The ST segment response during exercise reflects a spectrum of myocardial asynergy and additional coronary artery disease.
- Utilizing multiple ECG leads is essential for comprehensive assessment of ST segment responses during stress testing.
Abstract:
We have examined the relation between electrocardiographic ST elevation during treadmill exercise (greater than or equal to 1 mm, using the conventional 12 leads), the severity of coronary artery disease, and left ventricular wall motion abnormalities in 680 patients. They were divided into three groups: (1) 218 patients with clinically significant coronary artery disease, (2) 178 patients with clinically significant coronary artery disease, and (3) 284 patients with clinically significant coronary artery disease and previous myocardial infarction. ST elevation during exercise (predominantly in lead V2) was seen in two patients (1%) in group 1, three patients (2%) in group 2, and 147 patients (52%) in group 3. Coronary artery disease (number of vessels involved and severity of stenoses) was comparable in groups 2 and 3. All the patients in group 1 showed a normal left ventricular contraction pattern; 64% of the patients in group 2 showed wall motion abnormalities (predominantly hypokinesia) and 95% of group 3 (mainly akinesia, dyskinesia, or aneurysm). A strongly positive correlation was seen between the ST elevation and left ventricular dysfunction in patients belonging to group 3. The overall sensitivity and the specificity of the stress test in detecting wall motion abnormalities was 55% and 100% respectively. The sensitivity increased with deterioration in left ventricular function, reaching 81% and 90% in patients with dyskinesia and aneurysm, respectively. Maximal ST elevation (greater than or equal to 3 mm) was confined to the patients with dyskinesia or aneurysm. The incidence of ST elevation during exercise was also related to the location of previous infarction, showing a positive response in 85% of patients with anterior myocardial infarction and in only 33% with inferior myocardial infarction. We conclude that ST segment elevation during exercise in patients with previous myocardial infarction is a sensitive and a specific indicator of advanced left ventricular asynergy. The ST segment response during exercise in patients with previous infarction and with angiographically demonstrated myocardial asynergy appears to be a continuous spectrum. A normal ST segment response or elevation alone usually signifies involvement of only one vessel supplying the infarcted myocardium, ST elevation with concomitant ST depression indicates additional coronary artery disease, and ST depression alone indicates overwhelming myocardial ischaemia resulting from multiple vessel disease. The employment of multiple leads is essential to obtain this information.
More Related Videos
 07:40
Impact of High-intensity Interval Exercise and Moderate-Intensity Continuous Exercise on the Cardiac Troponin T Level at an Early Stage of Training
Published on: October 10, 2019
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
Related Concept Videos
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and narrowing...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:26
Exercise Stress Test
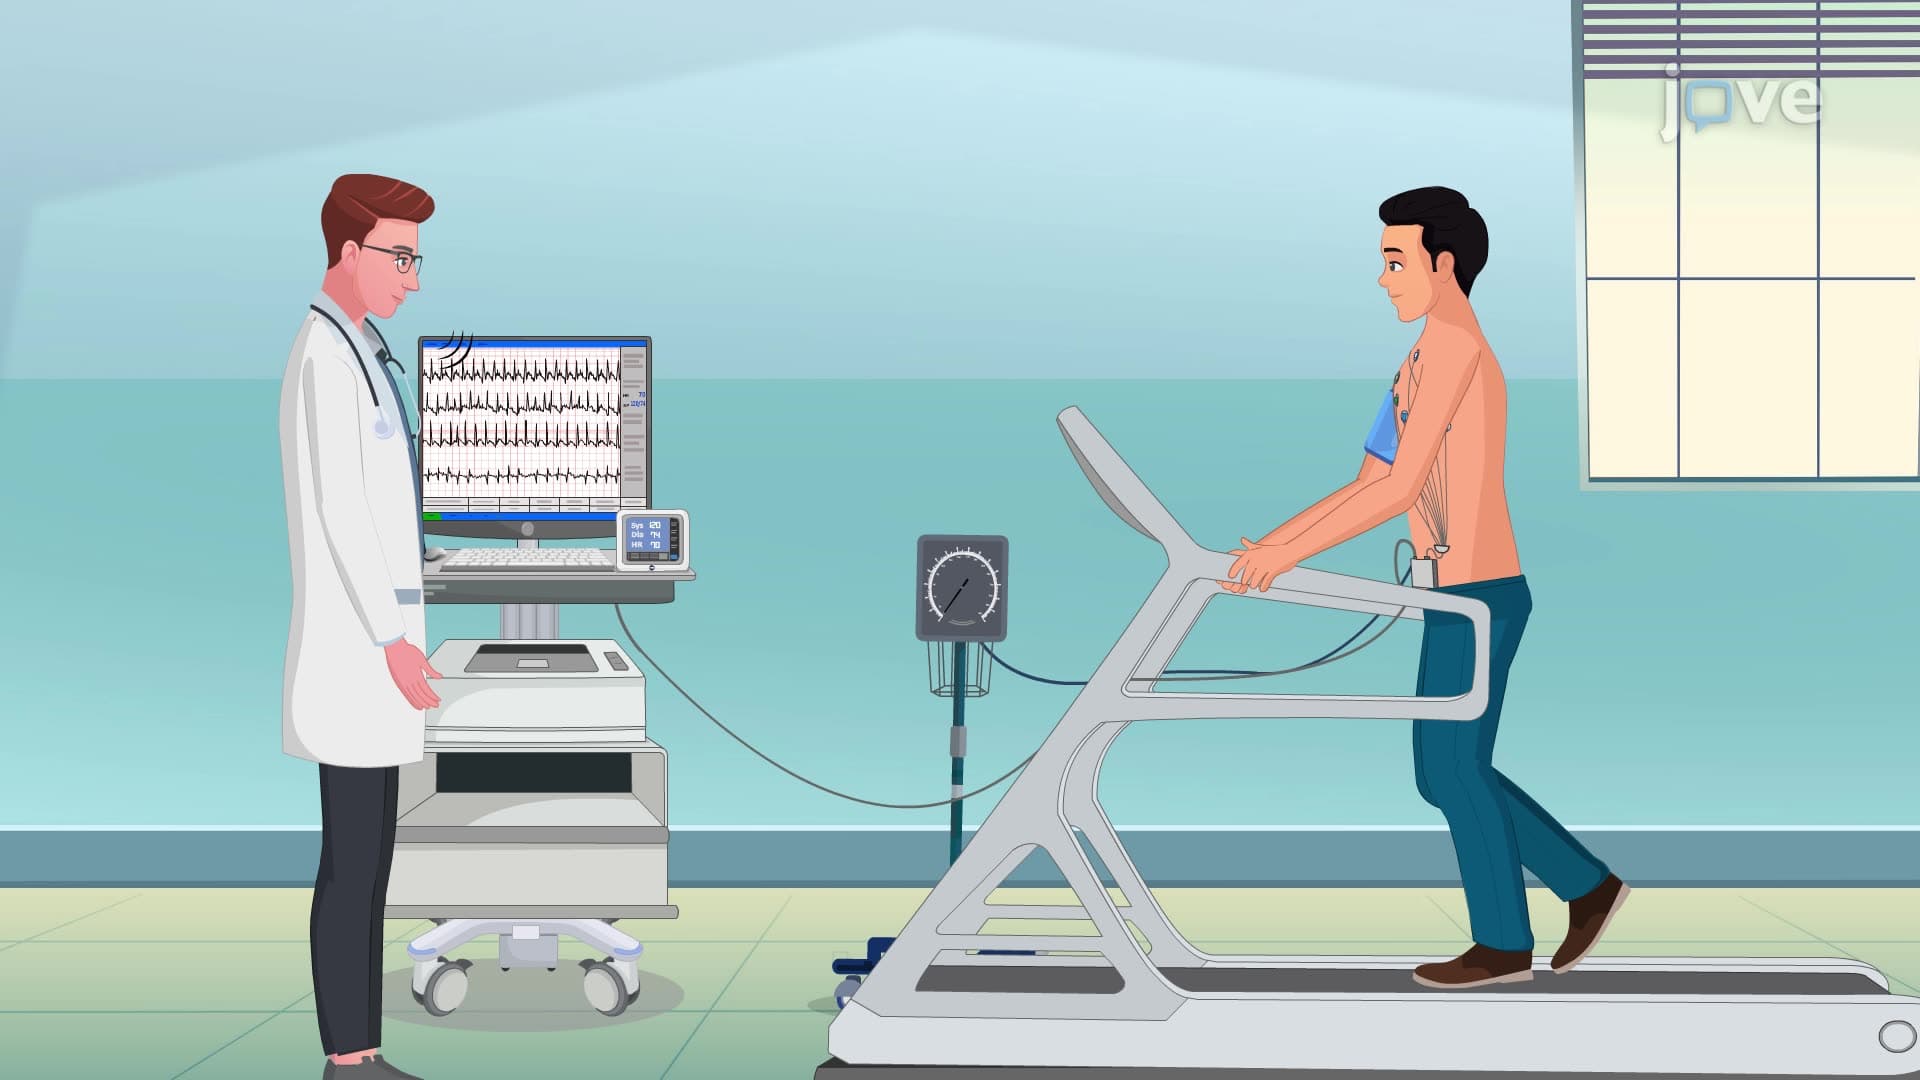
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies