Related Experiment Video
Updated: Sep 25, 2026


Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Effect of adenosine on the relaxation of coronary arteries at varying pH values

Abstract:
The efficiency of adenosine to relax the bovine coronary arterial strips increased significantly by lowering the bath pH from 7.4 to 6.8 (CO2 or HCO-3). The large vessels (3-4 mm O.D.) relaxed with greater significance at higher concentrations of adenosine, whereas small vessels (0.5-0.7 mm O.D.) relaxed better at low concentrations of adenosine. Theophylline and 8-phenyltheophylline competitively inhibited the effect of adenosine. 8-phenyltheophylline was found to be a better antagonist than theophylline. Furthermore, binding assays with 2-3H adenosine displayed a single species of binding sites. The Kd was 3 X 10(-6) M and 4 X 10(-6) M, while Bmax was 48 and 19 pmoles/mg protein for small and large vessels, respectively. The antagonistic effect of theophylline and 8-phenyltheophylline was not affected by pH variations. It is concluded that relaxation of coronary arteries by adenosine is affected by pH variations.
More Related Videos

Related Concept Videos
 01:31
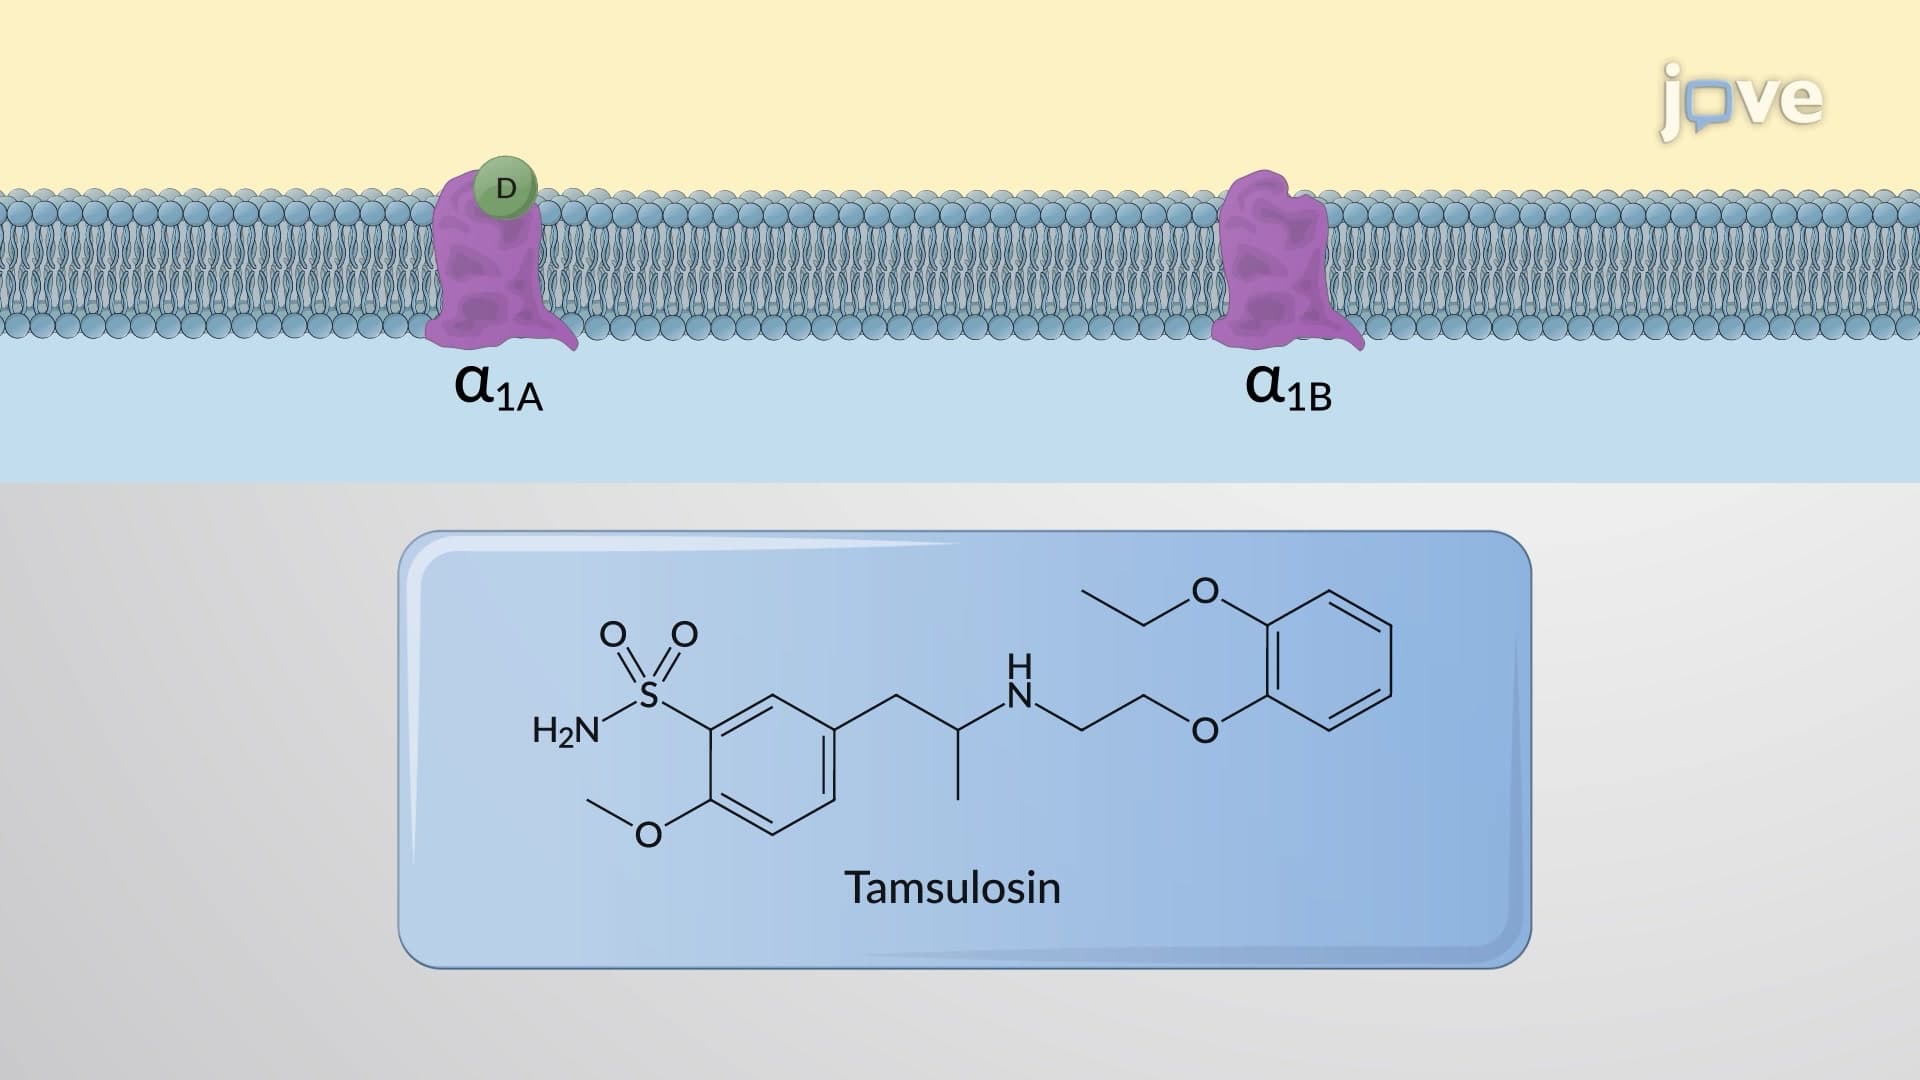
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
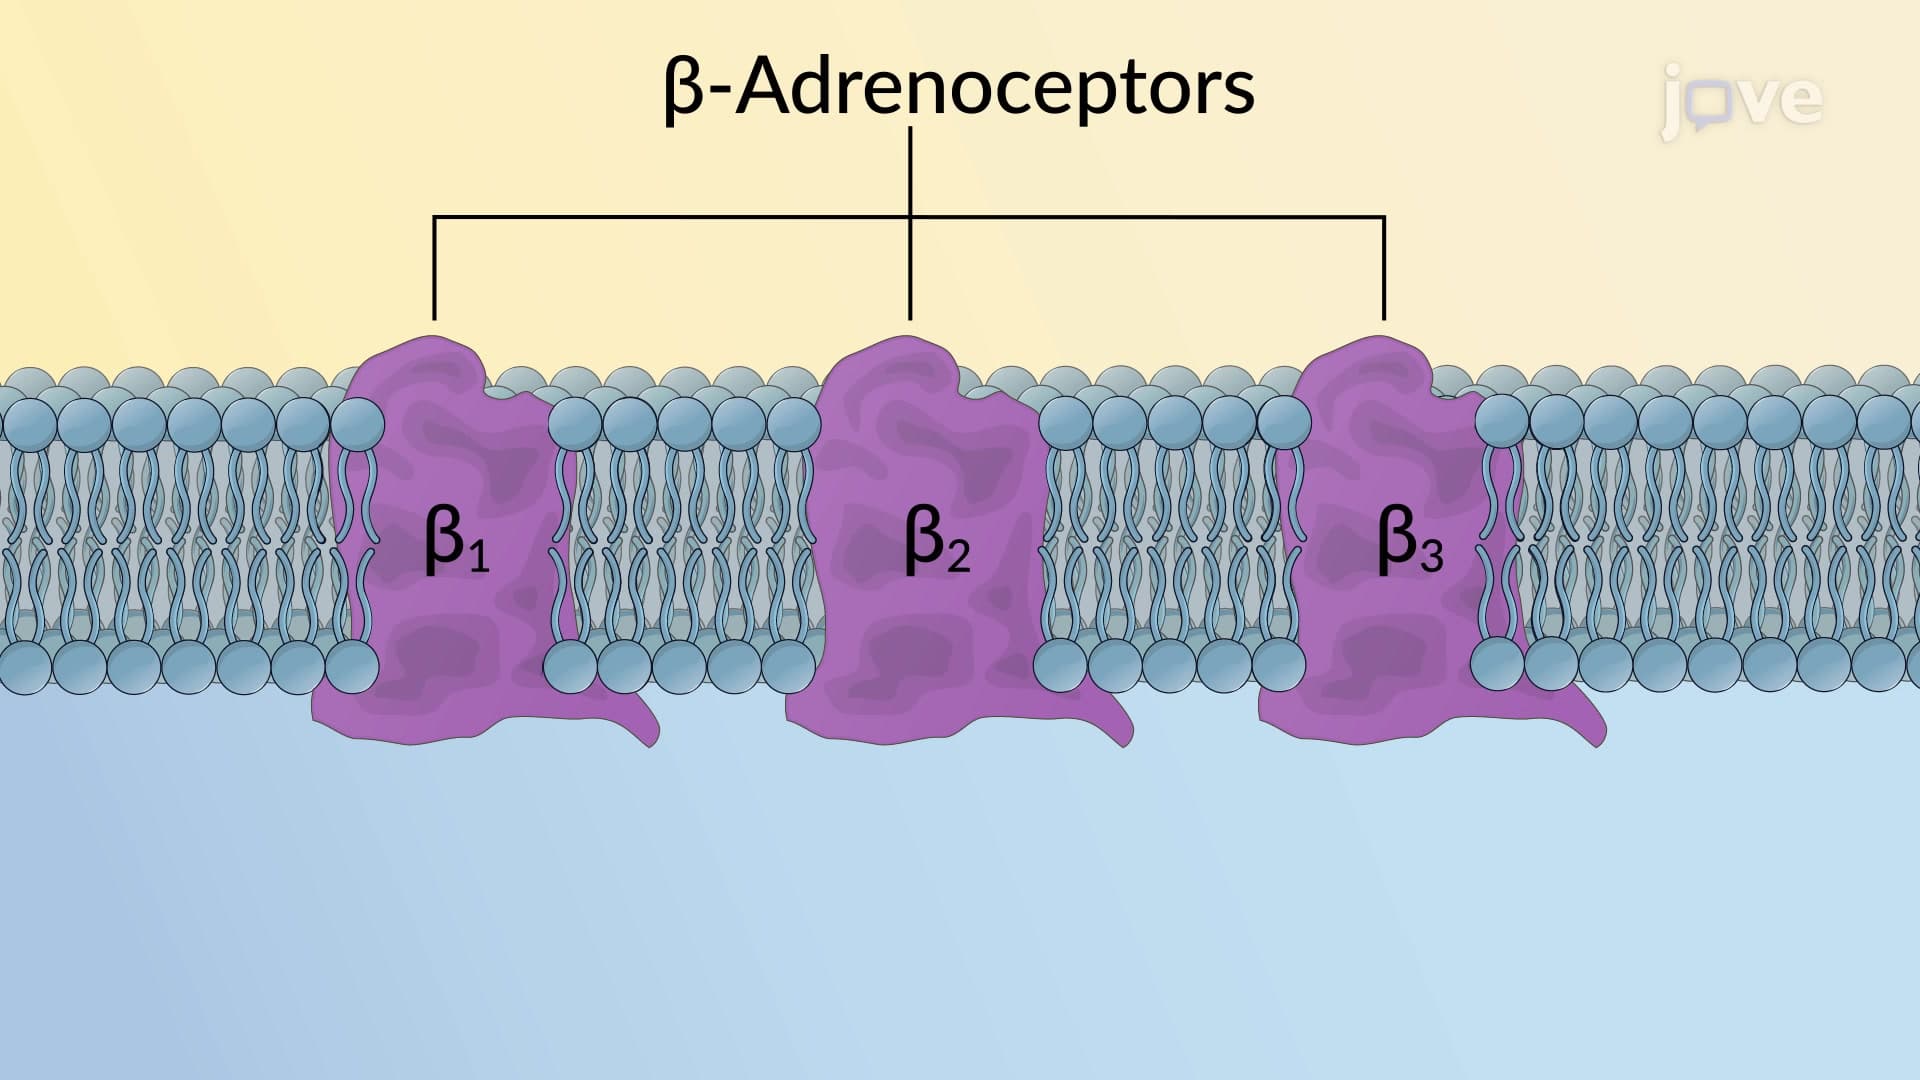
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...