Related Experiment Video
Updated: Aug 6, 2026

05:50

International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
Extrapleural empyema thoracis as a direct extension of Ludwig's angina. Case report
The Journal of Thoracic and Cardiovascular Surgery
|July 1, 1980

Abstract:
The following case report describes a previously unreported cause of extrapleural empyema thoracis, namely, direct extension of a submandibular abscess, which occurred following dental extraction and presented initially as Ludwig's angina.


Related Concept Videos
 01:13
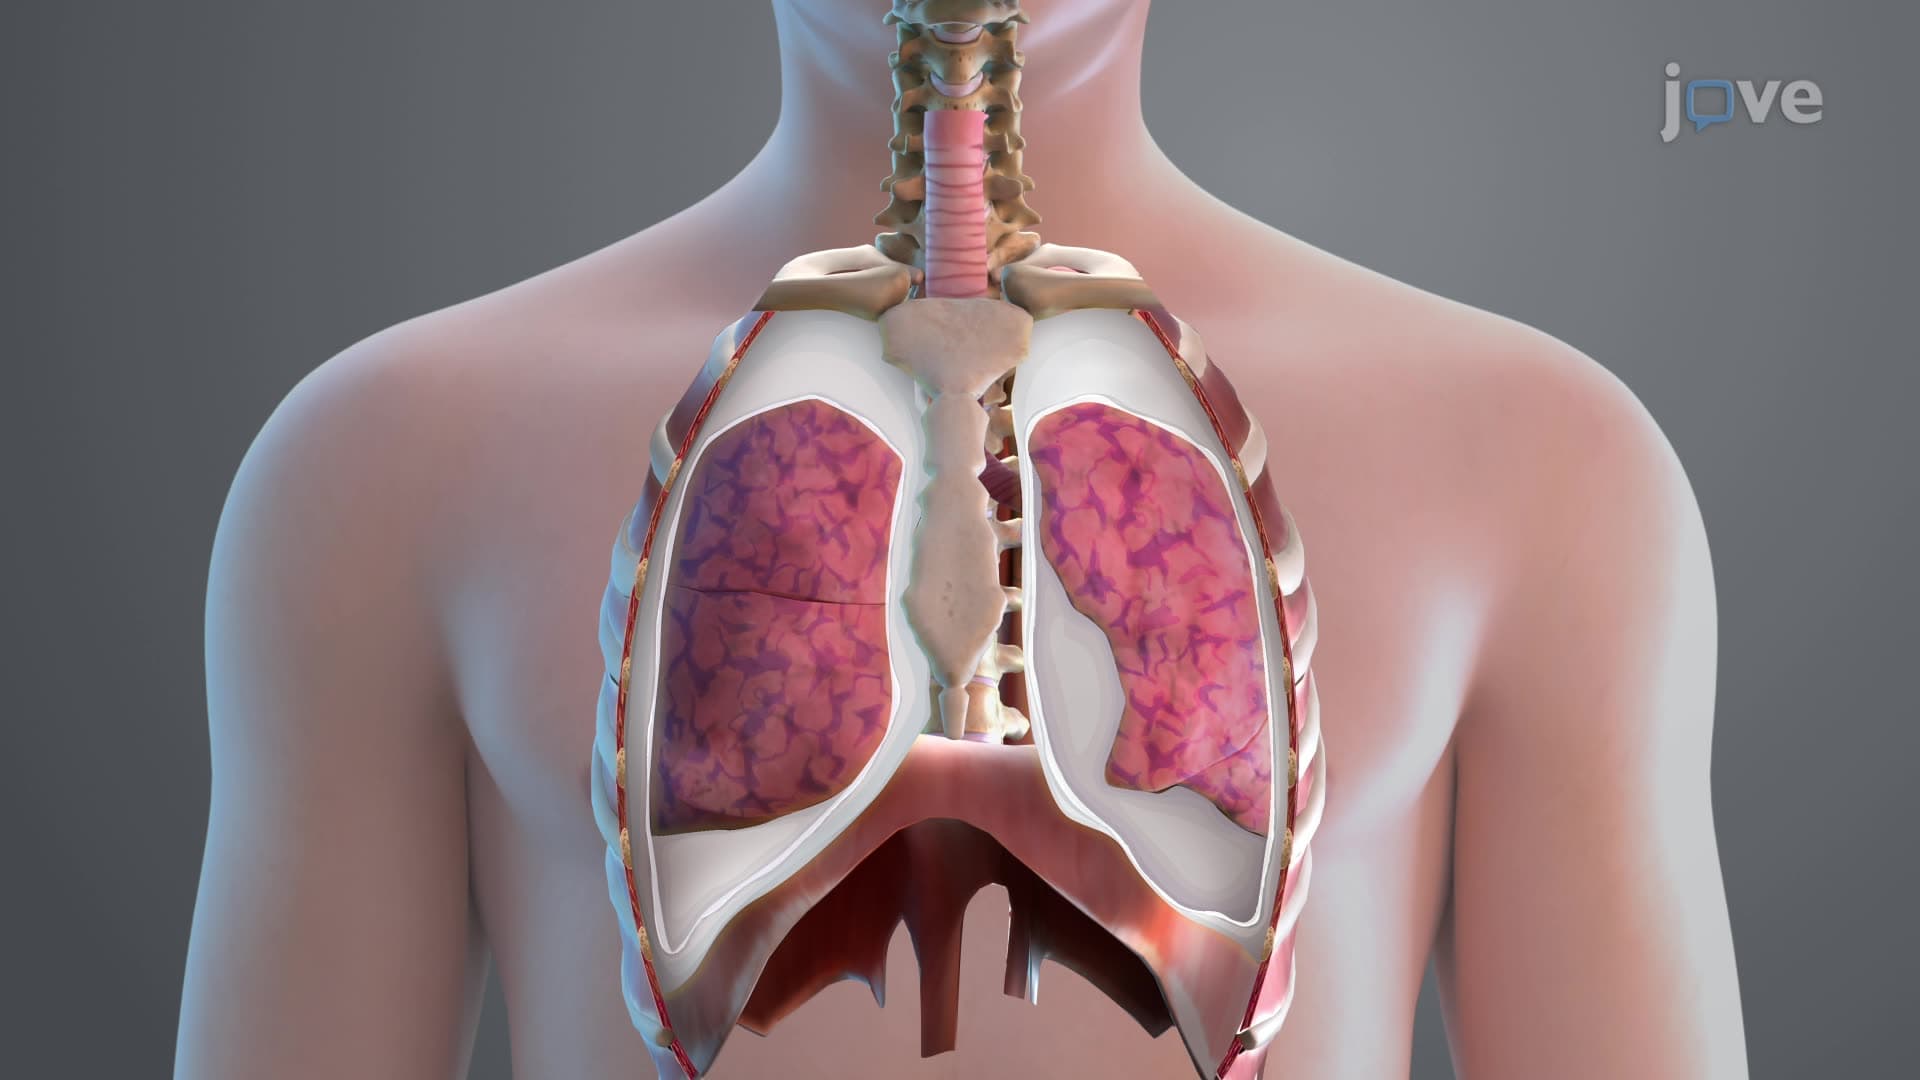
Pleura of the Lungs
The lungs are nestled in a cavity, shielded by the pleura. The pleura, a form of serous membrane, wraps around each lung. This membrane arrangement consists of two layers: the visceral and parietal pleurae. The visceral pleura lines the surface of the lungIn contrast, the parietal pleura is the outer layer and contacts to the thoracic wall, the mediastinum, and the diaphragm. The hilum is the point of connection between the visceral and parietal layers. The space between the parietal and...
 01:28
Pleural Effusion II: Symptoms and Management
Pleural Effusion Overview
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:27
Pneumothorax-II
Pneumothorax is a medical condition defined by the buildup of air in the pleural space between the lungs and the chest wall. This accumulation of air can lead to partial or complete lung collapse, resulting in a range of clinical manifestations. Understanding the clinical presentation and effective management strategies is crucial for healthcare professionals in providing timely and appropriate care to individuals with pneumothorax.
Clinical Manifestations:
Clinical Manifestations:
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Esophageal perforations manifest in various clinical forms, influenced by factors such as the perforation's cause and location (cervical, intrathoracic, or intra-abdominal), the extent of contamination, and potential injury to adjacent mediastinal structures. The timing between the perforation occurrence and treatment initiation also affects the clinical presentation.
Clinical Manifestations:
Clinical Manifestations:
 01:29
Pulmonary Embolism I: Introduction
Pulmonary embolism (PE) occurs when a thrombus, fat or air embolus, amniotic fluid, or tumor tissue blocks one or more pulmonary arteries. These blockages originate in the venous system or the right side of the heart.EtiologyPE primarily arises from deep vein thrombosis (DVT) and other hypercoagulable states, such as inherited thrombophilias. Additional etiological factors include venous stasis, commonly seen in obesity, and endothelial injury from surgery and trauma. Less common causes include...
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.