Small-intestine length in infants and children
Related Experiment Video
Updated: Aug 13, 2026

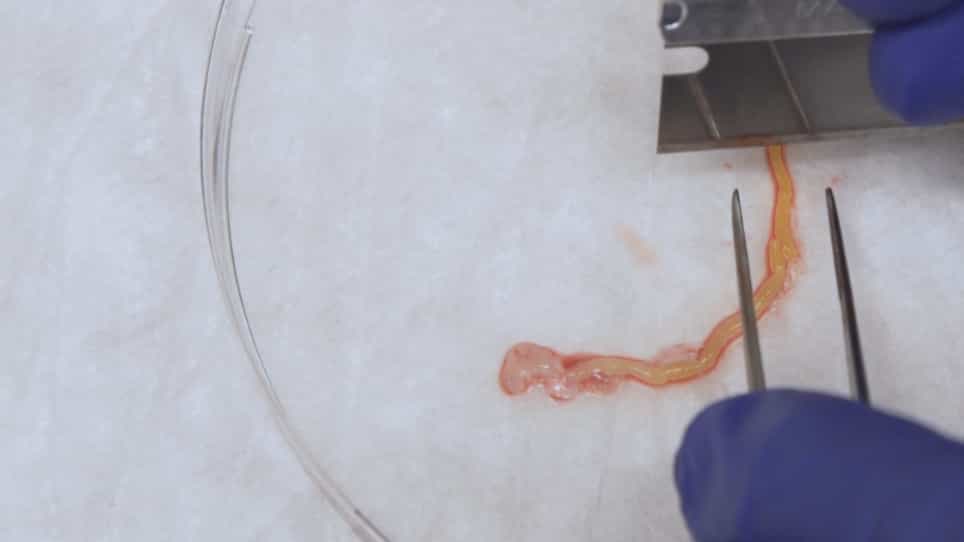
Tissue Engineering of the Intestine in a Murine Model
Published on: December 1, 2012

Insights
Small intestine length in children grows rapidly until 60 cm body length, then plateaus. No significant differences were found across diagnostic groups, though some cases showed abnormal small intestine lengths.
Area of Science:
- Pediatric Gastroenterology
- Human Anatomy
- Growth and Development
Background:
- Accurate measurement of pediatric gastrointestinal anatomy is crucial for diagnosing and managing various conditions.
- Understanding normal small intestine length variations in children is essential for clinical interpretation.
Purpose of the Study:
- To establish reference standards for small intestine length in infants and children.
- To investigate potential correlations between small intestine length and patient age, body size, and diagnostic categories.
Main Methods:
- Measurement of small intestine length (ligament of Treitz to ileocecal valve) in 183 pediatric patients.
- Correlation analysis with crown-heel length and categorization into diagnostic groups (congenital heart disease, abdominal lesions, miscellaneous).
Main Results:
- Rapid intestinal elongation observed up to 60 cm crown-heel length.
- Intestinal length remained constant between 100-140 cm body length.
- No statistically significant differences in small intestine length were found among the diagnostic categories.
- Several cases presented with notably elongated or shortened small intestines.
Conclusions:
- Established growth patterns for small intestine length in pediatric populations.
- Body length is a key determinant of small intestine length in children.
- While overall group differences were not significant, individual variations highlight the importance of considering specific patient anatomy.
Abstract:
Small-intestine length from ligament of Treitz to ileocecal valve was measured in 183 infants and children ranging up to 15 years of age. Elongation of the intestine was rapid until crown-heel length was 60 cm and remained constant from 100 to 140 cm of body length. When patients were placed into three general diagnostic categories (congenital heart disease, abdominal lesions, and miscellaneous) no significant differences were found. However, several striking instances of abnormally long or short small intestines were encountered.

Related Concept Videos
 01:23
Anatomy of the Intestines
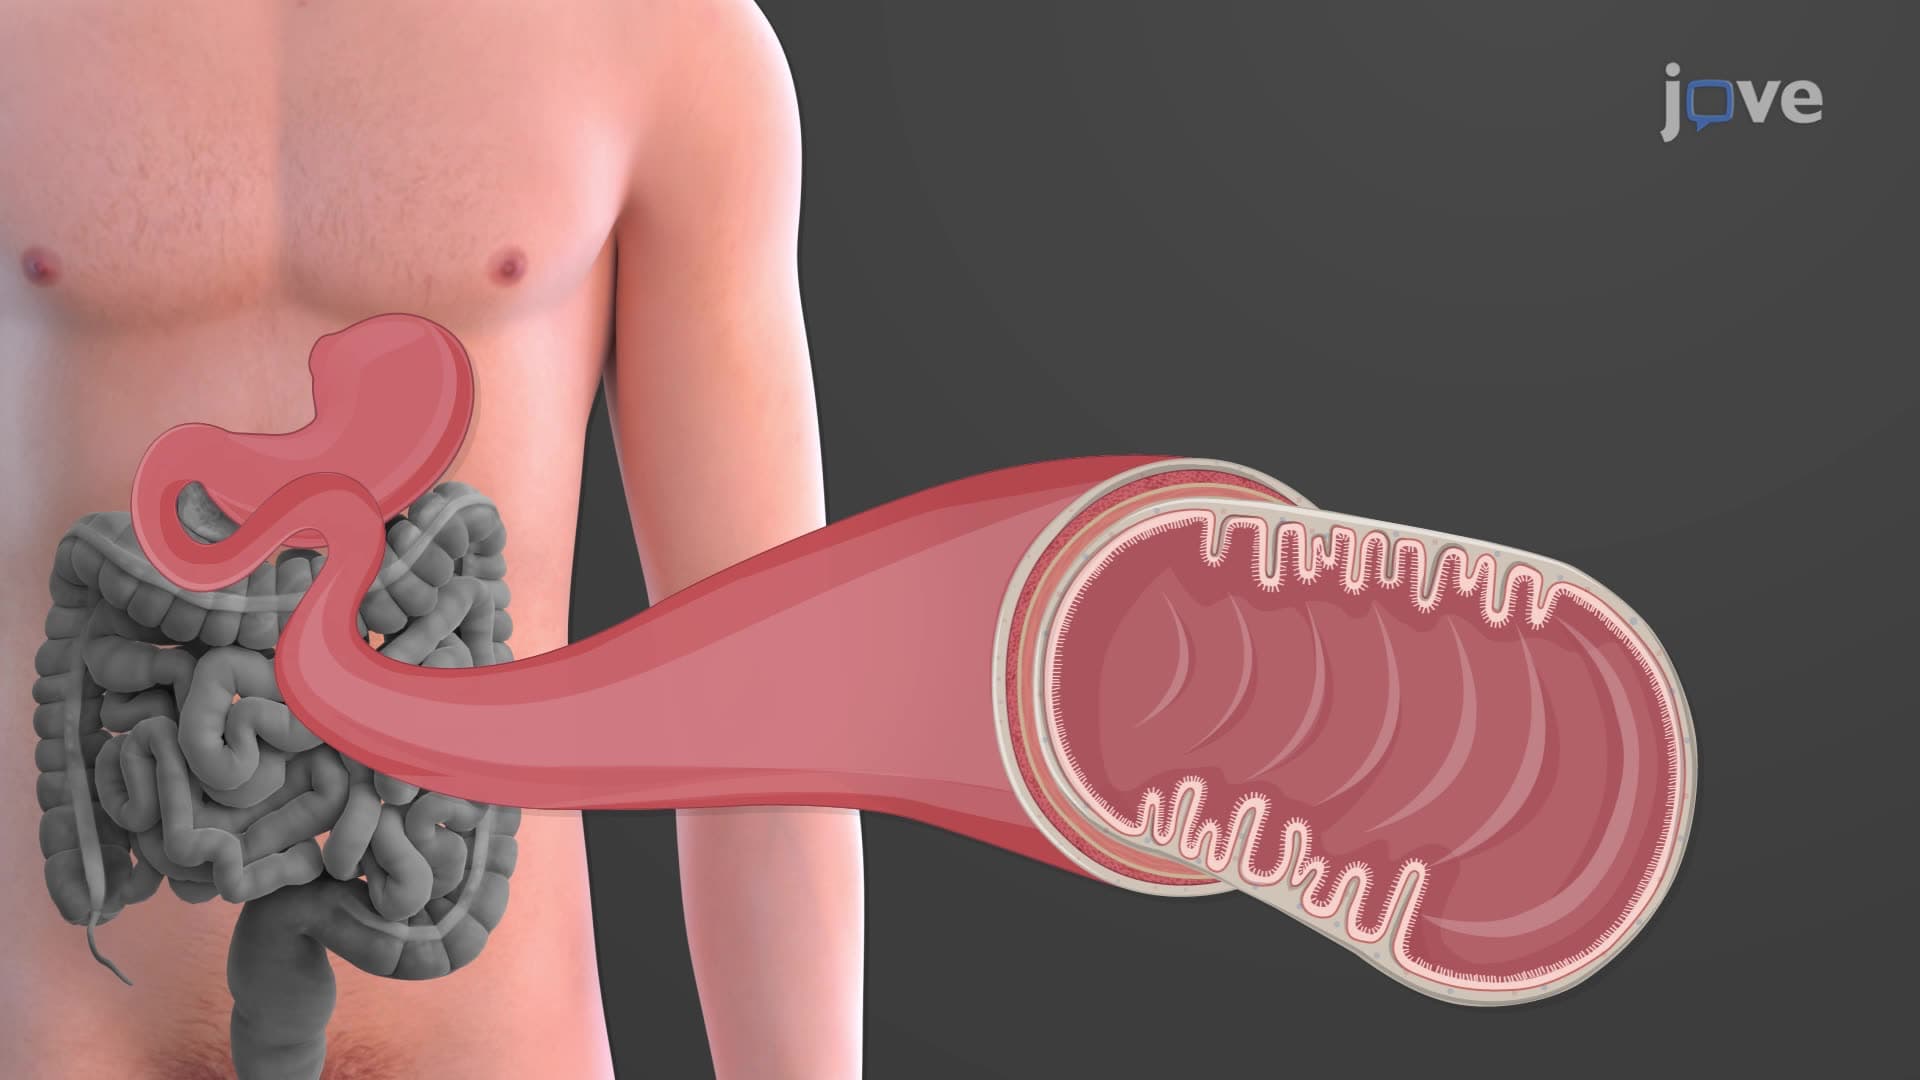
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the small...
 01:23
Renewal of Intestinal Stem Cells
 01:15
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique C-shape wraps...
 01:27
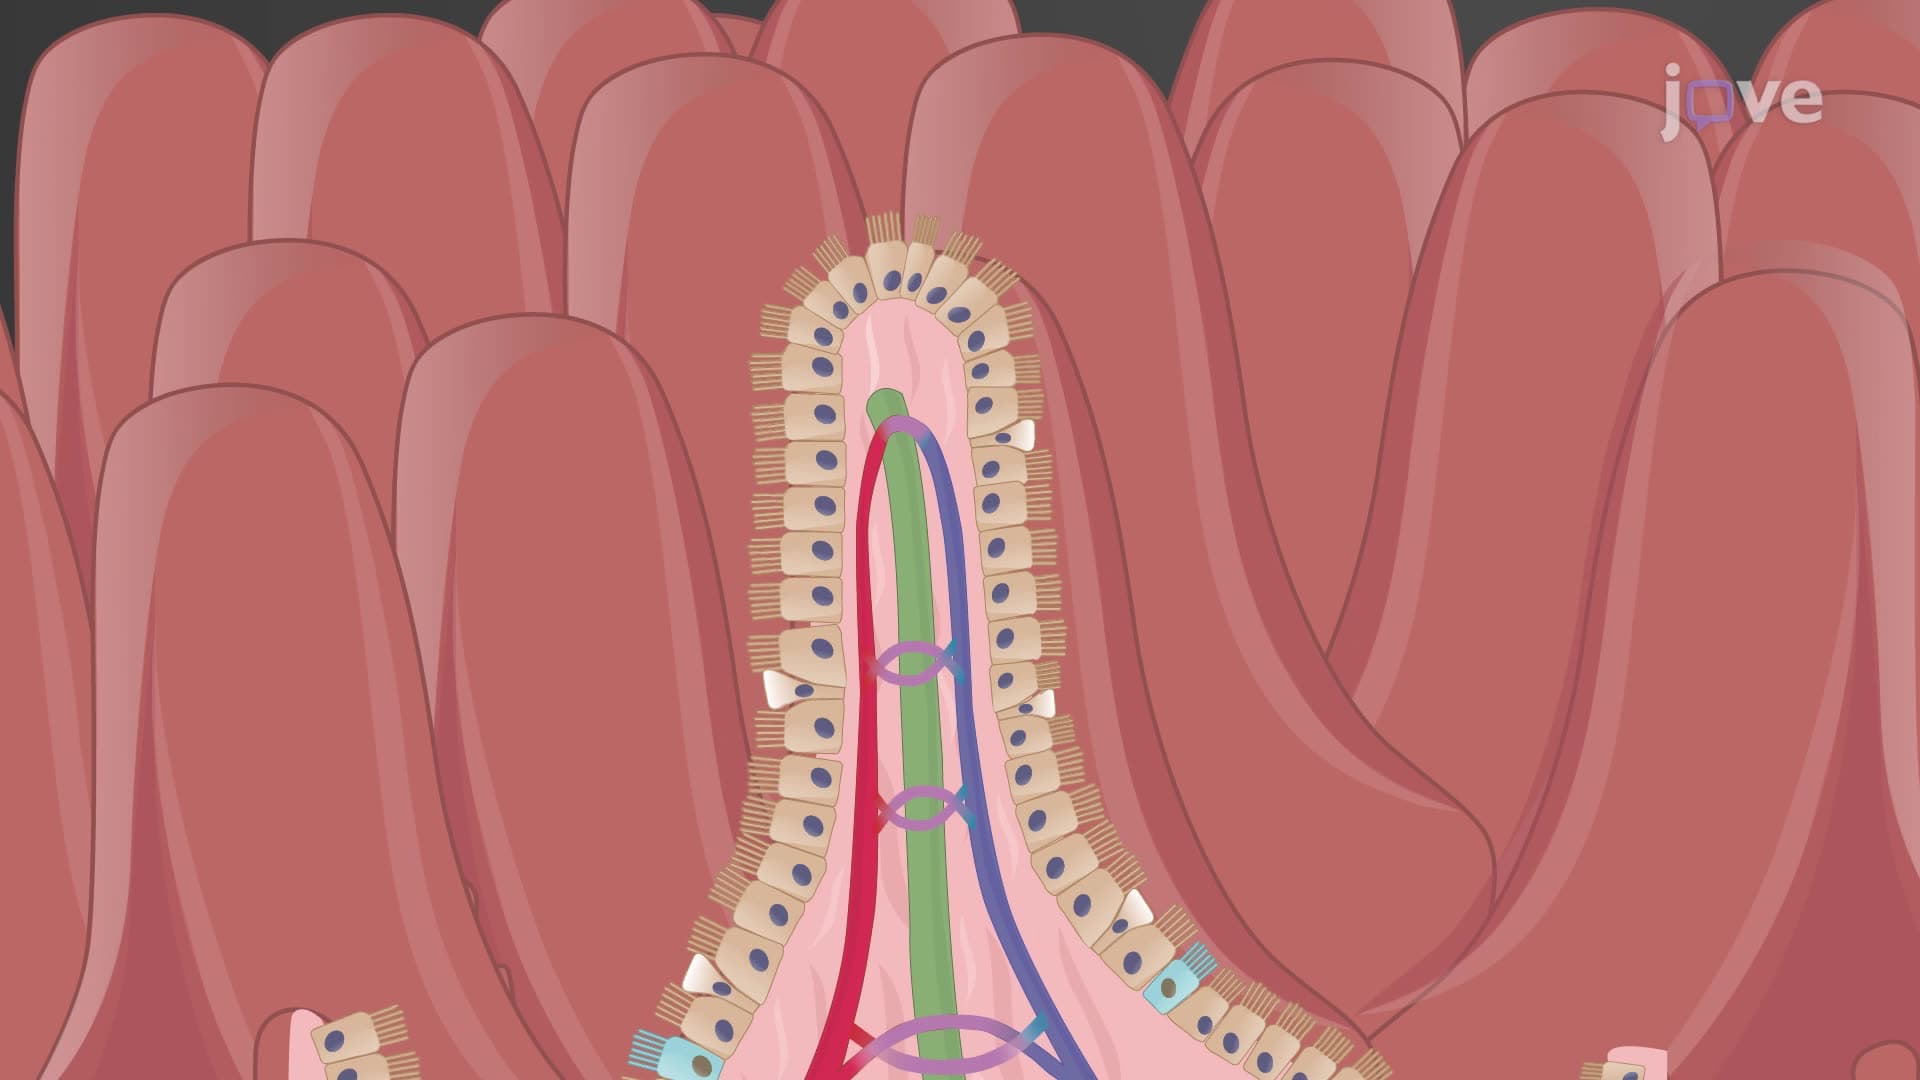
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption