Related Experiment Video
Updated: Jul 26, 2026

10:20
In vitro Measurements of Tracheal Constriction Using Mice
Published on: June 25, 2012
Physiologic features of the canine esophagus: effects of tranquilization on esophageal motility
American Journal of Veterinary Research
|May 1, 1980

Abstract:
Esophageal motility was studied in clinically normal dogs. Mean values as to the time and pressure functions of esophageal peristaltic pressure curves are presented. Effects of two dosage levels of tranquilization on the time and pressure functions are reported.


Related Concept Videos
 01:28
Drugs Affecting GI Tract Motility: Dopamine Receptor Antagonists
Prokinetic agents are specialized medications that stimulate gastrointestinal (GI) motility, promoting food movement through the GI tract. Dopamine, an inhibitory neurotransmitter, plays a significant role in this process, reducing GI motility and indirectly controlling the speed of digestion. Dopamine receptor antagonists, such as metoclopramide and domperidone, offer a unique advantage as prokinetic agents. By blocking the dopamine receptors, these drugs increase GI motility, improving food...
 01:23
Drugs Affecting GI Tract Motility: Serotonin Receptor Agonists
Serotonin, a crucial neurotransmitter synthesized by enterochromaffin cells, plays a cardinal role in regulating gastrointestinal (GI) motility. With over 90% of the body's total serotonin in the GI tract, its influence on digestive processes is profound. Serotonin is swiftly released upon various stimuli, such as food boluses or certain drugs, triggering intrinsic sensory neurons in the myenteric plexus and extrinsic vagal and spinal sensory neurons. This leads to the activation of the...
 01:24
Esophagus
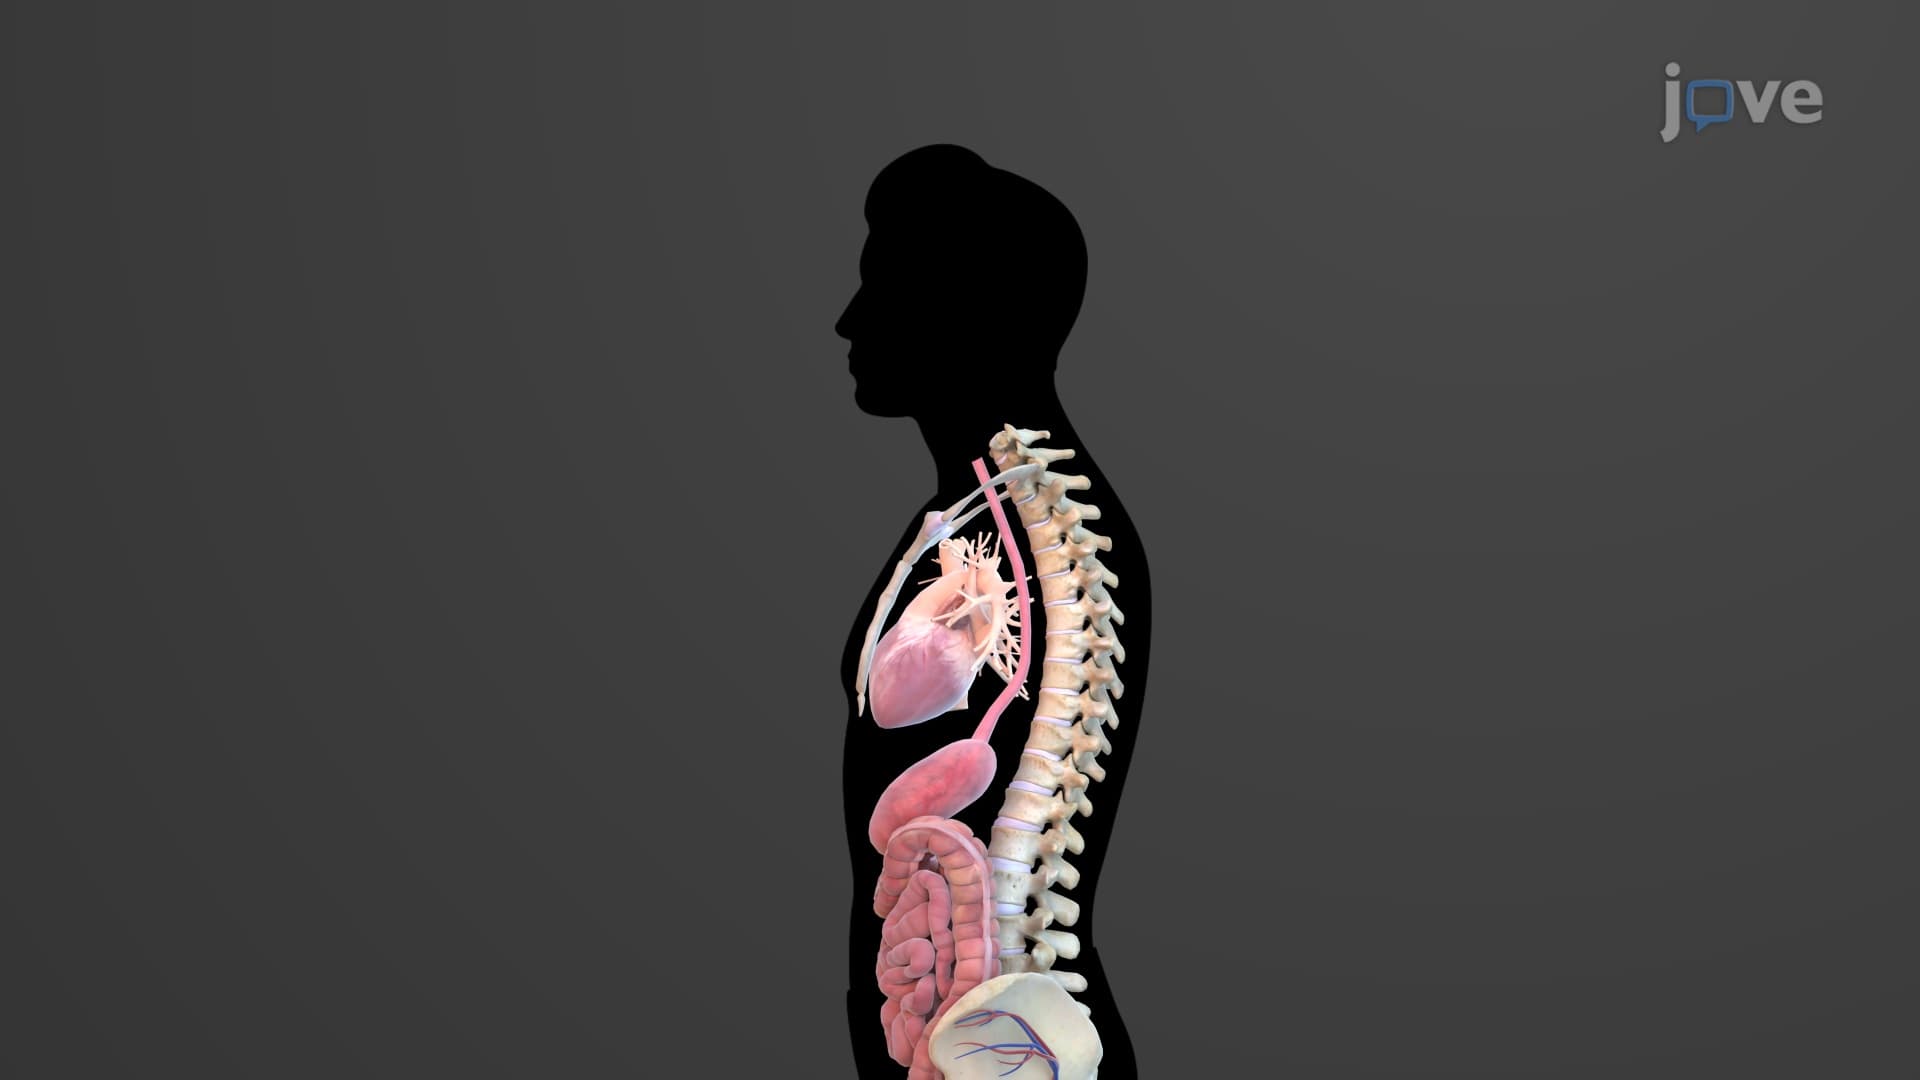
The esophagus, a muscular conduit linking the pharynx and stomach, measures roughly 10 inches (25.4 cm) and sits behind the trachea. It remains collapsed when not swallowing. The esophagus follows a predominantly straight path through the thoracic mediastinum and enters the abdominal cavity through a diaphragmatic opening known as the esophageal hiatus.
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:30
Esophageal Strictures-I: Introduction
Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Patients with esophageal strictures often experience a range of symptoms. Initially, they may have difficulty swallowing solid foods, which can progress to include liquids. Additional symptoms may involve chest pain or discomfort, regurgitating food and fluids, heartburn, unintentional weight loss, coughing or choking during meals, and hoarseness.
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:27
Esophageal Achalasia
Esophageal achalasia is a chronic neurogenic disorder characterized by impaired relaxation of the lower esophageal sphincter (LES) and absent or ineffective peristalsis in the distal esophagus. This leads to a functional obstruction without a physical blockage, despite significant disruption of esophageal motility.EtiologyAchalasia is caused by degeneration of the myenteric (Auerbach's) plexus, specifically the loss of inhibitory ganglion cells that produce vasoactive intestinal peptide (VIP)...