Leucocyte electrolytes and sodium efflux rate constants in the hypertension of pre-eclampsia

1. Leucocyte electrolytes were measured in pre-eclampsia and comparison was made with leucocytes from normal primigravidae and from the original pre-eclamptic subjects 6 months after delivery when blood pressure had returned to normal. 2. In pre-eclamptic subjects, leucocyte sodium was elevated and potassium depressed, and the rate constant for sodium efflux was depressed. 3. These changes returned to normal after delivery. 4. An increase in cellular sodium as a result of altered sodium pump activity may be the cause of hypertension in pre-eclampsia.

Related Concept Videos

Antihypertensive Drugs: Action of Diuretics01:16

Antihypertensive Drugs: Action of Diuretics

Diuretics are antihypertensive drugs used to treat hypertension resulting from sodium and water retention. Sodium, vital for fluid balance and nerve or muscle function, is regulated by the kidneys through millions of nephrons. Blood enters nephrons via afferent arterioles, which branch into capillaries called glomeruli. These filter blood plasma, allowing water and solutes, like sodium ions, to pass through capillary walls into Bowman's capsule. The filtrate then flows through various tubules...
Antihypertensive Drugs: Potassium-Sparing Diuretics01:28

Antihypertensive Drugs: Potassium-Sparing Diuretics
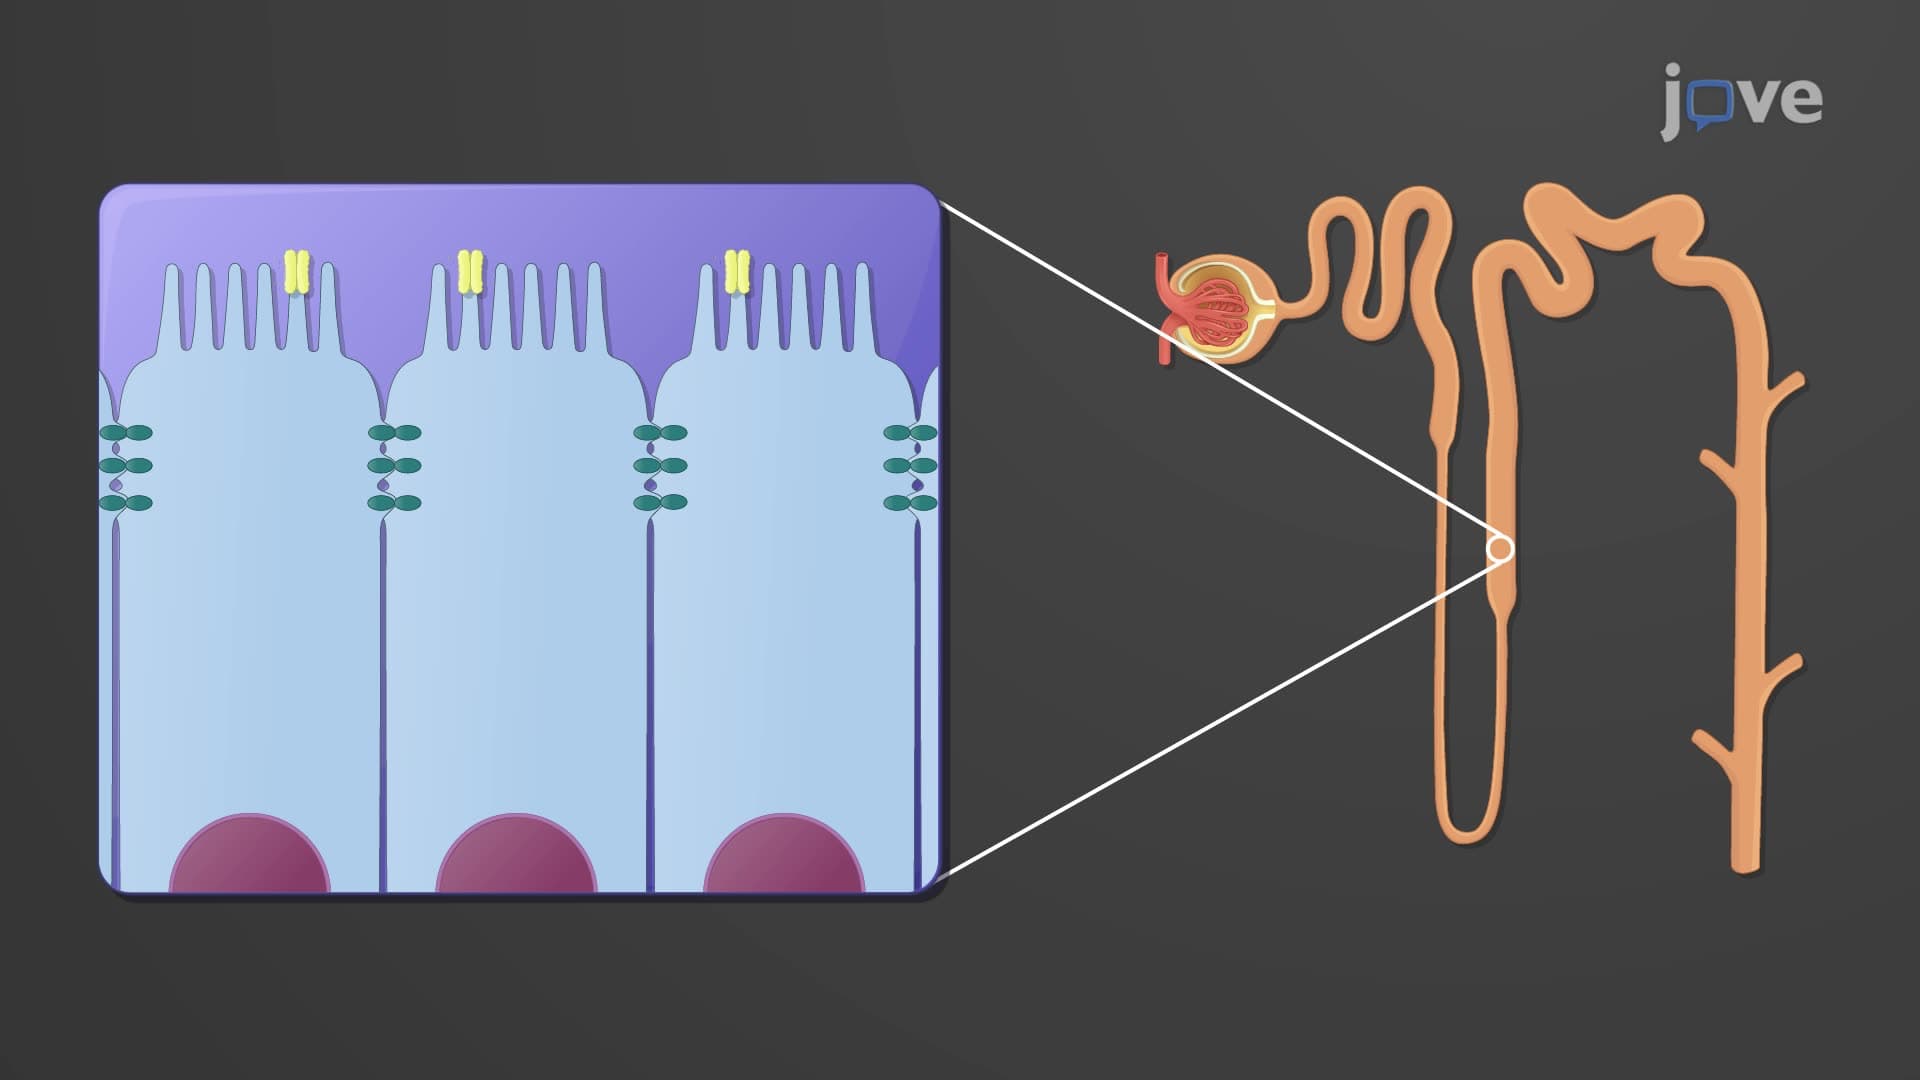
Liddle syndrome is a genetically inherited form of hypertension characterized by the overactivity of epithelial sodium channels in the nephron, the functional unit of the kidney. This heightened activity leads to increased sodium reabsorption and excessive excretion of potassium. To counteract this, potassium-sparing diuretics such as amiloride are used. They function by blocking these sodium channels, thereby reducing the influx of sodium into the epithelial cells and minimizing the loss of...
Reabsorption and Secretion in the Loop of Henle01:17

Reabsorption and Secretion in the Loop of Henle
The thick ascending limb of the nephron loop has Na+–K+–2Cl− symporters in the apical membranes of its cells. These symporters simultaneously reclaim one sodium ion, one potassium ion, and two chloride ions from the tubular fluid. Sodium ions are actively transported into the interstitial fluid at the base and sides of the cell, diffusing into the vasa recta. Chloride ions move through leakage channels in the basolateral membrane into the interstitial fluid and then into the vasa recta.
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa01:22

Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa

The pH of urine, the drug's pKa, and the urine flow rate are vital parameters for drug reabsorption and excretion. Urinary pH varies between 4.6 and 8.0 and is influenced by diet, drug intake, and the patient's pathophysiology. It affects a drug's ionization state and reabsorption. For instance, carbohydrate-rich food produces alkaline urine promoting drug excretion, while proteins and certain medications like ascorbic acid lead to acidic urine enhancing reabsorption.
The pKa of a drug,...
Nephrotic Syndrome II : Assessment and Medical Management01:26

Nephrotic Syndrome II : Assessment and Medical Management

IntroductionNephrotic syndrome is a kidney disorder marked by excessive protein loss in the urine, leading to various systemic complications. This condition often results from damage to the glomeruli—the kidney's filtering units—causing proteinuria, low blood protein levels, and fluid retention. Understanding the assessment, diagnosis, and management of nephrotic syndrome is essential for effective treatment and prevention of further kidney damage.AssessmentPatient History: Document any history...
