Related Experiment Video
Updated: Aug 7, 2026


Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
Puzzling biochemical thyroid profile in patients with multinodular goitre originating from a mild iodine deficient
M V el May1, A Kraiem, T Messaoud
1Service des Isotopes, Institut S Azaiz, Tunis, Tunisie.

Abstract:
Thirty Tunisian patients with a voluminous multinodular goiter with cold nodules and inhabiting a region of mild iodine deficiency, have been studied. The 131 I fixation by the thyroid, three hours after ingestion was significatively higher than in normal population. Fourty six per cent of the patients have stable iodine urine contents less or equal to 0.39 mumol/L. Three serum concentrations were paradoxically abnormal: thyrotropin (TSH), thyroglobulin (TG) and gammaglobulin concentrations. Fourty seven per cent of the serum thyrotropin (TSH) levels were less than the normal values though the serum total triiodotyronine (TT3), tetraiodotyronine (TT4), free triiodotyronine (FT3), free tetraiodotyronine (FT4), antithyroglobulin antibodies, total protein, triglycerides and cholesterol concentrations were normal. Serum thyroglobulin (TG) rates were elevated, ranged from 2 to 10,180 ng/ml and twenty five per cent of our patients showed levels greater than 500 ng/ml. The gammaglobulin levels were greater than normal in sixty eight per cent of our patients though only 10% of our patients manifest antithyroglobulin antibodies.
More Related Videos


Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:20
Synthesis and Regulation of Thyroid Hormones
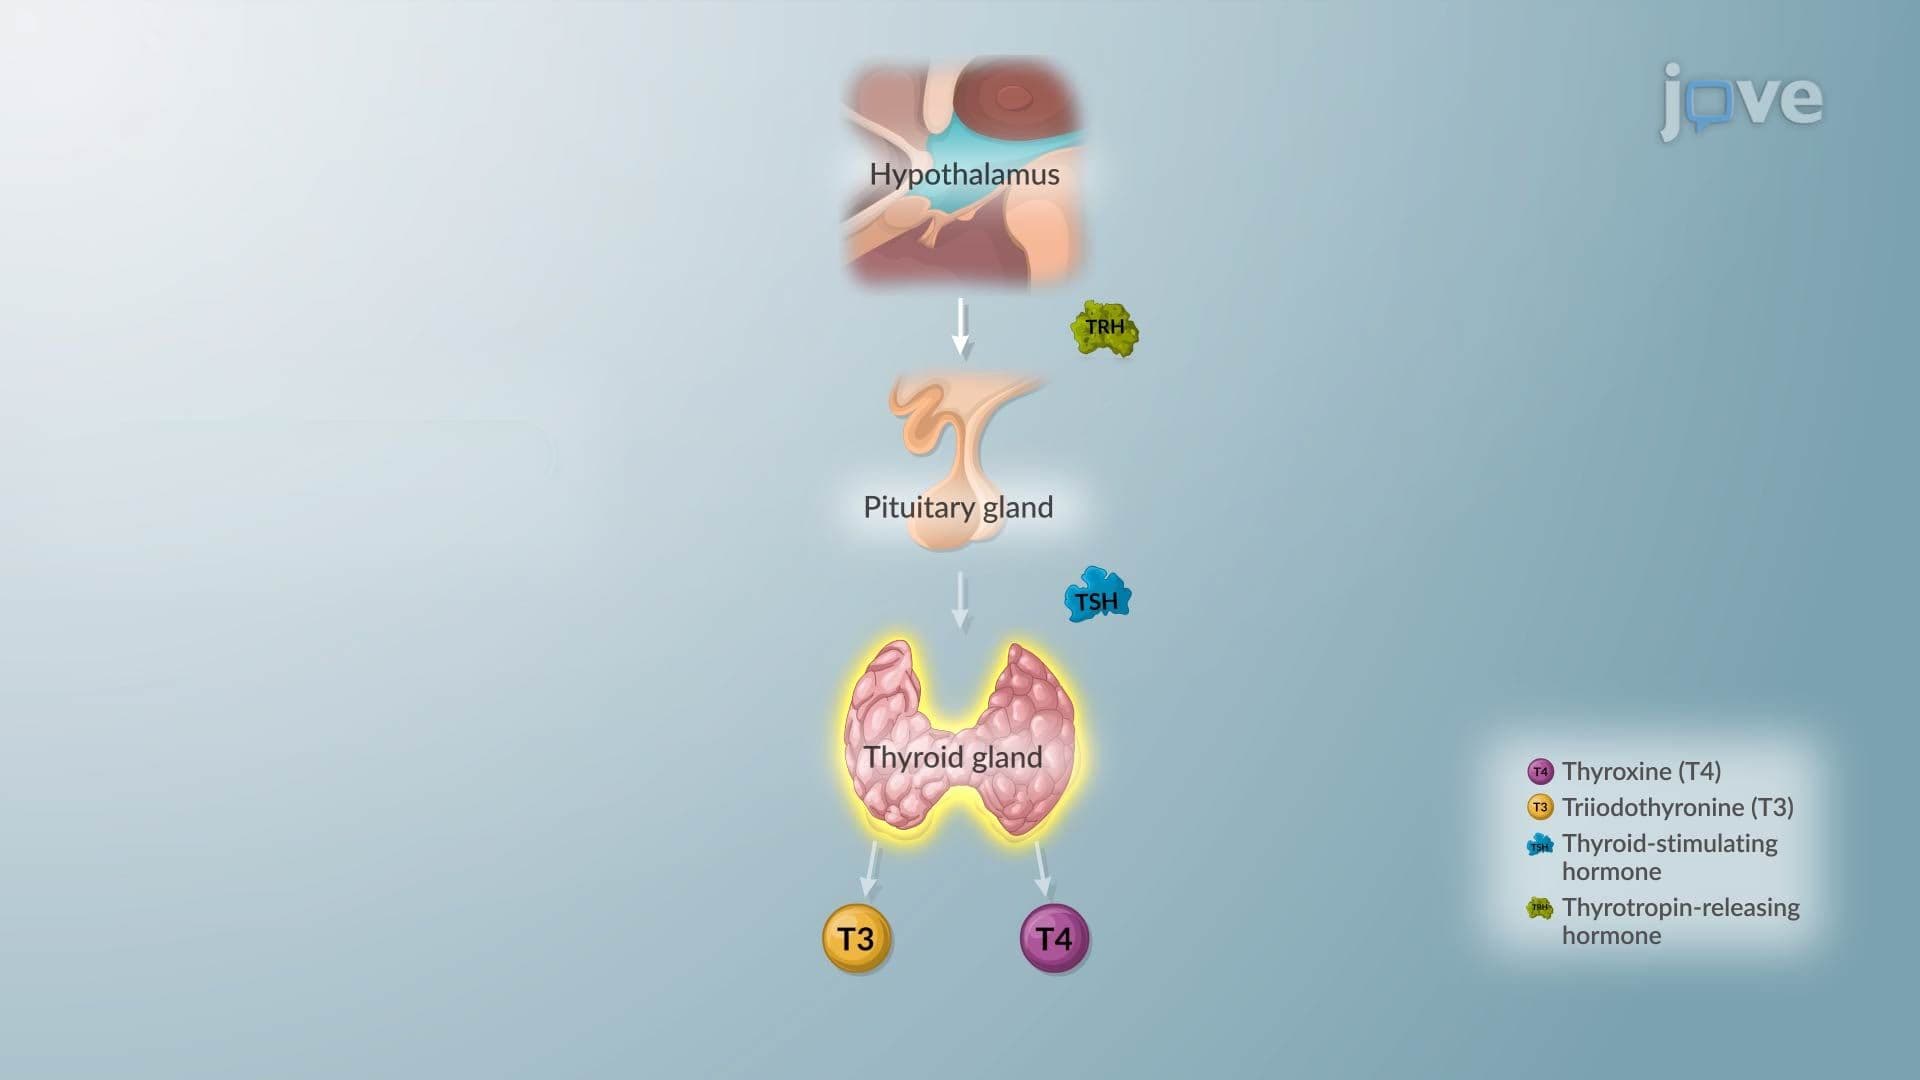
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:27
Goiter
 01:23
Hypothyroidism II: Pathophysiology