Related Experiment Video
Updated: Aug 11, 2026


Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Hormone refractory disease

Abstract:
Hormone refractory disease is observed in less than 20% of newly diagnosed cases of advanced prostatic cancer. In the majority of cases, hormone refractory disease appears after a median time of 18 months of endocrine manipulation and is attributed to the selection and/or cloning of pre-existing or de novo appearing hormone-independent or resistant cell lines. There are no generally accepted rules for second-line management. The varying sets of criteria used by different study groups make comparisons of widely different regimens very difficult. Actually, it seems reasonable to consider length of survival as the only objective response criterion. This implies, however, that there should be an unanimous definition about the moment of primary treatment failure. Indeed, the detection of hormonal escape is a gradual event and the relative length of survival time depends on the chosen moment of therapy administration. To date, monitoring of prostate specific antigen (PSA) has become the best and primary tool to document progression of disease. Earlier diagnosis based on a rise in PSA levels in patients that are still asymptomatic with a good performance status, might provide the opportunity to treat patients that could profit from therapy and give a fair chance to the investigated drug to show efficacity and tolerability. In this paper we will discuss the rationale of the current available second-line therapeutic options in relapsed prostatic cancer.
Insights
Hormone refractory prostate cancer affects less than 20% of advanced cases. Early detection via prostate-specific antigen (PSA) monitoring aids in guiding second-line treatments for better survival outcomes.
Area of Science:
- Oncology
- Urology
Background:
- Hormone-refractory prostate cancer (HRPC) develops in a minority of advanced cases, typically after 18 months of endocrine therapy.
- HRPC is attributed to the emergence of hormone-independent or resistant prostate cancer cell lines.
- Current second-line management lacks standardized criteria, hindering treatment comparisons.
Purpose of the Study:
- To review the rationale behind current second-line therapeutic options for relapsed prostate cancer.
- To highlight the importance of standardized criteria for evaluating treatment efficacy in HRPC.
Main Methods:
- Review of current literature on second-line treatments for advanced prostate cancer.
- Discussion on the role of prostate-specific antigen (PSA) monitoring in disease progression detection.
Main Results:
- Prostate-specific antigen (PSA) monitoring is the primary tool for documenting disease progression.
- Early PSA-based diagnosis in asymptomatic patients may improve treatment opportunities and drug evaluation.
- Length of survival remains the most objective criterion, necessitating a clear definition of treatment failure.
Conclusions:
- Standardized criteria for evaluating second-line therapies in HRPC are crucial.
- Early detection of disease progression using PSA monitoring can optimize patient selection for novel therapies.
- Further research is needed to establish universally accepted treatment guidelines for relapsed prostate cancer.
More Related Videos
 08:59
Looking for Driver Pathways of Acquired Resistance to Targeted Therapy: Drug Resistant Subclone Generation and Sensitivity Restoring by Gene Knock-down
Published on: December 11, 2017
 09:11
Y-90 Radioembolization and PD-1 Inhibitor as Neoadjuvant Treatment in Hepatocellular Carcinoma
Published on: May 24, 2024
Related Concept Videos
 01:08
Intracellular Hormone Receptors
 02:56
Treatment Resistant Cancers
02:56Treatment Resistent Cancers
 01:22
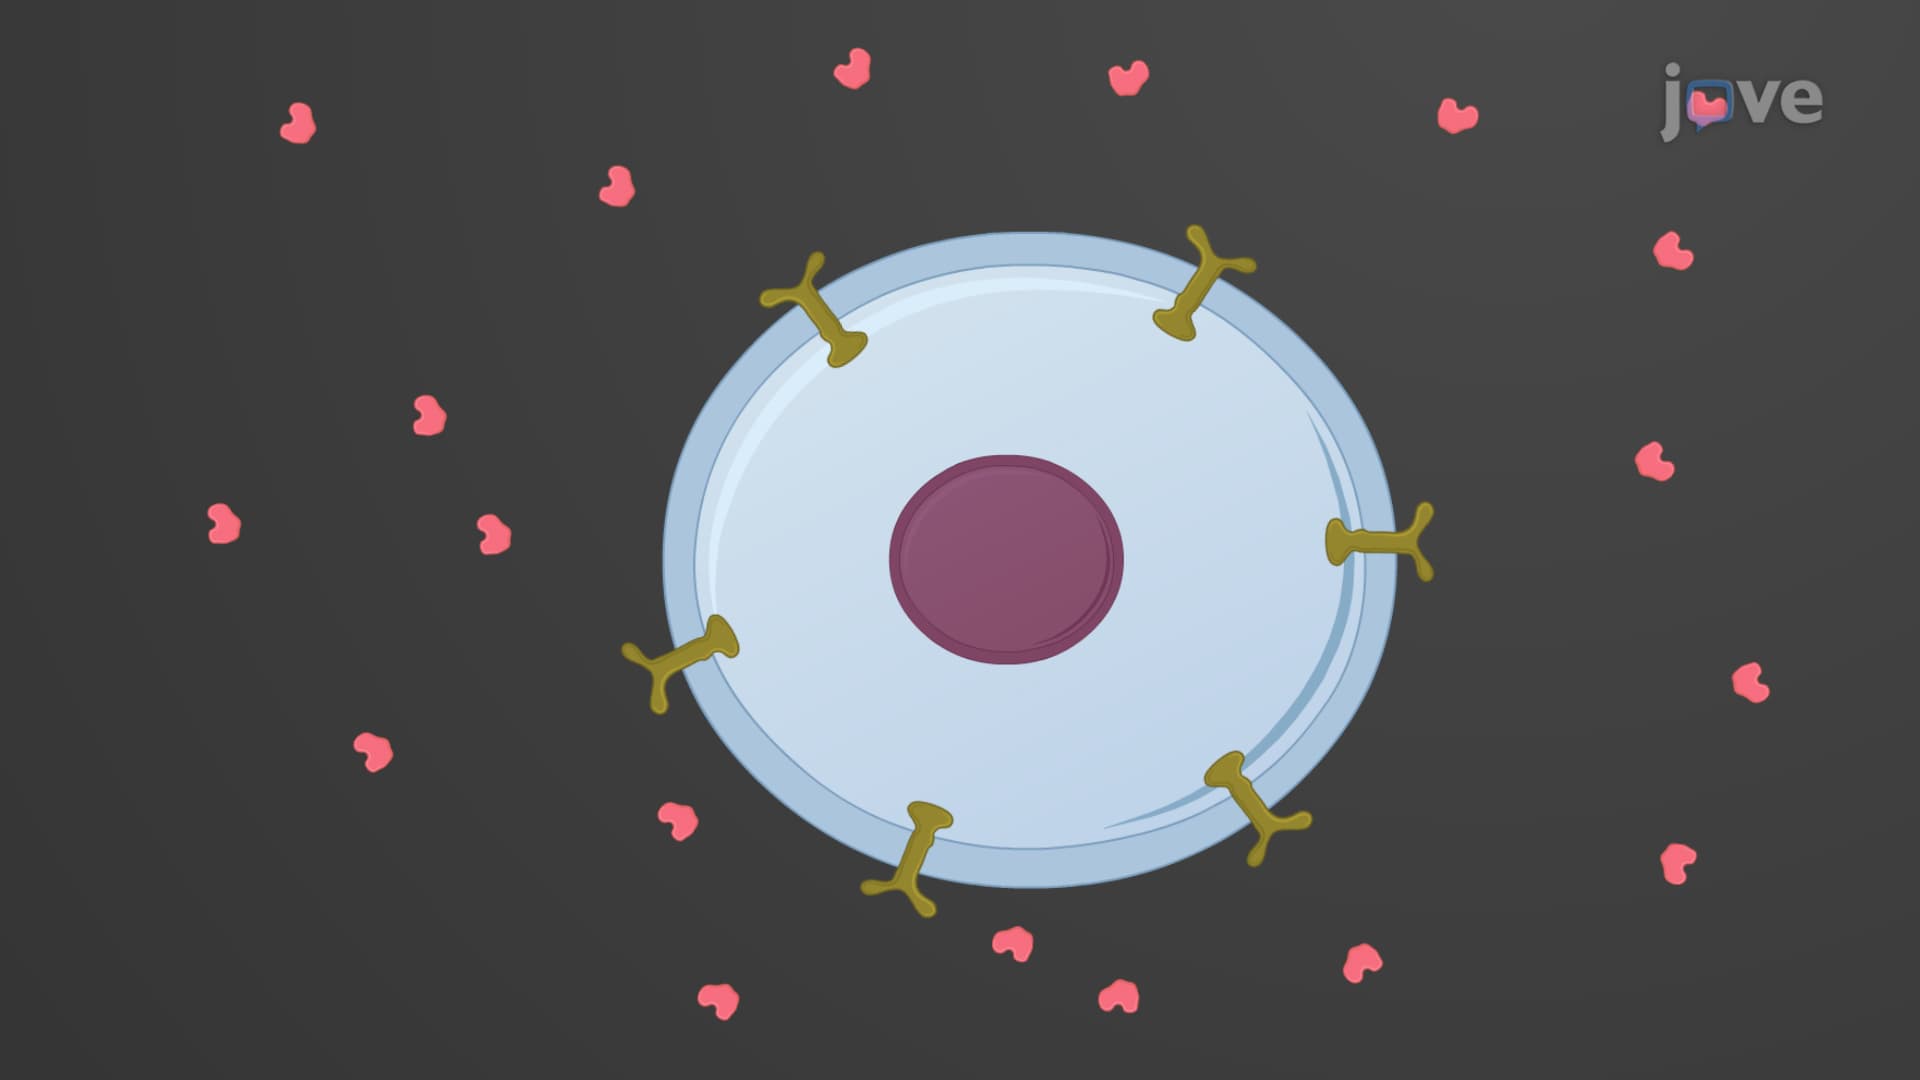
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology