Related Experiment Video
Updated: Oct 3, 2026
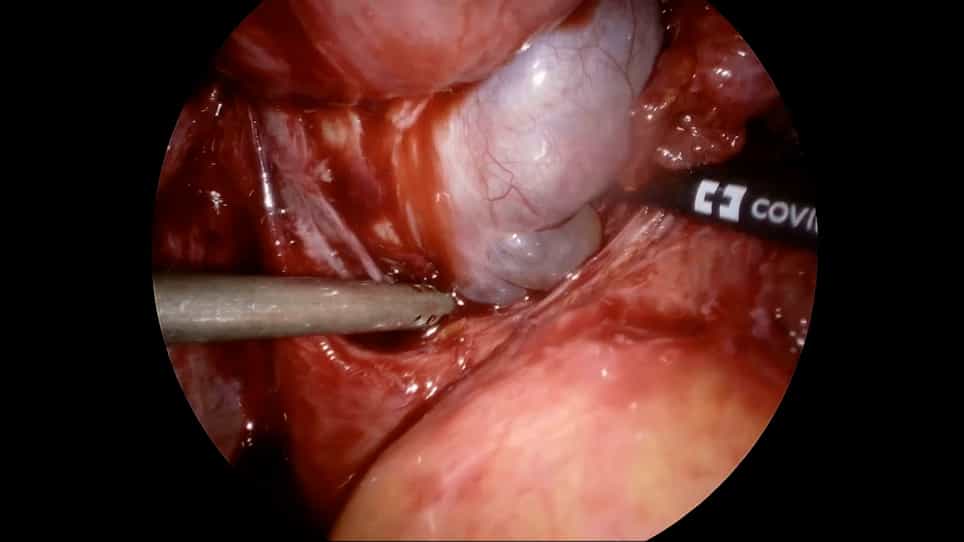
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Endometrioid adenocarcinoma of the ovary and its relationship to endometriosis
D S McMeekin1, R A Burger, A Manetta
1UCI Medical Center, Orange, California 92688, USA.

Abstract:
In order to better understand the clinical presentation and biologic behavior of ovarian carcinomas arising in endometriosis, we performed a historical cohort study of all women with endometrioid adenocarcinoma of the ovary (ECO) diagnosed between 1979 and 1991 at our institutions. A review of pathology reports determined the presence or absence of coexisting endometriosis. Cancers adjacent to endometriosis on the same ovary or arising within endometriosis were labeled endometriosis-associated endometrioid adenocarcinoma (EAEA), while all others were considered typical endometrioid adenocarcinoma (TEA). Associations between tumor type and clinicopathologic variables were analyzed by chi 2 and Fisher's exact tests as indicated. Disease-free interval (DFI) and overall survival were estimated using the Kaplan-Meier method. The independent prognostic significance of clinicopathologic variables was determined by multivariate analysis using the Cox proportional hazards regression model. Of 91 ECO patients identified, 63 (69%) had TEA and 28 (31%) had EAEA. Significant differences between TEA and EAEA existed for age at diagnosis (greater than 55 years; 56 vs 32%, P = 0.039), nulliparity (19 vs 46%, P = 0.007), stage (I and II combined; 37 vs 70%, P = 0.004), and disease status at completion of primary surgery (complete tumor resection; 47 vs 70%, P = 0.04). Synchronous atypical endometrial hyperplasia or uterine carcinoma was found in 7/63 (11%) TEA versus 7/28 (25%) EAEA cases (P = 0.054). Estimated 5-year DFI by life table analysis was significantly longer in the EAEA than in the TEA cohorts (57 vs 25%, P = 0.02); however, the 5-year survival difference was not significant (59 vs 45%, P = 0.18). Multivariate analysis identified only stage as an independent prognostic factor in predicting both DFI and survival. In conclusion, women with EAEA are significantly younger, present with earlier stage disease, and have a longer disease-free survival than those with TEA. These factors may reflect a more favorable biologic behavior of ECO when arising in association with endometriosis.


Related Concept Videos
 02:07
Oogenesis
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:26
Ovaries
On the ovarian surface, a layer of cuboidal...
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:24
Disorders of the Female Reproductive System