The effects of oestrogens and progestogens on the postmenopausal endometrium
Related Experiment Video
Updated: Oct 13, 2026

Two Methods for Establishing Primary Human Endometrial Stromal Cells from Hysterectomy Specimens
Published on: May 23, 2014

Abstract:
Cyclical regimens of unopposed oestrogens are associated with the development of endometrial hyperplasia and the incidence of hyperplasia is dose-related. As no pattern of vaginal bleeding serves as a reliable indicator of underlying endometrial pathology and as hyperplasia can develop subsequent to the finding of a normal endometrium and at any time from 2 to 35 mth after the start of treatment, serial biopsies are required on every patient. Oral oestrone and oestradiol complexes both give rise in the plasma principally to oestrone and therefore the term "Hormone replacement therapy" is inappropriate. The incidence of hyperplasia during sequential oestrogen/progestogen therapy is greatly reduced and therefore progestogens are capable of protecting against the development of this condition. Sequential regimens can also reverse oestrogen-related hyperplasia to normal endometrium.

Related Concept Videos
 02:07
Oogenesis
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:27
Ovarian Cycle
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
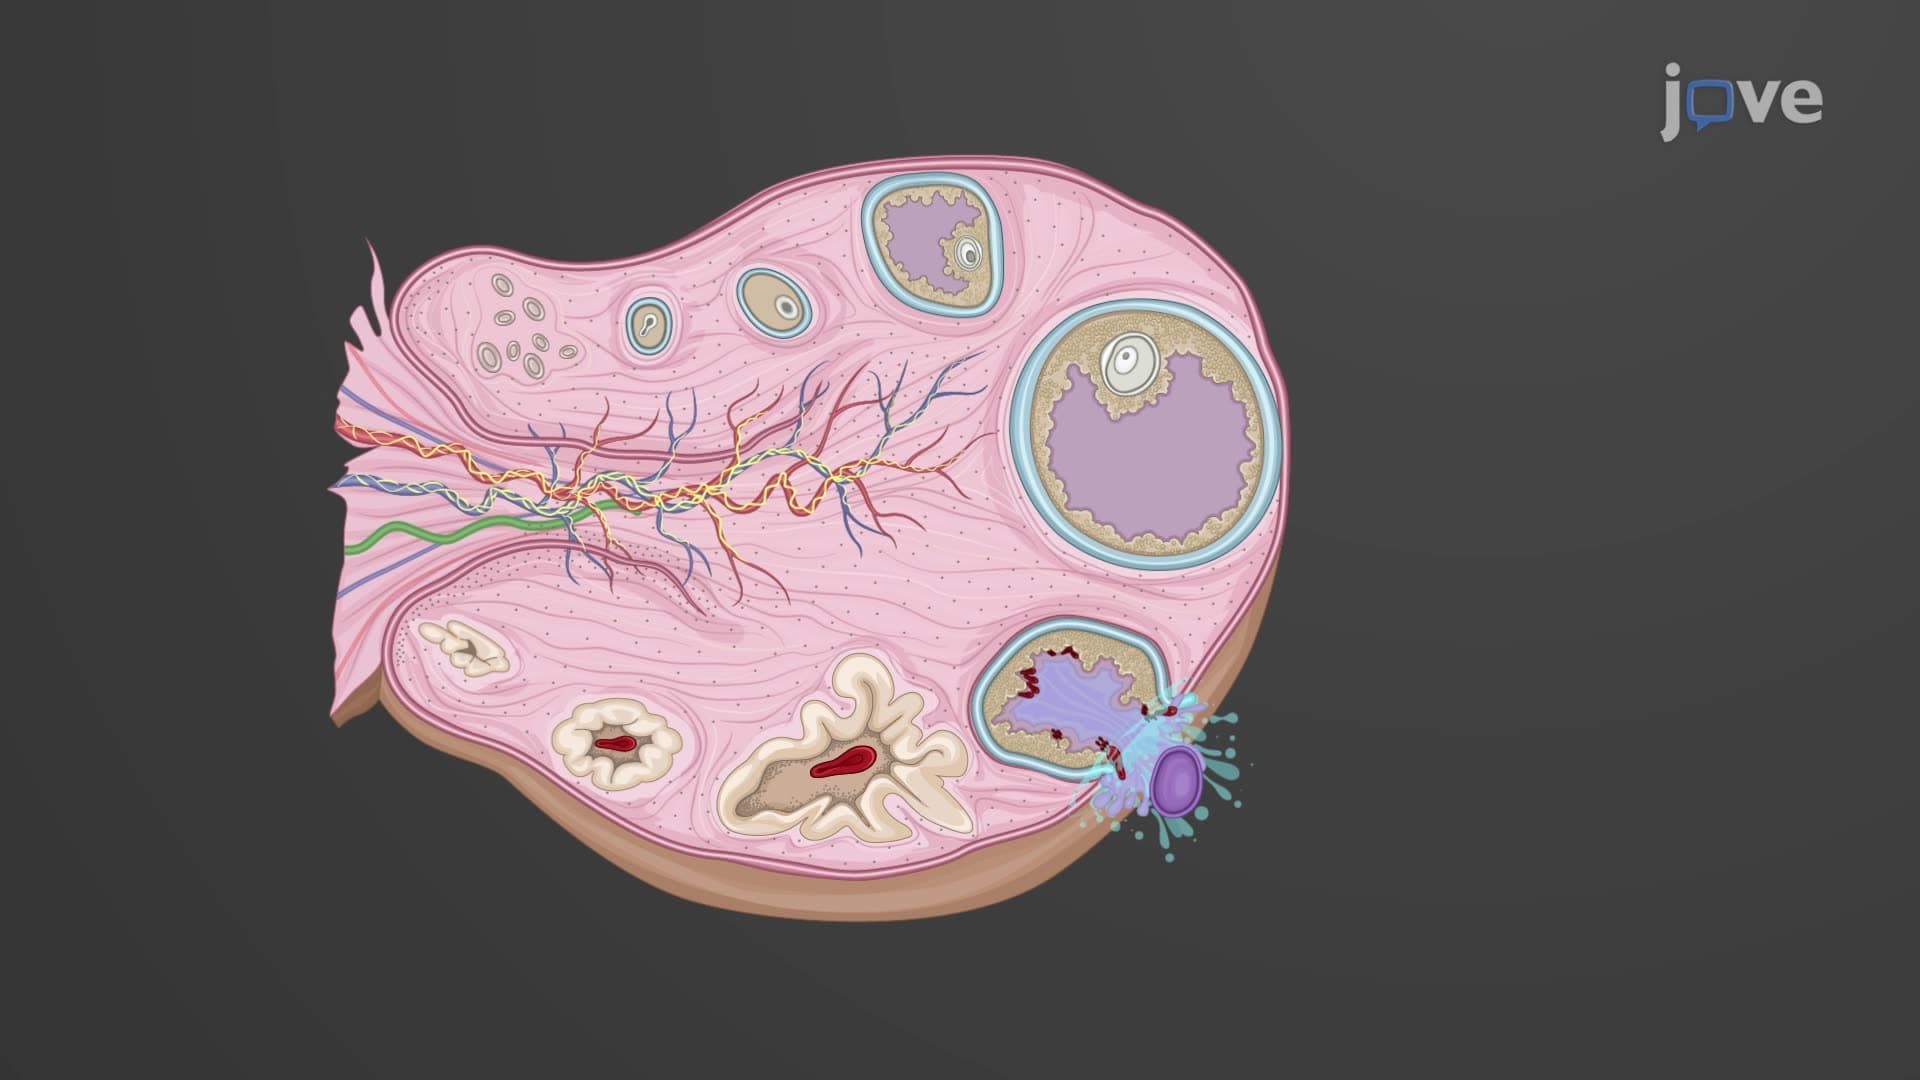 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:28
Menopause