Related Experiment Video
Updated: Oct 12, 2026

Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Influence of plasma lipoprotein (a) levels on coronary vasomotor response to acetylcholine
Y Tsurumi1, H Nagashima, K Ichikawa
1Department of Cardiology, Heart Institute of Japan, Tokyo, Japan.

Insights
Elevated lipoprotein(a) [Lp(a)] impairs coronary artery vasodilation, even without visible atherosclerosis. This suggests Lp(a) causes endothelial dysfunction, contributing to future coronary artery disease risk.
Area of Science:
- Cardiovascular Research
- Endothelial Function Studies
- Lipoprotein Analysis
Background:
- Epidemiologic studies link elevated plasma lipoprotein(a) [Lp(a)] to increased coronary artery disease risk.
- Coronary risk factors impact endothelium-dependent vasomotion.
- The specific influence of Lp(a) on coronary vasomotor function remained undetermined.
Purpose of the Study:
- To investigate the impact of plasma lipoprotein(a) [Lp(a)] levels on coronary endothelial vasomotor function.
- To determine if Lp(a) affects the ability of coronary arteries to dilate or constrict.
Main Methods:
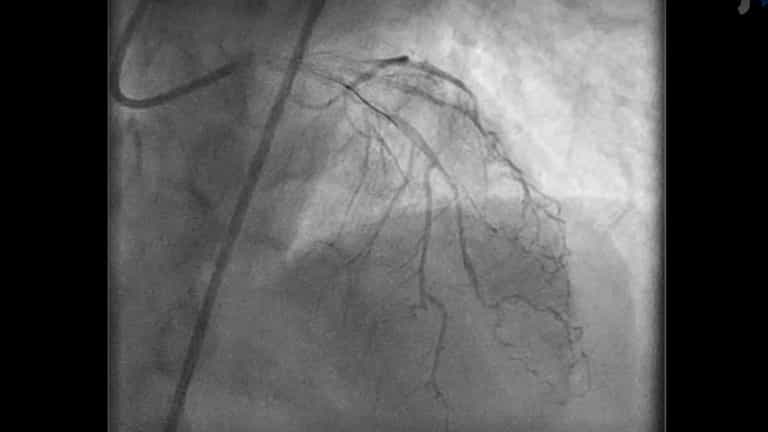
- Quantitative coronary angiography was used to assess left anterior descending coronary artery diameter changes.
- Intracoronary acetylcholine and isosorbide dinitrate were administered to evaluate vasomotion.
- Plasma Lp(a) levels were quantified using enzyme-linked immunosorbent assay in 30 patients with normal coronary arteries.
Main Results:
- A significant inverse correlation was observed between plasma Lp(a) levels and acetylcholine-induced vasomotion across all segments of the left anterior descending coronary artery (p < 0.01).
- Plasma Lp(a) was identified as a significant predictor of vasomotion in response to acetylcholine.
- Vasomotor responses varied, with Lp(a) inversely correlating with the degree of vasodilation/constriction.
Conclusions:
- Elevated plasma Lp(a) levels are associated with impaired endothelium-dependent vasodilation.
- This endothelial dysfunction occurs even in the absence of angiographically detectable atherosclerotic lesions.
- These findings suggest Lp(a) contributes to endothelial dysfunction and may play a role in the development of atherosclerosis.
Objectives:
This study was undertaken to examine the influence of plasma lipoprotein(a) [Lp(a)] levels on coronary endothelial vasomotor function.
Background:
Epidemiologic studies have demonstrated a direct relation between elevated plasma levels of Lp(a) and increased risk of coronary artery disease. Well recognized coronary risk factors are known to affect endothelium-dependent vasomotion; however, the influence of Lp(a) on coronary vasomotor function has not been determined.
Methods:
We used quantitative coronary angiography to measure left anterior descending coronary artery diameter changes produced by intracoronary acetylcholine and isosorbide dinitrate in 30 patients with angiographically normal coronary arteries. Plasma Lp(a) levels were determined with enzyme-linked immunosorbent assay.
Results:
Vasomotor response to acetylcholine ranged from +13% to -47% in the proximal, from +23% to -53% in the middle and from +13% to -56% in the distal segment of the left anterior descending coronary artery. According to univariate linear regression analysis, Lp(a) had a significant inverse correlation with vasomotor response to acetylcholine: r = 0.47, p < 0.01 in the proximal; r = -0.61, p < 0.001 in the middle; and r = -0.52, p < 0.01 in the distal segment of the left anterior descending coronary artery. By multiple stepwise regression analysis, plasma Lp(a) was the significant predictor of vasomotion in response to acetylcholine in all tested segments (p < 0.01).
Conclusions:
Elevated Lp(a) levels were associated with impairment of endothelium-dependent vasodilation even when atherosclerotic lesions were not recognizable by angiography. This finding suggests that elevated plasma levels of Lp(a) cause endothelial dysfunction and may contribute in part to later development of atherosclerosis, as shown in epidemiologic studies.
Related Concept Videos
 01:26
Coronary Artery Disease II: Pathophysiology
 01:26
Coronary Artery Disease IV: Preventive Measures
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Atherosclerosis III: Management