Related Experiment Video
Updated: Jun 23, 2026


Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Twenty to 40 year follow up of infantile hiatal hernia
B T Johnston1, I J Carré, P S Thomas
1Department of Medicine, Queen's University of Belfast, Northern Ireland.

Insights
Hiatal hernias diagnosed in childhood often persist into adulthood, but most patients experience minimal symptoms. Early treatment may reduce adult heartburn and antacid use, though endoscopic screening is advised due to potential Barrett
Area of Science:
- Gastroenterology
- Pediatric Surgery
- Clinical Medicine
Background:
- Hiatal hernias diagnosed in infancy or early childhood can persist into adulthood.
- Long-term clinical outcomes and radiological findings of these cases require further investigation.
- Understanding the natural history of pediatric hiatal hernias is crucial for adult patient management.
Purpose of the Study:
- To evaluate the clinical and radiological characteristics of gastro-oesophageal reflux in adults with a history of childhood hiatal hernia.
- To assess the long-term impact of childhood hiatal hernia on adult gastrointestinal symptoms and treatment needs.
- To identify potential risk factors for persistent symptoms and complications like Barrett's oesophagus.
Main Methods:
- A cohort of 118 adult patients (minimum age 20) with a history of childhood hiatal hernia was interviewed.
- Barium meal examinations were conducted in 96 patients to assess radiological findings.
- Patient data included surgical history, symptom frequency (heartburn), and antacid consumption.
Main Results:
- Hiatal hernia persisted in 53% of non-surgically treated patients; 46% reported monthly heartburn, with few severe cases.
- Heartburn was more frequent in patients with radiological evidence of reflux on barium meal.
- Adults with a history of effective childhood treatment consumed fewer antacids (20% vs. 46%).
- Two patients developed Barrett's oesophagus, suggesting a need for endoscopic surveillance.
Conclusions:
- Persistence of hiatal hernia in adulthood is common, but significant symptoms are infrequent in non-surgically treated individuals.
- Effective childhood treatment correlates with reduced adult antacid use for heartburn.
- The occurrence of Barrett's oesophagus highlights the importance of considering endoscopic screening in this patient cohort.
Abstract:
The aim of this study was to assess clinical and radiological findings of gastro-oesophageal reflux in adults who were diagnosed as having a hiatal hernia in infancy or early childhood. One hundred and eighteen patients with a minimum age of 20 who were diagnosed as having a hiatal hernia in childhood were interviewed; barium meal examination was performed in 96 of these cases. Ninety four patients had not required surgery for their hernia. The hiatal hernia persisted in 53% of these patients and 46% experienced heartburn at least monthly but in only three was this severe. Heartburn was significantly more common in patients in whom reflux was seen on barium meal. The consumption of antacids was significantly lower (20% v 46%) in patients who responded well to treatment as children. Eighteen of 24 patients who underwent surgery as children experienced heart-burn monthly but in only one patient was this severe. Two patients underwent endoscopy at their request because of symptoms during this follow up. Both had Barrett's oesophagus. In conclusion, despite the persistence of the hiatal hernia in half of the non-surgically treated patients, few complained of significant symptoms. Effective treatment in childhood was associated with a significant reduction in antacid consumption for heartburn as adults. The finding of Barrett's oesophagus in two patients high-lights a possible role for endoscopic screening in this patient group.


Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:25
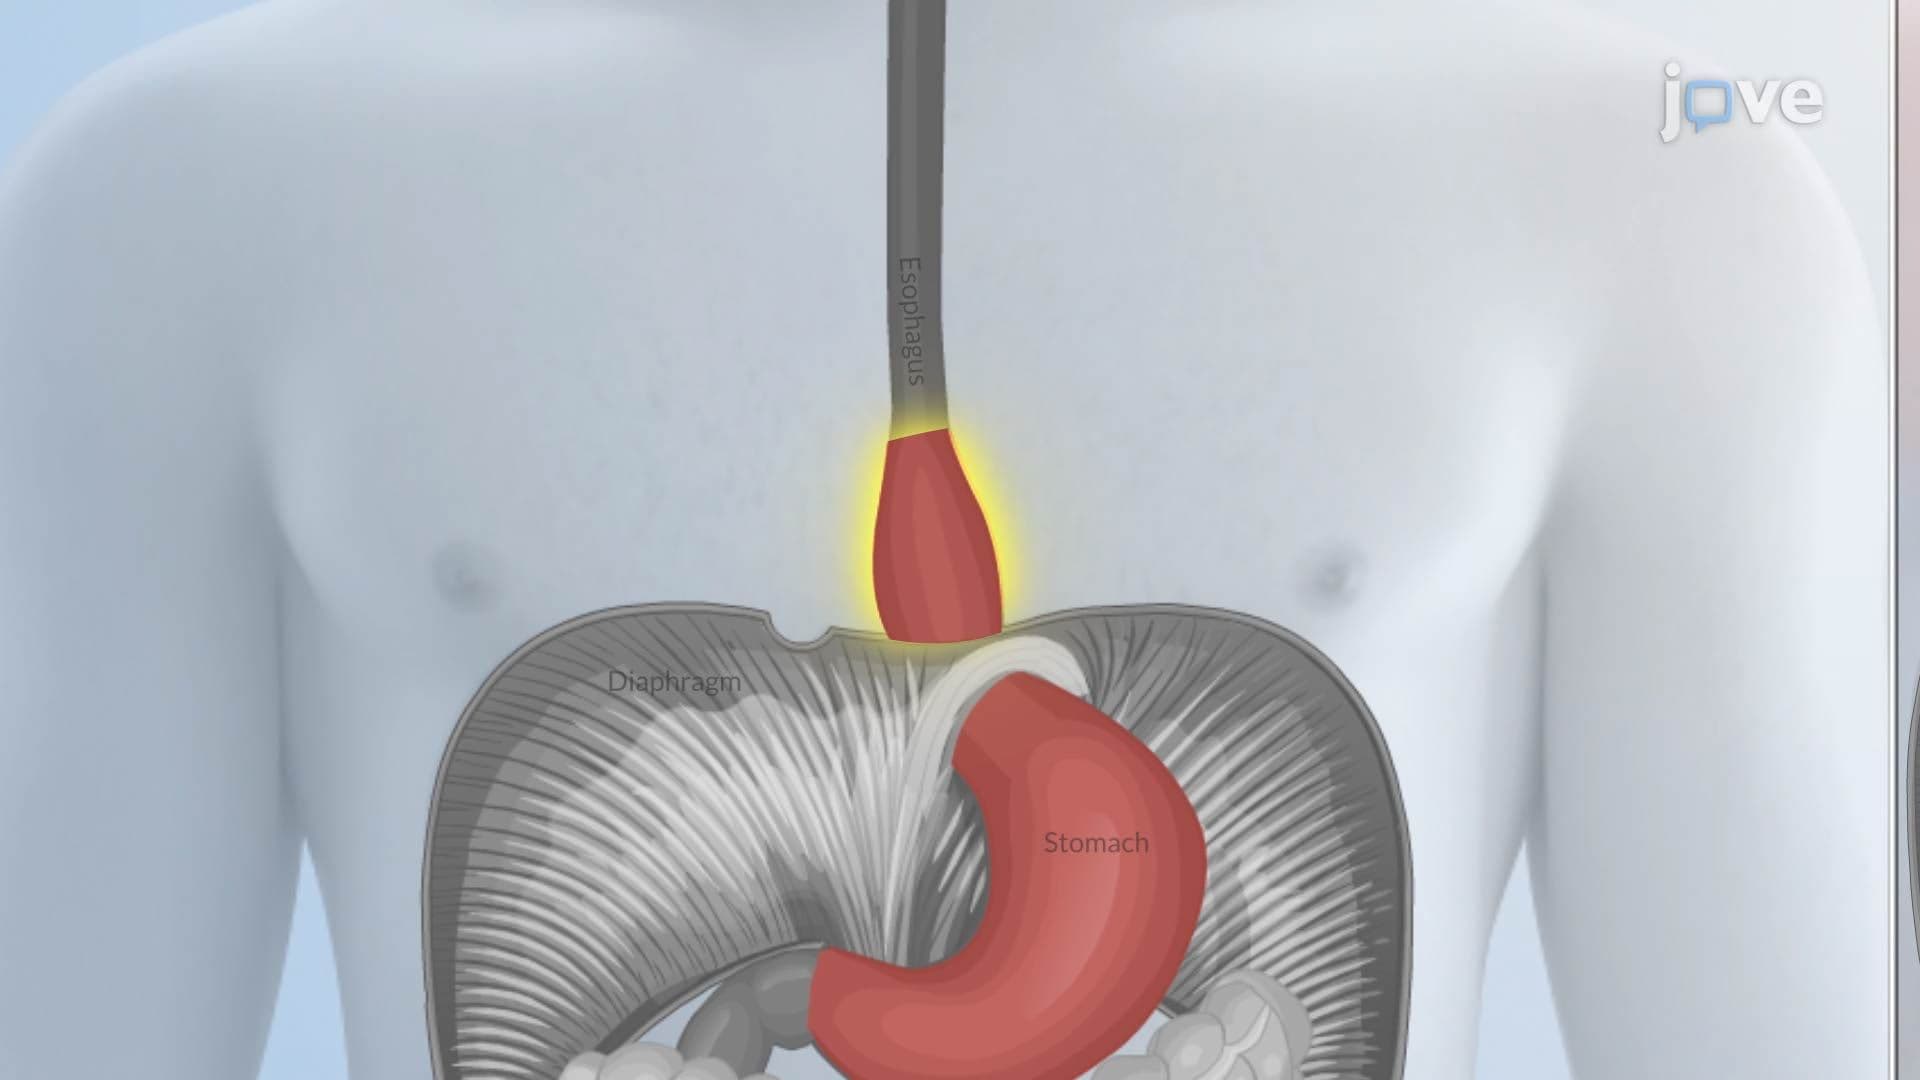
Hiatal Hernia
 01:11
Pyloric Obstruction