Related Experiment Video
Updated: Aug 10, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Intraperitoneal erythropoietin treatment of children with chronic renal failure
1Department of Paediatrics, McMaster University Medical Centre, Hamilton, Ontario, Canada.

Insights
Intraperitoneal erythropoietin effectively improved hemoglobin in children on peritoneal dialysis over six months. This method is cost-effective and avoids the pain associated with subcutaneous injections.
Area of Science:
- Pediatric Nephrology
- Renal Replacement Therapy
- Hematology
Background:
- Chronic kidney disease in children often leads to anemia.
- Erythropoietin is a standard treatment for anemia in dialysis patients.
- Subcutaneous administration of erythropoietin can cause local pain and discomfort.
Purpose of the Study:
- To evaluate the efficacy and safety of intraperitoneal erythropoietin administration in children undergoing chronic peritoneal dialysis.
- To assess the cost-effectiveness of the intraperitoneal route compared to subcutaneous administration.
Main Methods:
- Three children on chronic peritoneal dialysis received intraperitoneal erythropoietin.
- Doses ranged from 100 to 150 units/kg, administered undiluted into a dry peritoneal cavity twice weekly.
- Erythropoietin remained in the cavity for 10-12 hours before resuming dialysis.
Main Results:
- Satisfactory hemoglobin levels were achieved and maintained over a 6-month study period.
- No complications related to intraperitoneal erythropoietin administration were observed.
- The intraperitoneal route demonstrated cost-effectiveness.
Conclusions:
- Intraperitoneal erythropoietin is a safe and effective alternative for managing anemia in pediatric patients on peritoneal dialysis.
- This administration route offers a cost-effective solution and improves patient comfort by avoiding subcutaneous injection pain.
Abstract:
Intraperitoneal erythropoietin was given to three children on chronic peritoneal dialysis. Doses between 100 and 150 units/kg were given undiluted into a dry cavity twice weekly and left for 10-12 h before resuming dialysis. Satisfactory haemoglobin levels were seen over a 6-month period and there were no complications. Intraperitoneal administration of erythropoietin is cost-effective and avoids the local pain of subcutaneous injections.


Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
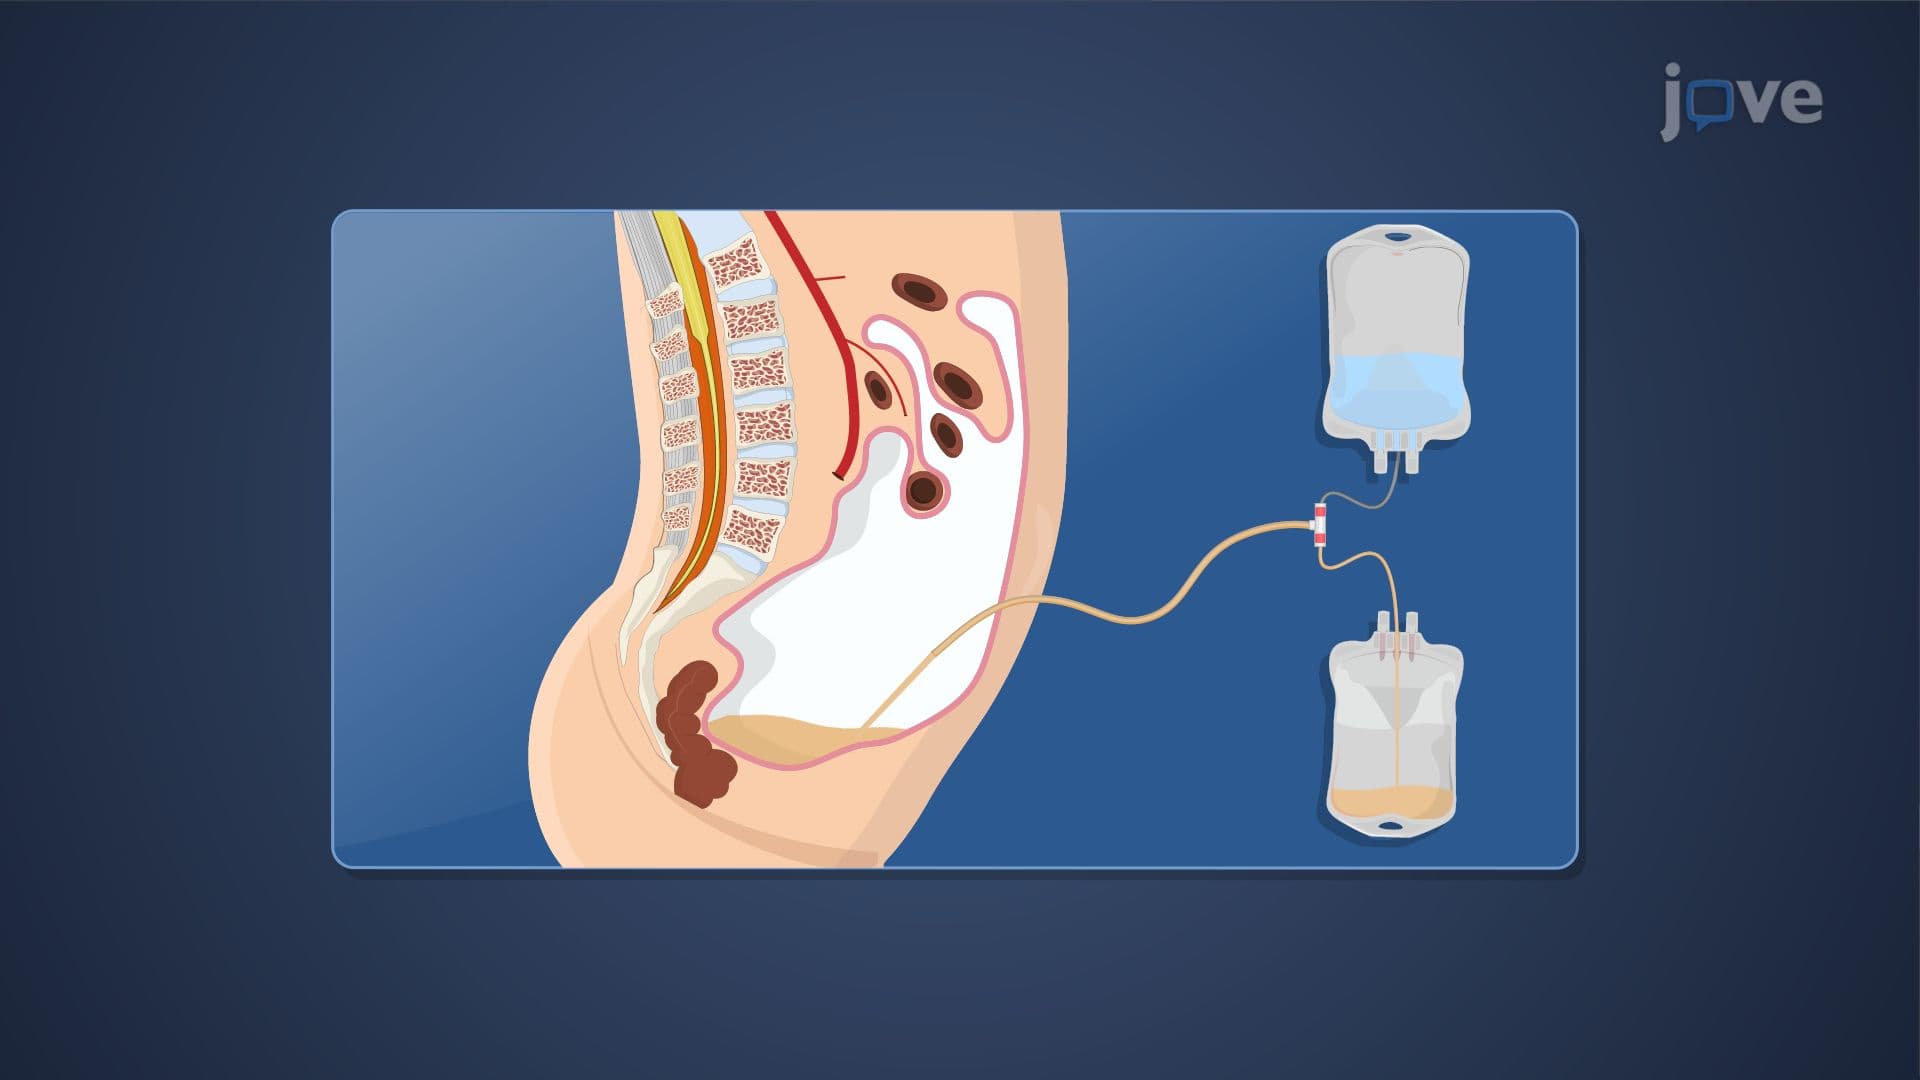 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:20
Acute Kidney Injury V: Interprofessional Care