Related Experiment Video
Updated: Sep 21, 2026


In vitro Measurements of Tracheal Constriction Using Mice
Published on: June 25, 2012
[Physiological basis for the use of muscarine antagonists in bronchopulmonary dysplasia]
J T Fisher1, A B Froese, K L Brundage
1Département de physiologie, d'anesthésie et de pédiatrie de l'université Queen, Kingston, Ontario, Canada.

Abstract:
The rationale for the use of muscarinic antagonists in bronchopulmonary dysplasia (BPD) is based on the physiology and pharmacology of airway smooth muscle, the pathology of BPD, and the response of infants with BPD to bronchodilators, in vivo and in vitro studies of airway smooth muscle of newborn animals and humans indicate that vagal efferent airway innervation and/or muscarinic receptors are functional at birth, as well as early in gestation. Current concepts regarding muscarinic receptor subtypes suggest that M3 receptors mediate airway smooth muscle contraction, M2 receptors are autoinhibitory and limit vagally-mediated bronchoconstriction, and M1 receptors may play a facilitatory role in ganglionic transmission. Muscarinic receptor subtypes appear to be functionally expressed at birth but may undergo developmental regulation. Infants with BPD have an elevated pulmonary resistance that is accompanied by hypertrophy of airway smooth muscle, b2-agonists cause bronchodilation in BPD as does atropine in infants recovering from severe BPD. The synthetic congener of atropine, ipratropium bromide (IPB) causes bronchodilation in ventilator-dependent infants with BPD in a dose-dependent fashion. Nebulized IPB causes a decrease in respiratory resistance that reaches a maximum of 20% at 175 mg. The bronchodilation seen with muscarinic antagonists suggests that part of the elevated resistance associated with BPD is due to increased muscarinic tone, presumably vagal in origin. When IPB is combined with salbutamol (0.04 mg) the response is increased in magnitude and duration; reaching a slightly larger decreases in resistance (26%) that is now accompanied by an increase in compliance (20%).(ABSTRACT TRUNCATED AT 250 WORDS)
Related Concept Videos
 01:22
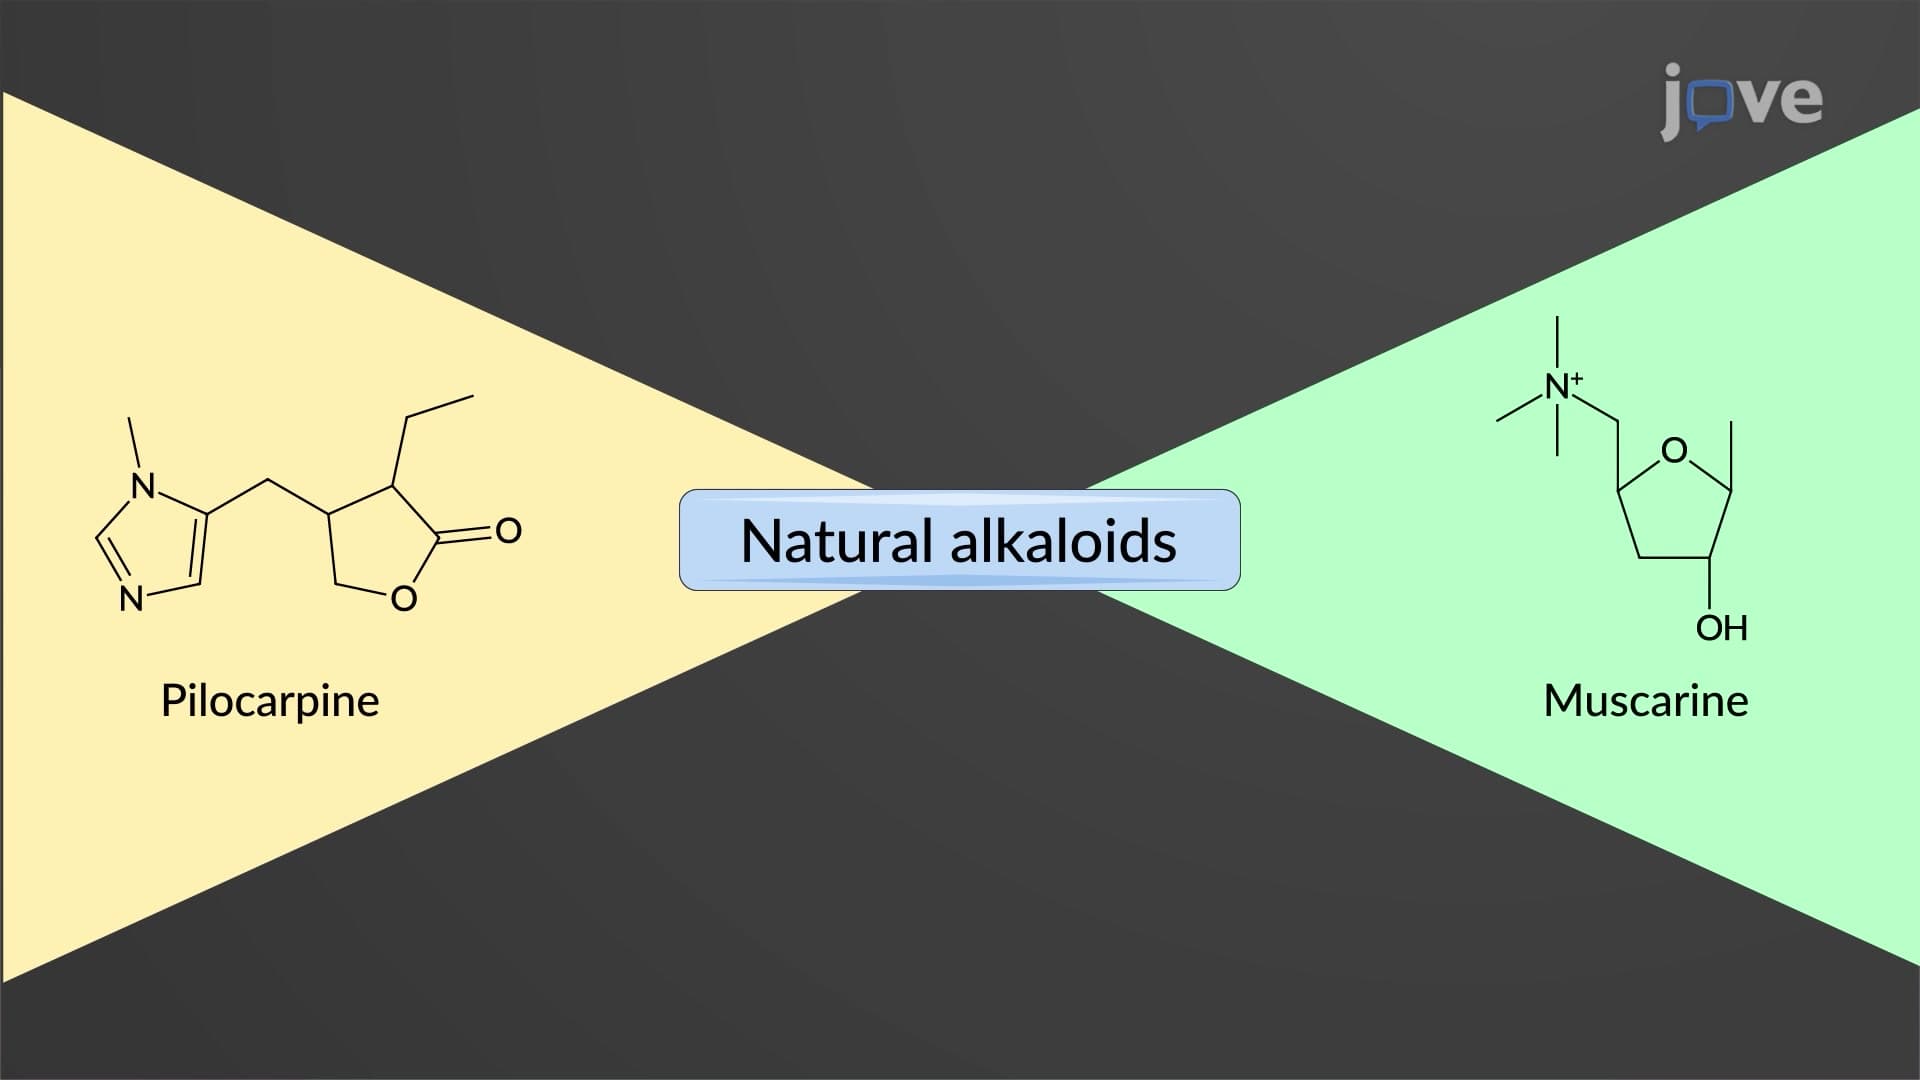
Direct-Acting Cholinergic Agonists: Chemistry and Structure-Activity Relationship
The direct-acting...
 00:59
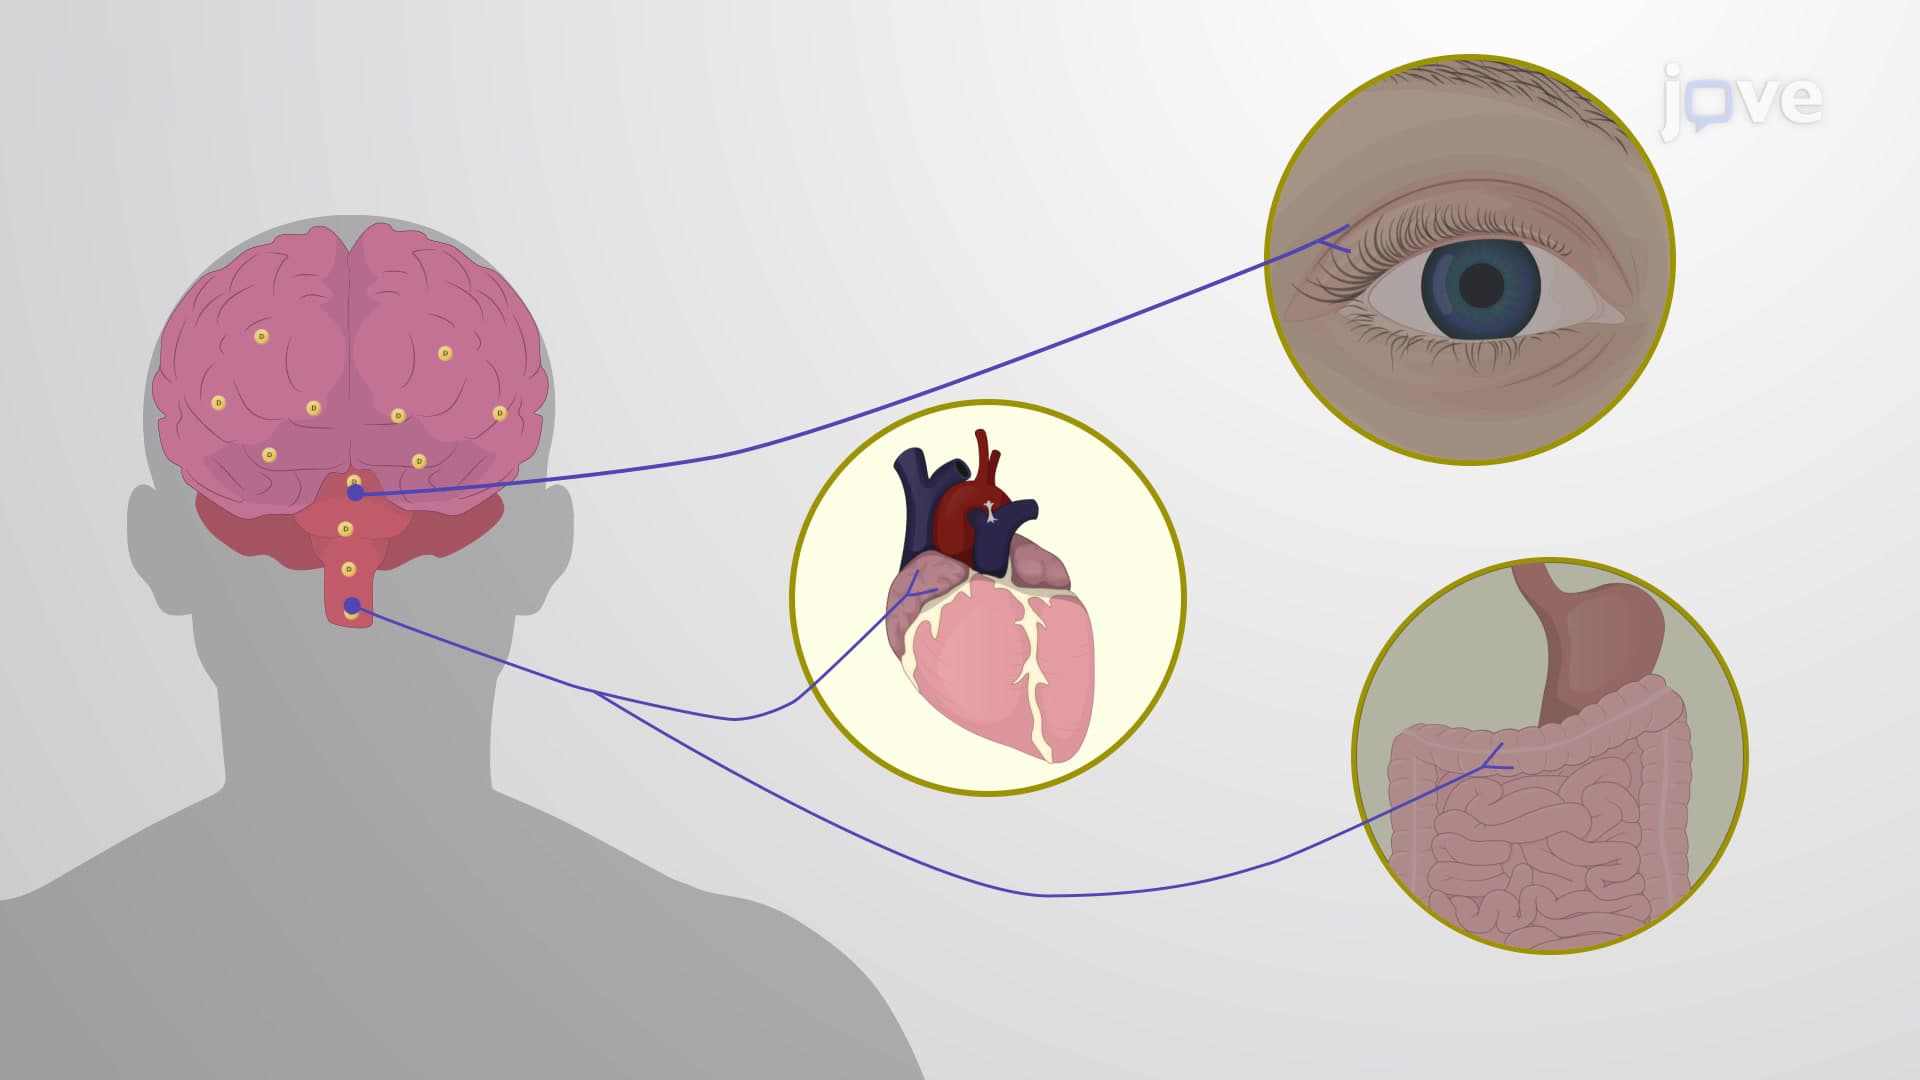
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:11
Direct-Acting Cholinergic Agonists: Therapeutic Uses
 01:28
Cholinergic Antagonists: Pharmacological Actions
Gastrointestinal Effects: Antimuscarinics reduce gut contractions, increase gastric emptying, and slow intestinal transit. They partly inhibit gastric acid secretion...
 01:26
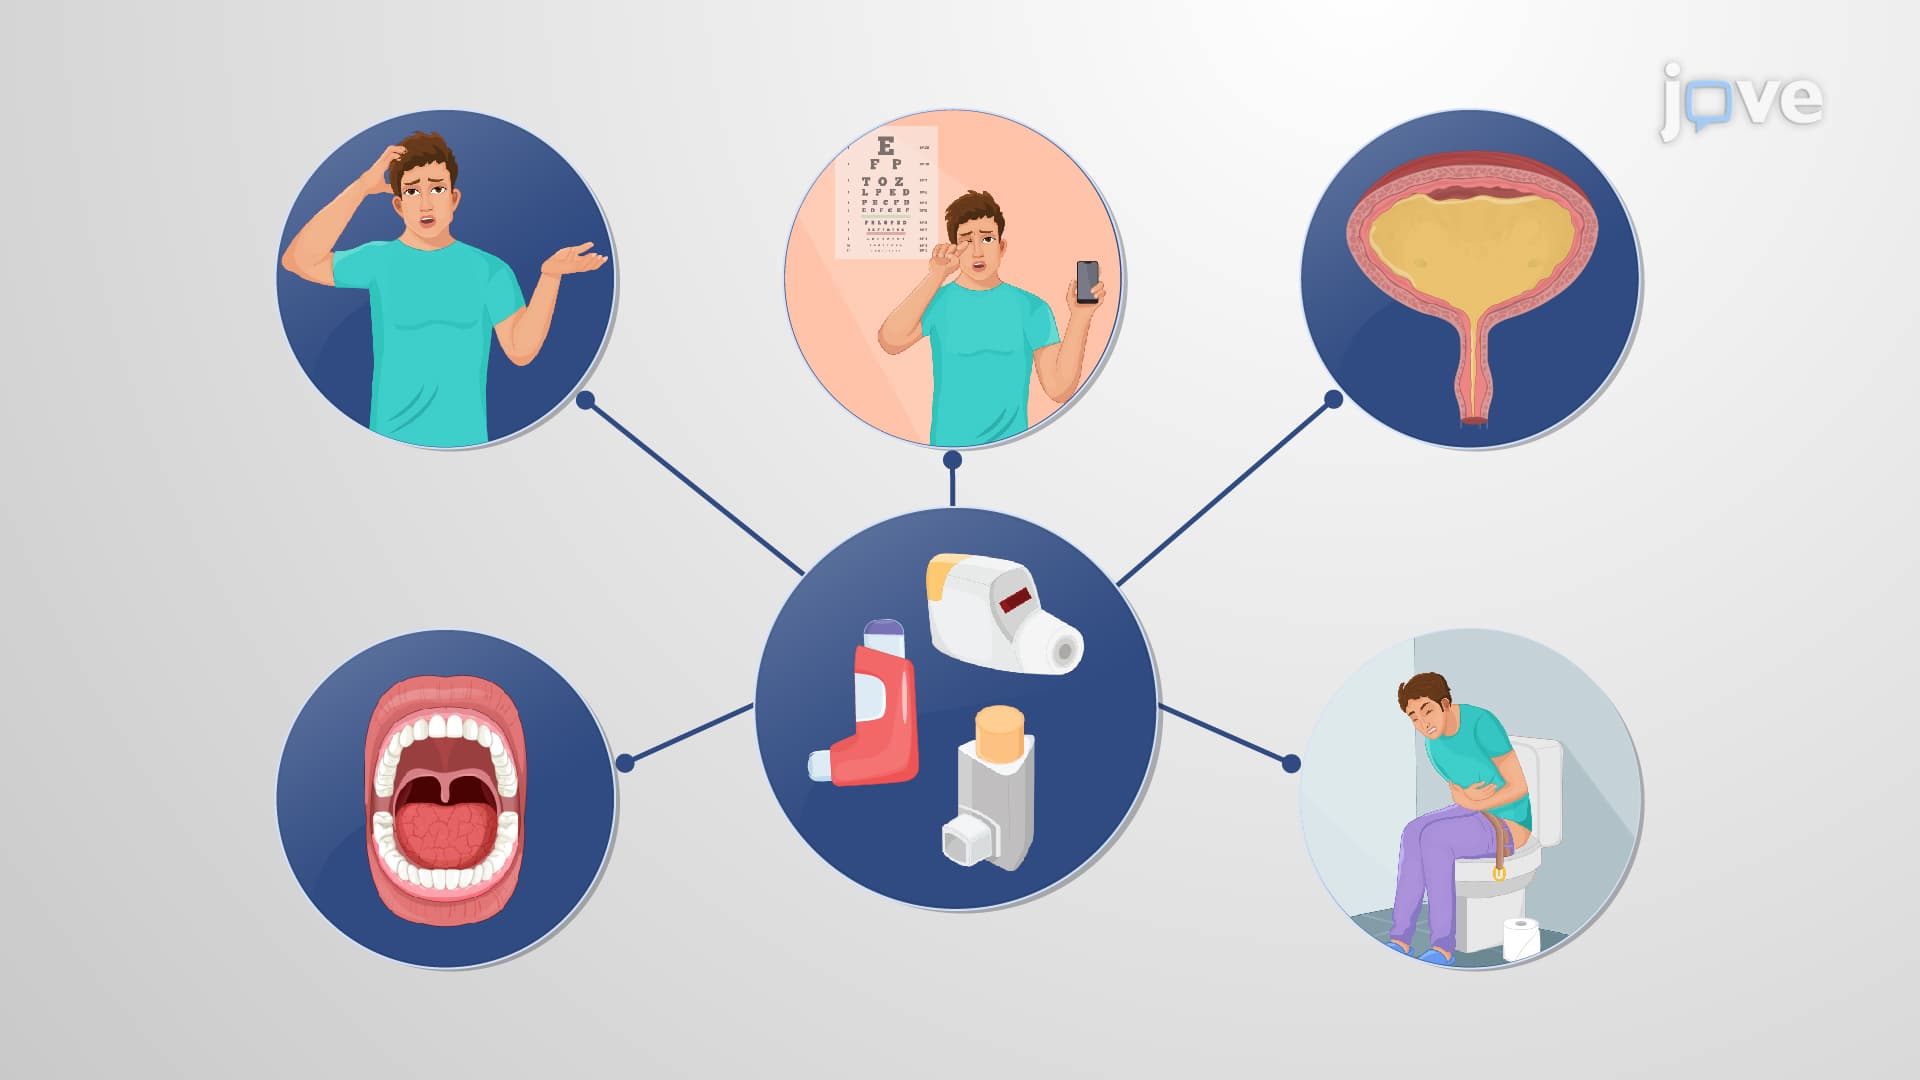
Cholinergic Antagonists: Therapeutic Uses
Respiratory Tract: Ipratropium, aclidinium, and tiotropium treat asthma, chronic bronchitis, and chronic obstructive pulmonary disease (COPD). They protect against bronchoconstriction caused by irritants like cigarette smoke, sulfur dioxide, and ozone. They also help reduce nasopharyngeal secretions in common...
 01:20
Antiasthma Drugs: Muscarinic Receptor Antagonists
Antimuscarinic agents compete with ACh for the same binding site on the muscarinic receptors. By binding to these receptors, they inhibit the downstream effects of ACh and block the parasympathetic...