Related Experiment Video
Updated: Aug 7, 2026
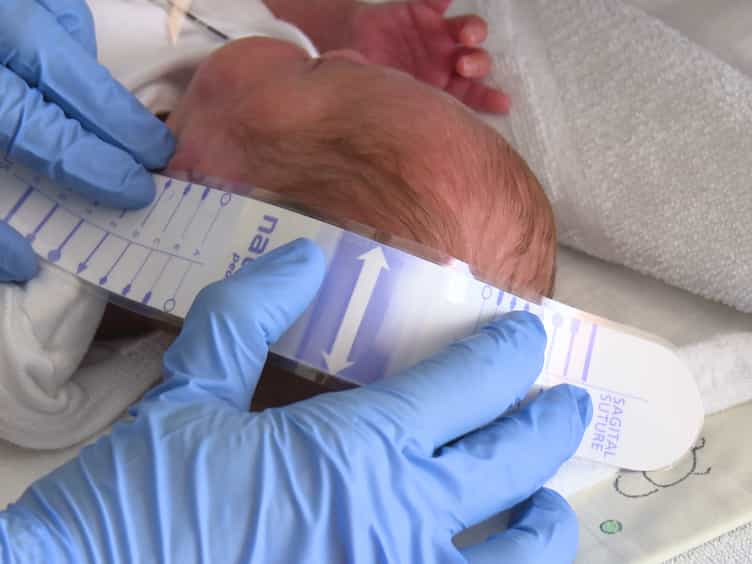

Application of an Amplitude-integrated EEG Monitor (Cerebral Function Monitor) to Neonates
Published on: September 6, 2017
Phases of fluid and electrolyte homeostasis in the extremely low birth weight infant
J M Lorenz1, L I Kleinman, G Ahmed
1Department of Pediatrics and Human Development, Michigan State University, East Lansing, USA.

Insights
Extremely low birth weight infants show three distinct fluid and electrolyte homeostasis phases, prediuretic, diuretic, and postdiuretic, regardless of thermal environment. These phases are linked to changes in renal function, including glomerular filtration rate and sodium excretion.
Area of Science:
- Neonatal Physiology
- Renal Function in Infants
- Fluid and Electrolyte Balance
Background:
- Preterm infants exhibit three phases of fluid and electrolyte homeostasis: prediuretic, diuretic, and postdiuretic.
- Understanding these phases is crucial for managing fluid and electrolyte balance in vulnerable newborns.
Purpose of the Study:
- To investigate if extremely immature infants and those in different thermal environments also display these three homeostatic phases.
- To correlate these identified phases with specific changes in renal function.
Main Methods:
- 32 infants with birth weights ≤1000 g underwent consecutive timed urine collections during the first 5 days of life.
- Infants were initially in radiant warmers, then transferred to nonhumidified incubators; diuresis was defined by urine flow rate and weight loss.
- Physiologic parameters including water/sodium balance, insensible water loss, blood pressure, and renal function were assessed across the three phases.
Main Results:
- 28 out of 32 infants (87%) exhibited the three homeostatic phases, with diuresis typically occurring between 25 and 96 hours of life.
- During the diuretic phase, urine flow, sodium excretion, glomerular filtration rate (GFR), and fractional excretion of sodium (FENa) significantly increased.
- While GFR and FENa returned to prediuretic levels in the postdiuretic phase, GFR remained unchanged, and urine osmolality was consistently dilute.
Conclusions:
- Extremely low birth weight infants demonstrate three fluid and electrolyte homeostasis phases, irrespective of the thermal environment.
- The observed diuresis and natriuresis are attributed to sharp increases in GFR and FENa.
- This phenomenon may be linked to the expansion of the neonatal extracellular space following fetal lung fluid reabsorption.
Objective:
We had shown previously that preterm infants undergo three phases of fluid and electrolyte homeostasis; prediuretic, diuretic, and postdiuretic. The objectives of the present study were: (1) to determine whether infants even more immature and infants cared for under thermal environmental conditions different from those previously studied also undergo these three phases; and (2) to relate these phases to changes in renal function.
Methods:
Consecutive, timed urine collections were made during the first 5 days of life in 32 infants with birth weights of 1000 g or less. Infants were cared for in radiant warmers for 24 hours and then transferred to nonhumidified incubators. Diuresis was defined as urine flow rate (V) of 3 mL or more/kg per hour and weight loss of 0.8 g or more/kg per hour. The physiologic relationships among water and sodium balance, insensible water loss, arterial blood pressure, and renal function were made during the three phases.
Results:
Twenty-eight (87%) of the 32 infants underwent the three homeostatic phases. The median ages of onset and cessation of diuresis were 25 and 96 hours, respectively. There was no correlation between onset of diuresis and change of thermal environment. During the prediuretic phase, V averaged 1.6 mL/kg per hour, and 17 of 28 infants had at least one collection period in which V was less than 1 mL/kg per hour; urinary sodium excretion was 0.1 mEq/kg per hour; the glomerular filtration rate (GFR) was 0.22 mL/kg per hour; fractional excretion of sodium (FENa) was 6.2%; and urine osmolality was dilute (221 mOsm/kg). During the diuretic phase, V and sodium excretion more than tripled; GFR and FENa doubled; and there was no change in urine osmolality. During postdiuresis, V and Na excretion decreased to values intermediate between the prediuretic and diuretic phases, and FENa fell to prediuretic levels, but there was no change in GFR or urine osmolality. There was poor correlation between blood pressure and GFR. Insensible water loss was high and variable during all phases, exceeding 190 mL/kg per day in the smallest infants.
Conclusions:
Extremely low birth weight infants manifest three phases of fluid and electrolyte homeostasis, as do more mature infants, independent of thermal environment. Diuresis and natriuresis are the result of abrupt increases in GFR and FENa. We speculate that this may be the result of expansion of the neonatal extracellular space as fetal lung fluid is reabsorbed.
More Related Videos
 09:36
Effect of Hyaluronic Acid 35 kDa on an In Vitro Model of Preterm Small Intestinal Injury and Healing Using Enteroid-Derived Monolayers
Published on: July 28, 2022
 08:58
Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
Related Concept Videos
 01:23
Transcellular Transport of Solutes
 01:17
Reabsorption and Secretion in the Loop of Henle
 01:20
Formation of Dilute Urine
Filtrate Osmolarity in the PCT
Initially, as the filtrate passes through the proximal convoluted tubule (PCT), its...
 01:18
Fluid Movement Between Compartments
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism