Related Experiment Video
Updated: Sep 25, 2026

A High-content In Vitro Pancreatic Islet β-cell Replication Discovery Platform
Published on: July 16, 2016
Serum "big insulin-like growth factor II" from patients with tumor hypoglycemia lacks normal E-domain O-linked
W H Daughaday1, B Trivedi, R C Baxter
1Department of Medicine, Washington University School of Medicine, St. Louis, MO 63110.

Abstract:
The insulin-like growth factor II (IGF-II) gene is overexpressed in many mesenchymal tumors and can lead to non-islet-cell tumor hypoglycemia (NICTH). ProIGF-II consists of the 67 aa of IGF-II with a carboxyl 89-aa extension, the E domain. A derivative of proIGF-II containing only the first 21 aa of the E domain [proIGF-II-(E1-21)] has been isolated by others from normal serum and has O-linked glycosylation. We found that the "big IGF-II" of normal serum, as detected by an RIA directed against residues 1-21 of the E domain of proIGF-II, was reduced in size by treatment with neuraminidase and O-glycosidase. The big IGF-II, which is greatly increased in NICTH sera, was unaffected by neuraminidase and O-glycosidase treatment. We have also shown that big IGF-II from normal serum is retained by jacalin lectin columns and that big IGF-II from NICTH serum was not retained, indicating that it lacked O-glycosylation. Normal O-linked glycosylation may be required for proper peptidase processing of proIGF-II. The lack of normal O-linked glycosylation by tumors may explain the predominance of big IGF-II in NICTH sera. In normal serum, most of the IGF-II is present in a 150-kDa ternary complex with IGF-II binding protein (IGFBP) 3 and alpha subunit. In NICTH serum, however, the complexes carrying big IGF-II are < 50 kDa. We investigated whether big IGF-II of NICTH was responsible for this abnormality. Tumor big IGF-II and IGF-II were equally effective in forming the 150-kDa complex with purified IGFBP-3 and 125I-labeled alpha subunit. Both 125I-labeled IGF-II and 125I-labeled proIGF-II-(E1-21), when incubated with normal serum, formed the 150-kDa complex as detected by Superose 12 exclusion chromatography. We conclude that the nonglycosylated big IGF-II of NICTH serum can form normal complexes with serum IGFBPs. The defective binding in NICTH is attributable to defective IGFBP-3 binding.
More Related Videos
 06:25
Ex Vivo Culture of Circulating Tumor Cells in the Cerebral Spinal Fluid from Melanoma Patients to Study Melanoma-Associated Leptomeningeal Disease
Published on: March 29, 2024
 08:34
Precise Visualization of Insulin Receptors A and B in Murine Brain with an RNA In Situ Hybridization Assay
Published on: July 15, 2025
Related Concept Videos
 01:05
Insulin Secretory Vesicles
 01:25
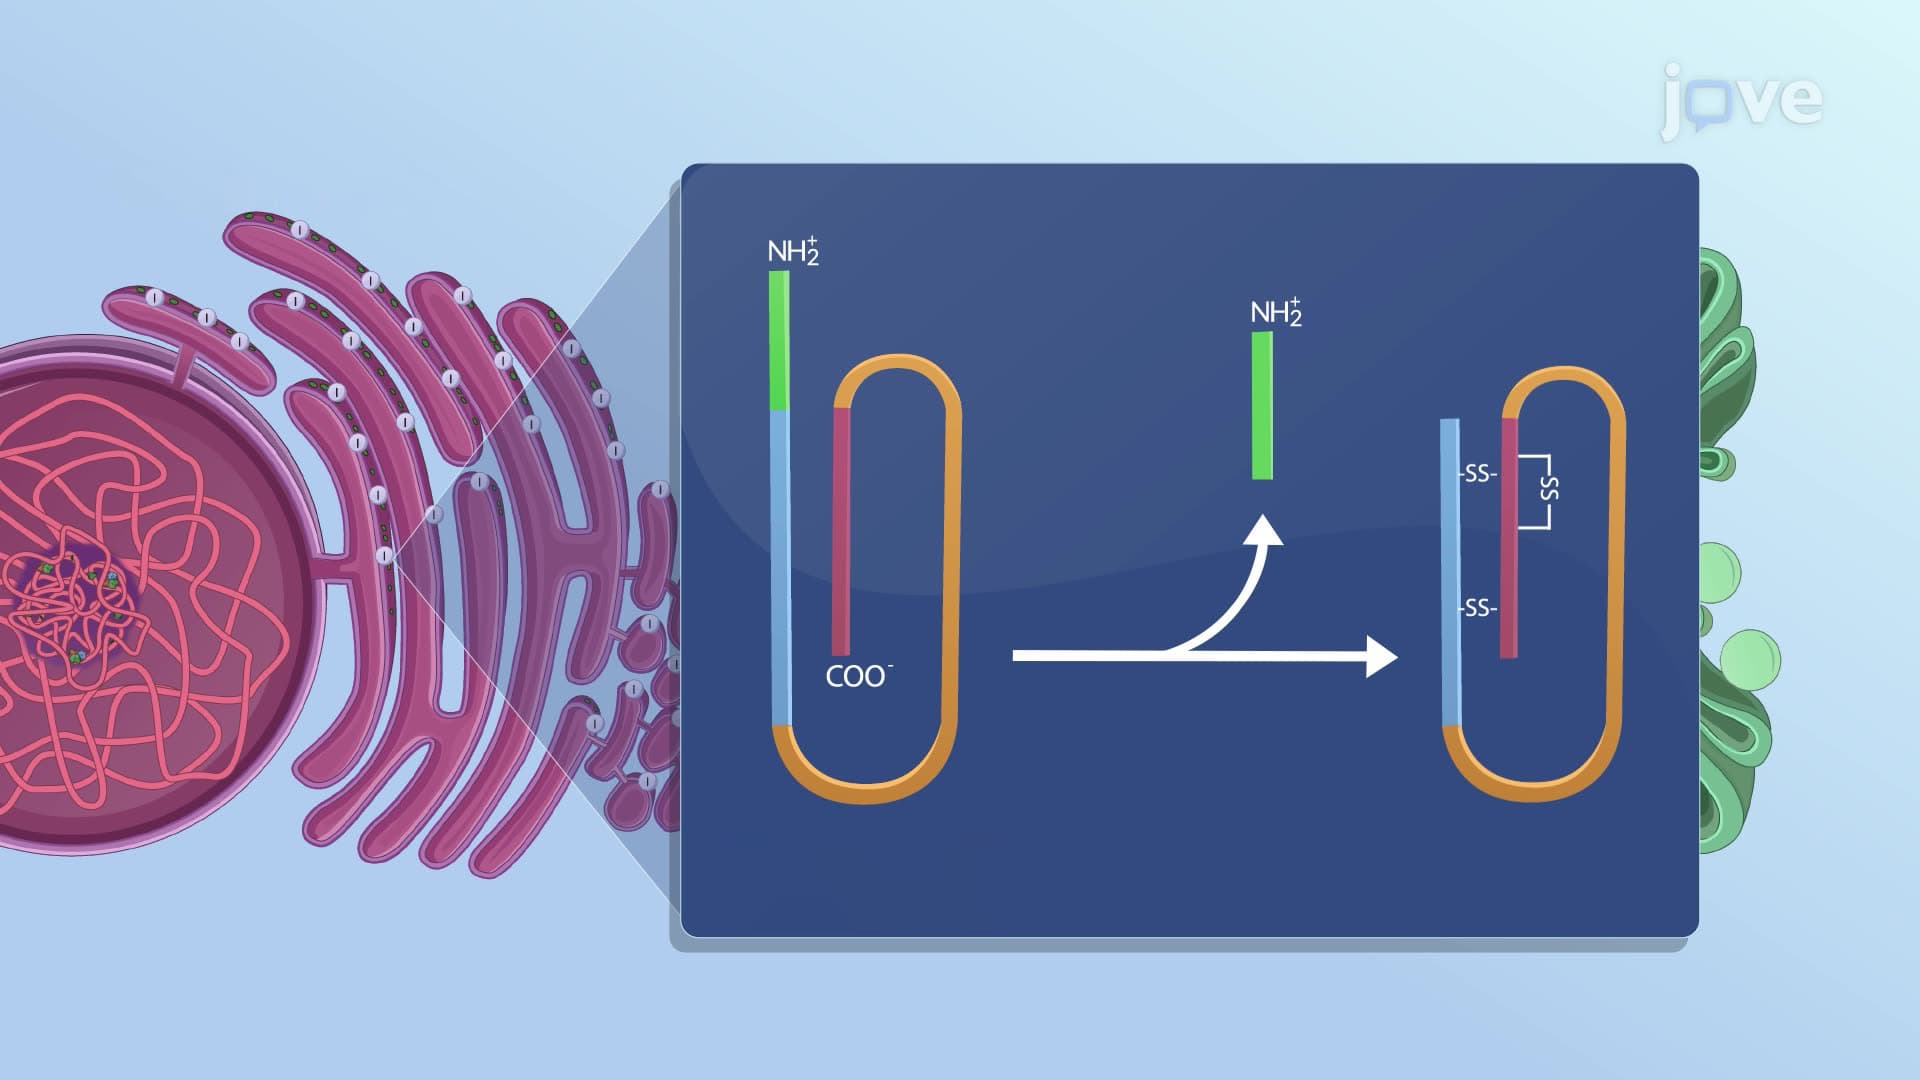
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:15
Hypoglycemia and Glucagon
 01:26
Type I Diabetes II: Pathophysiology
 01:24
Type II Diabetes II: Pathophysiology
 01:26
Hypoglycemia