Related Experiment Video
Updated: Aug 19, 2026
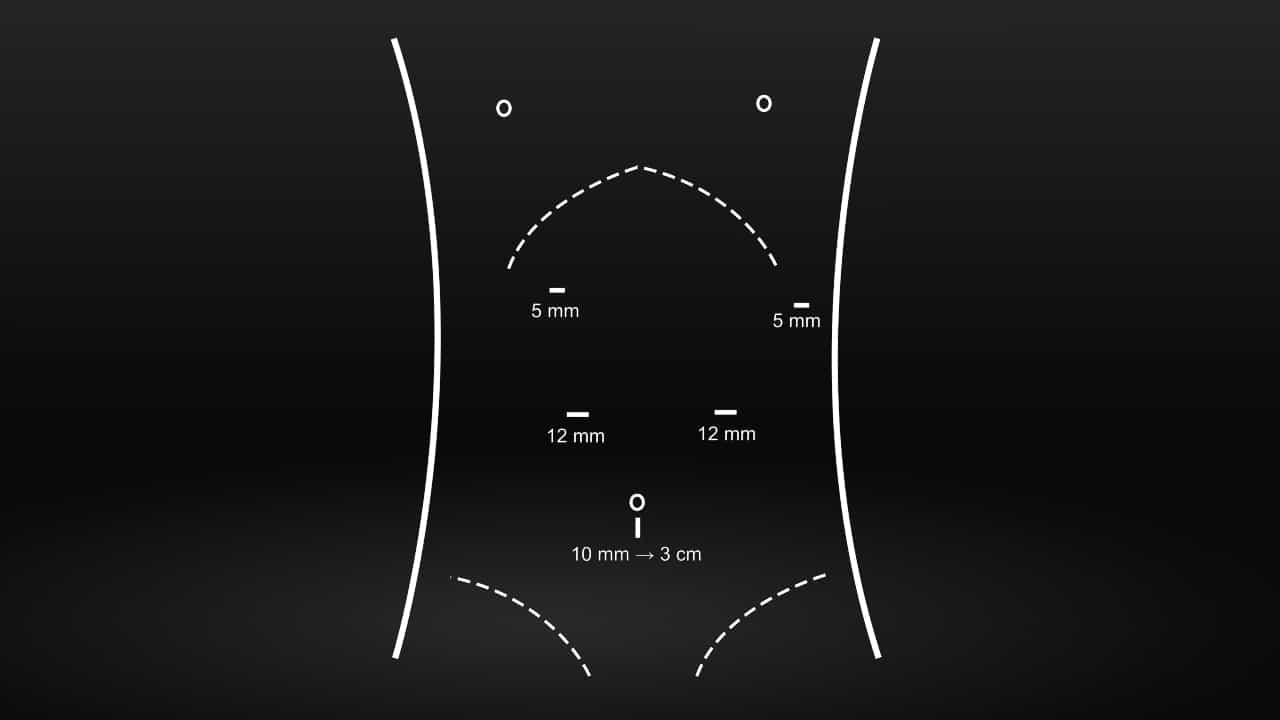
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Current management of bleeding peptic ulcer. A review
1Department of Medicine, University of Birmingham, Queen Elizabeth Hospital, Edgbaston, England.

Abstract:
In the United Kingdom, acute bleeding from peptic ulcer is estimated to account for 25 admissions to hospital per 100,000 population annually. Overall mortality has been reported at around 10%. Accurate initial assessment for the identification of high risk groups, prompt resuscitation, close monitoring and timely intervention for rebleeding improves survival. In patients not responding to initial resuscitation and those who rebleed, emergency endoscopy identifies the source of bleeding in the majority and is essential to enable endoscopic therapy. Injection of a vasoconstrictor and/or sclerosant into a visible or bleeding vessel, or thermal coagulation, reduces the incidence of rebleeding and probably decreases mortality. In general terms, 'early' surgical intervention is indicated for those aged over 60 years in whom bleeding recurs or continues despite endoscopic measures. The low mortality (< 5%) reported from specialist units and units adhering to strict protocols of management should become the norm. The use of antacids, histamine H2-receptor antagonists or omeprazole does not influence mortality or the incidence of early rebleeding in patients with acute haemorrhage from peptic ulcer. Although not used routinely, tranexamic acid has been shown to have significant benefit.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:27
Peptic Ulcer
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications