Related Experiment Video
Updated: Aug 19, 2026

Isolation of Human Atrial Myocytes for Simultaneous Measurements of Ca2+ Transients and Membrane Currents
Published on: July 3, 2013
Myocyte contractile responsiveness after hypothermic, hyperkalemic cardioplegic arrest. Disparity between exogenous
M J Cavallo1, B H Dorman, F G Spinale
1Department of Anesthesiology, Medical University of South Carolina, Charleston 29425-2207, USA.

Insights
Hypothermic, hyperkalemic cardioplegic arrest (HHCA) impairs heart muscle cell function. Beta-adrenergic receptor agonists improved function, suggesting alternative mechanisms beyond calcium levels are involved after HHCA.
Area of Science:
- Cardiology
- Cellular Physiology
- Cardiac Surgery
Background:
- Acute left ventricular dysfunction is common post-hypothermic, hyperkalemic cardioplegic arrest (HHCA).
- Inotropic interventions are often needed for separation from cardiopulmonary bypass.
- Mechanisms of depressed left ventricular function and cellular responses to inotropes after HHCA remain unclear.
Purpose of the Study:
- To investigate the effects of calcium (Ca2+) and beta-adrenergic receptor (beta AR) agonists on isolated myocyte contractile function following HHCA.
- To elucidate the cellular mechanisms underlying depressed cardiac function after HHCA.
Main Methods:
- Myocytes were isolated from porcine left ventricles and divided into normothermic control and HHCA groups.
- Contractile function was assessed under varying extracellular Ca2+ and beta AR agonist (isoproterenol) concentrations.
- Myocyte surface area and response to hypoxia were also evaluated.
Main Results:
- HHCA significantly reduced baseline myocyte contractile function compared to controls.
- Increased extracellular Ca2+ minimally improved function in the HHCA group, unlike the control group.
- Beta AR stimulation improved contractile function in both groups, though to a lesser extent in the HHCA group.
- Hypoxia exacerbated contractile dysfunction, but beta-adrenergic responsiveness was maintained.
Conclusions:
- Calcium depletion is unlikely the primary cause of depressed contractility after HHCA.
- Improved function with beta AR stimulation suggests alternative mechanisms, possibly altered myofilament sensitivity to Ca2+, are involved.
- Left ventricular dysfunction after HHCA stems from electromechanical uncoupling and hypoxic conditions.
Background:
Acute left ventricular dysfunction is commonly encountered after hypothermic, hyperkalemic cardioplegic arrest (HHCA) and often requires inotropic intervention for successful separation from cardiopulmonary bypass. However, the basic mechanisms involved in depressed left ventricular function and the cellular basis for the differential effects of inotropic drugs after HHCA are unknown. Accordingly, the goal of this study was to determine the effects of calcium (Ca2+) and beta-adrenergic receptor agonists (beta AR) stimulation on isolated myocyte contractile function after HHCA.
Methods:
Myocytes were isolated from the left ventricle of nine pigs and randomly assigned to one of the following treatment groups: (1) normothermic, control: incubation in oxygenated cell culture media for 2 h at 37 degrees C; and (2) cardioplegia: incubation in 4 degrees C crystalloid cardioplegia for 2 h, followed by rewarming. Steady-state myocyte contractile function was measured after pulse stimulation at baseline, in the presence of extracellular Ca2+ (3-10 mM), and in the presence of the beta AR agonist isoproterenol (2-100 nM). Myocyte profile surface area was measured for both normothermic myocytes and myocytes after HHCA. In a separate set of experiments, myocyte contractile function also was documented after 2 h of hypoxic conditions with both normothermic incubation and HHCA, in the presence and absence of beta AR stimulation.
Results:
Baseline myocyte contractile function was significantly less in the cardioplegia group compared to control. Extracellular Ca2+ produced a dose-dependent significant increase in myocyte contractile function in the normothermic control group, whereas increased extracellular Ca2+ only minimally increased myocyte contractile function in the cardioplegia group. A dose-dependent, significant increase in myocyte contractile function was observed in both groups after beta AR stimulation by isoproterenol; however, myocyte contractile function in the cardioplegia group was decreased compared to the control group. Hypoxia under normothermic conditions significantly reduced myocyte contractile function, myocyte relaxation, and beta-adrenergic responsiveness. Hypoxia in combination with cardioplegic arrest compounded the negative effects on contractile processes but did not further impair beta-adrenergic responsiveness. Myocyte profile surface area was significantly increased after HHCA.
Conclusions:
The minimal improvement in myocyte contractile function after HHCA with increased extracellular Ca2+ suggests that Ca2+ depletion is not the primary mechanism for depressed myocyte contractility after HHCA. On the other hand, because beta AR administration improved myocyte contractile function after HHCA, the cellular basis for the effects of beta AR stimulation after HHCA is probably not increased myocyte Ca2+ but rather alternative mechanisms, such as changes in myofilament sensitivity to Ca2+. These results also suggest that the abnormalities in left ventricular function after HHCA result from the direct effects of hyperkalemic induced electromechanical uncoupling as well as relative hypoxic conditions.
Related Concept Videos
 01:27
Feedback Regulation of Calcium Concentration
Various transmembrane receptors, such as G protein-coupled receptors (GPCRs), elicit a response to extracellular signals by increasing cytosolic calcium. Activated GPCRs...
 01:29
Relaxation of Skeletal Muscles
When an action potential reaches the axon terminal, it depolarizes the membrane and opens voltage-gated sodium channels. Sodium ions enter the cell, further depolarizing the presynaptic membrane. This depolarization causes voltage-gated calcium channels to open.
 01:27
Specialized Characteristics of Cardiac Muscles
Cardiac muscle cells are smaller than skeletal muscles, averaging 10–20 mm in diameter and 50–100 mm in length. However, they have large energy demands for continuous contraction and relaxation. This energy is almost exclusively derived from aerobic metabolism of energy reserves in...
 01:25
Smooth Muscle Contraction
The onset of contraction is triggered by an increase in calcium ions within the sarcoplasm, similar to the process in striated muscle. However, smooth muscles have a relatively smaller reservoir of the sarcoplasmic...
 01:19
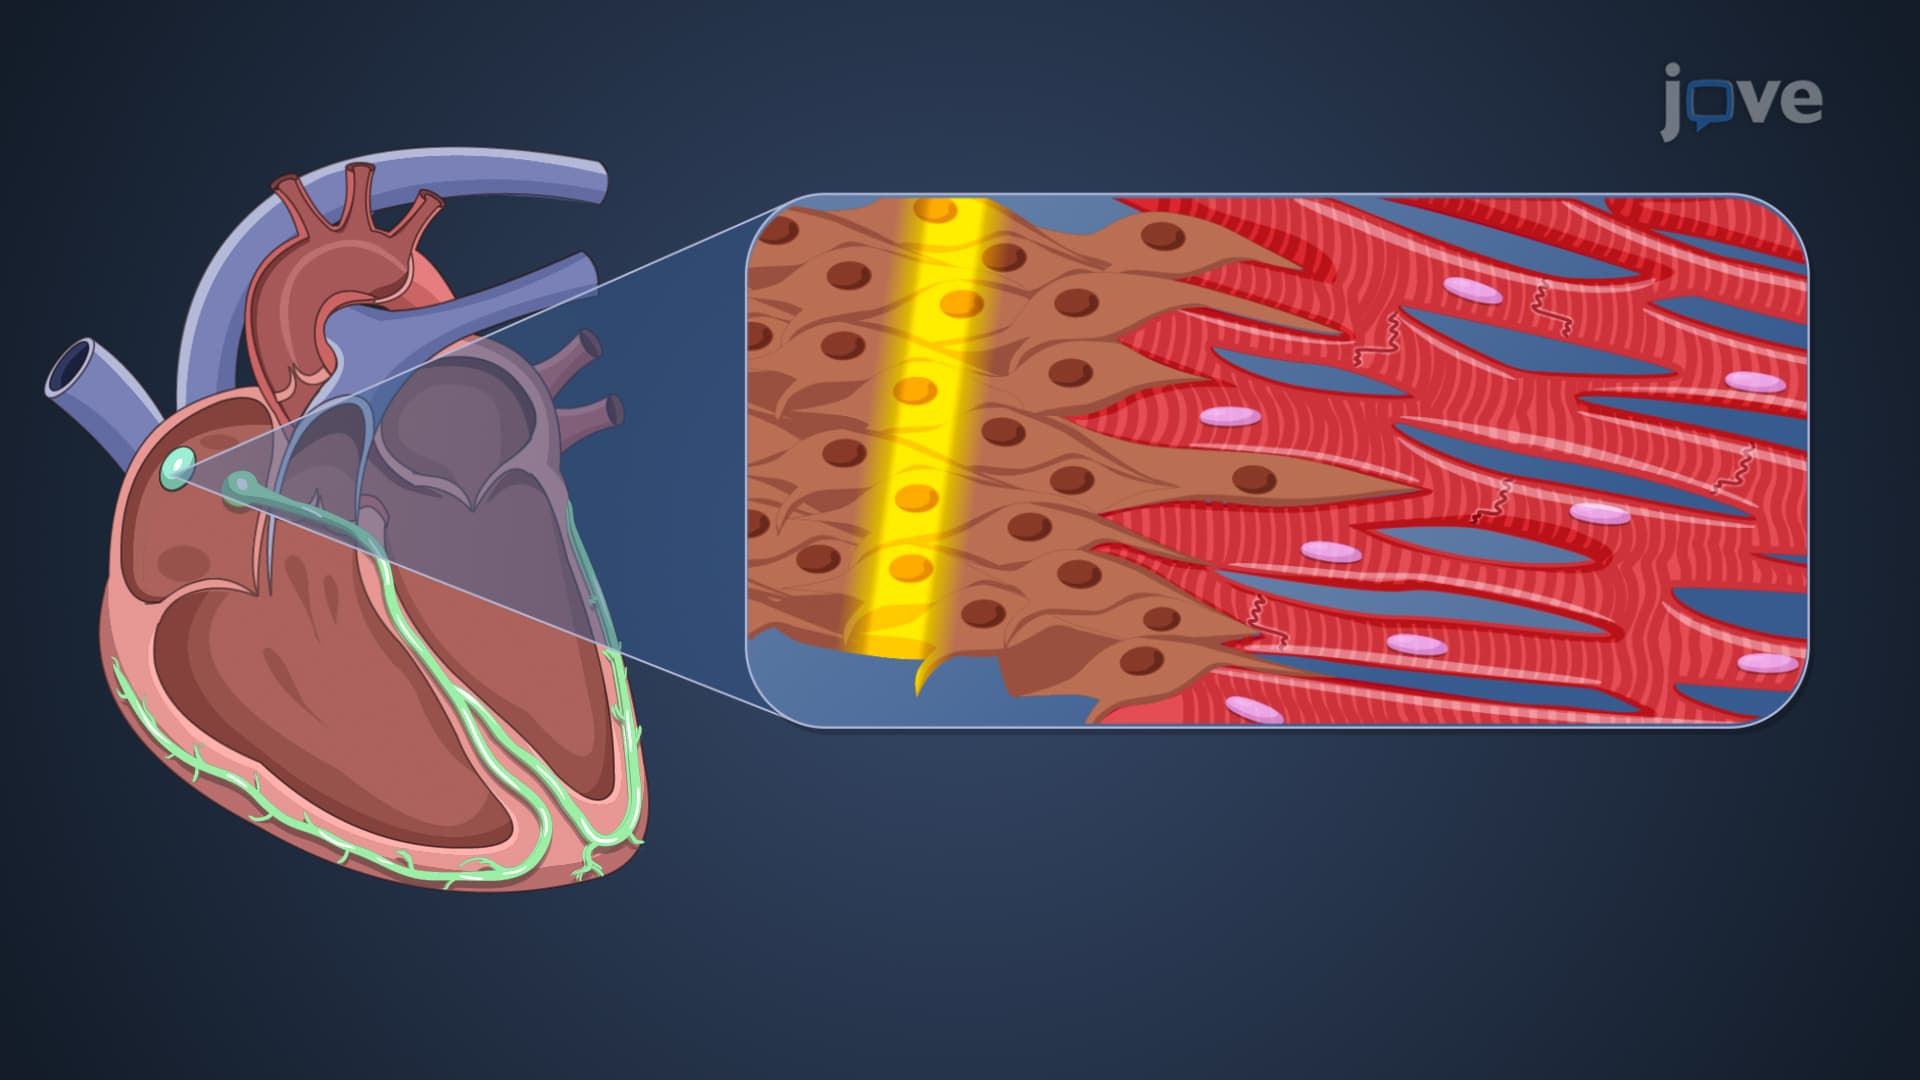
Electrophysiology of Normal Cardiac Rhythm
 01:30
Cardiac Action Potential
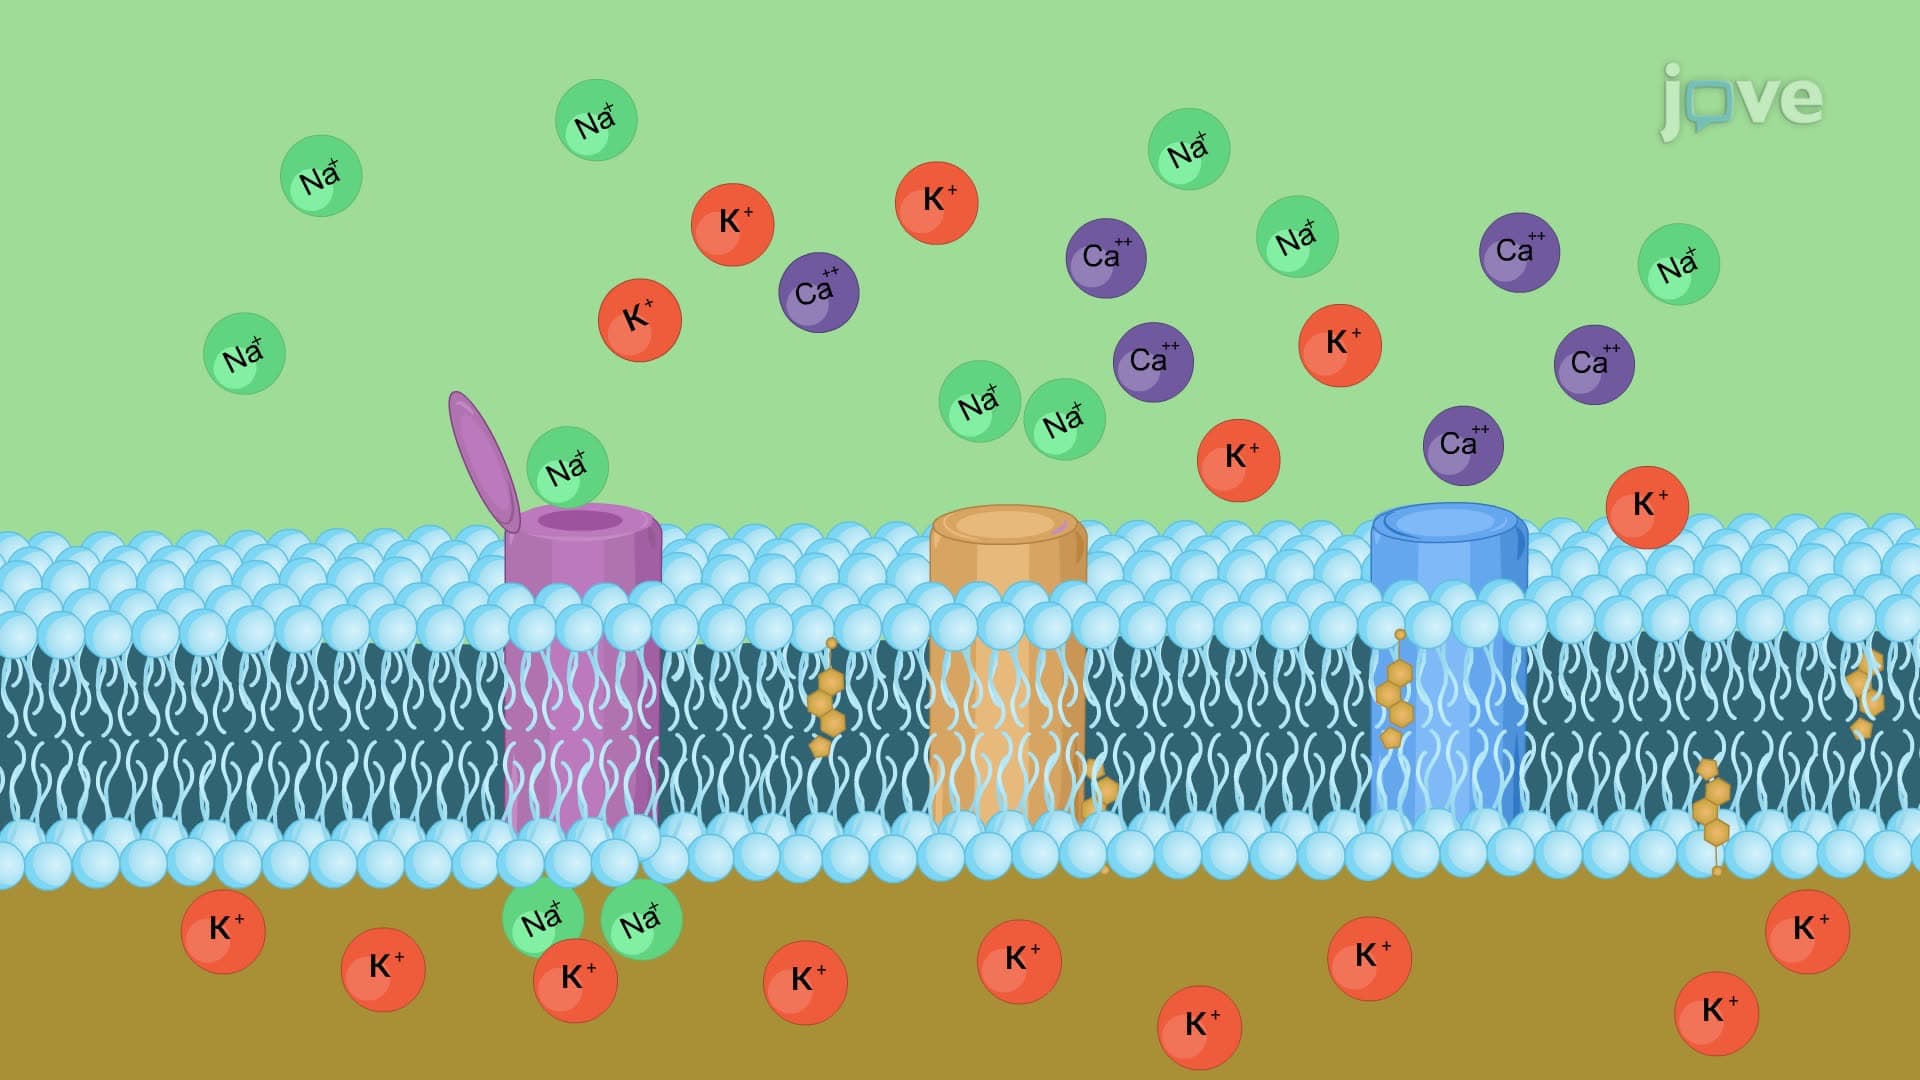
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials