Adrenoreceptors, endothelial function, and lipid profile: effects of atenolol, doxazosin, and carvedilol
Related Experiment Video
Updated: Oct 12, 2026

Induction of Atherosclerotic Plaques Through Activation of Mineralocorticoid Receptors in Apolipoprotein E-deficient Mice
Published on: September 26, 2018
1La Paz Hospital, Madrid, Spain.

Insights
Alpha-1 blockers improve blood clotting and lipid profiles in hypertensive patients with ischemic heart disease. Beta-blockers reduce ischemia but do not improve fibrinolysis or lipid profiles.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Hypertension management often fails to adequately reduce ischemic heart disease incidence.
- Adrenergic blockade's cardiovascular and endothelial effects require further investigation.
Purpose of the Study:
- To evaluate the cardiovascular effects of alpha-blockade, beta-blockade, and dual-action adrenergic blockade.
- To assess the impact of these treatments on endothelial fibrinolytic response and lipoprotein metabolism in hypertensive patients with ischemic heart disease.
Main Methods:
- 78 hypertensive patients with stable angina and silent ischemia were treated with atenolol (beta-blocker), doxazosin (alpha-1 inhibitor), or carvedilol (dual-action).
- Cardiovascular parameters, endothelial fibrinolytic activity, and lipoprotein metabolism were assessed at baseline and 6 months.
Main Results:
- Atenolol improved exercise tolerance but did not affect fibrinolysis.
- Doxazosin enhanced endothelial fibrinolytic activity and improved the lipoprotein ratio without anti-ischemic effects.
- Carvedilol reduced ischemia and improved fibrinolytic activity post-anoxia, without altering the lipid profile.
Conclusions:
- Alpha-1 receptor inhibition improves endothelial fibrinolytic activity and lipid profiles in hypertensive patients.
- Beta-blockade demonstrates anti-ischemic effects but does not enhance fibrinolysis or improve the lipoprotein ratio.
Background:
The use of effective blood-pressure-lowering drugs has not achieved the expected reduction in the incidence of ischaemic heart disease in hypertensive patients. This study examined the cardiovascular effects of adrenergic blockade (alpha or beta, or both) and its effect on the fibrinolytic response of the endothelium to anoxia and lipoprotein metabolism in 78 hypertensive patients with ischaemic heart disease.
Methods:
All patients had stable angina on positive exercise testing and silent ischaemia on 24 h Holter monitoring at baseline and 6 months after effective blood-pressure-lowering treatment with the selective beta-blocker atenolol, the alpha 1-inhibitor doxazosin, or the dual-action drug carvedilol.
Results:
Atenolol increased the effort time (P < 0.05), total ischaemia (P < 0.05), and the number of ischaemic episodes (P < 0.05). It reduced the lipoprotein ratio (P < 0.05) but did not modify the fibrinolytic activity of the endothelium. Doxazosin increased the fibrinolytic index (ratio of plasminogen activator to its main inhibitor) before (P < 0.05) and after anoxia (P < 0.0001) and the lipoprotein ratio (P < 0.001), without an anti-ischaemic effect. Carvedilol increased the effort time (P < 0.05), reducing total ischaemia (P < 0.05), the number of ischaemic episodes (P < 0.01), and increasing the post-anoxia fibrinolytic index (P < 0.05) without modifying the lipid profile.
Conclusions:
At antihypertensive equipotent doses, the inhibition of alpha 1-receptors improves the endothelial fibrinolytic activity and the lipid profile. beta-Blockade has an anti-ischaemic action, but reduces the lipoprotein ratio (ApoA/ApoB) and does not improve endothelial fibrinolytic activity.
More Related Videos


Related Concept Videos
 01:31
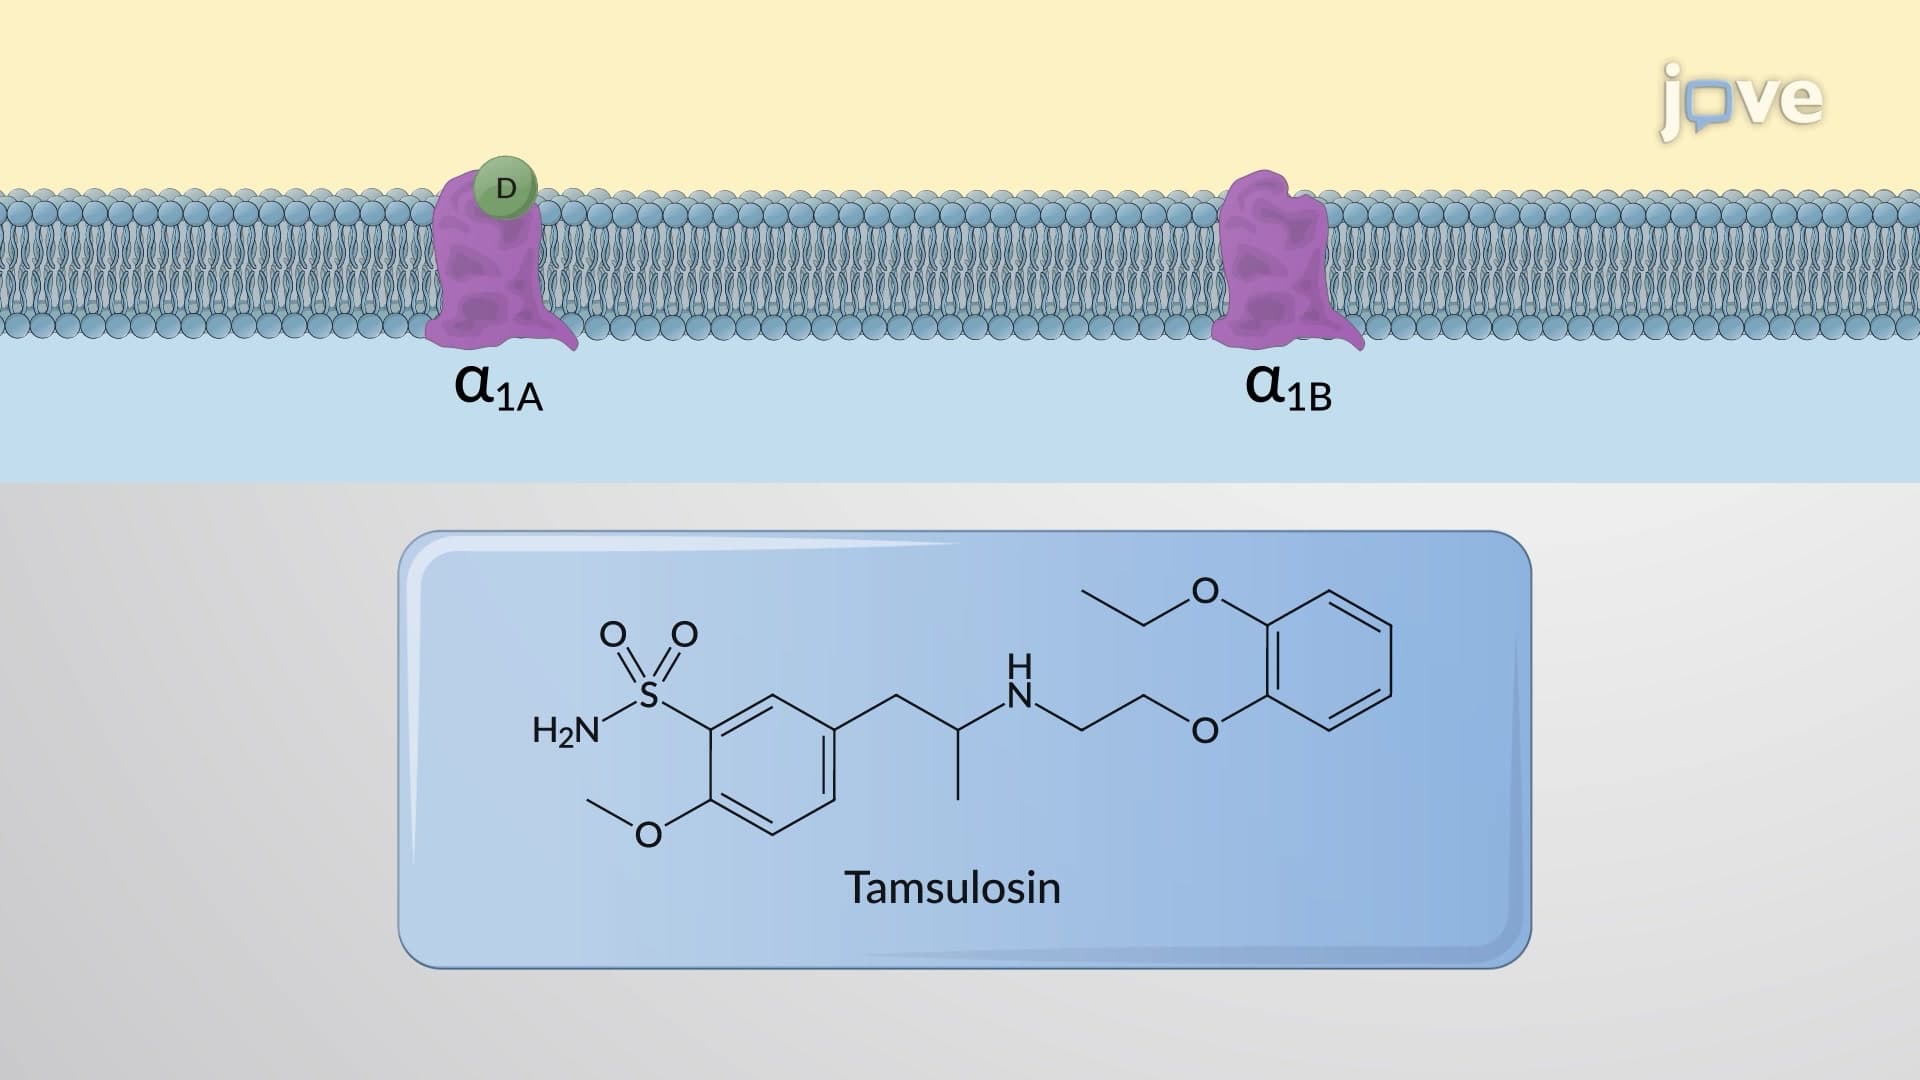
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:26
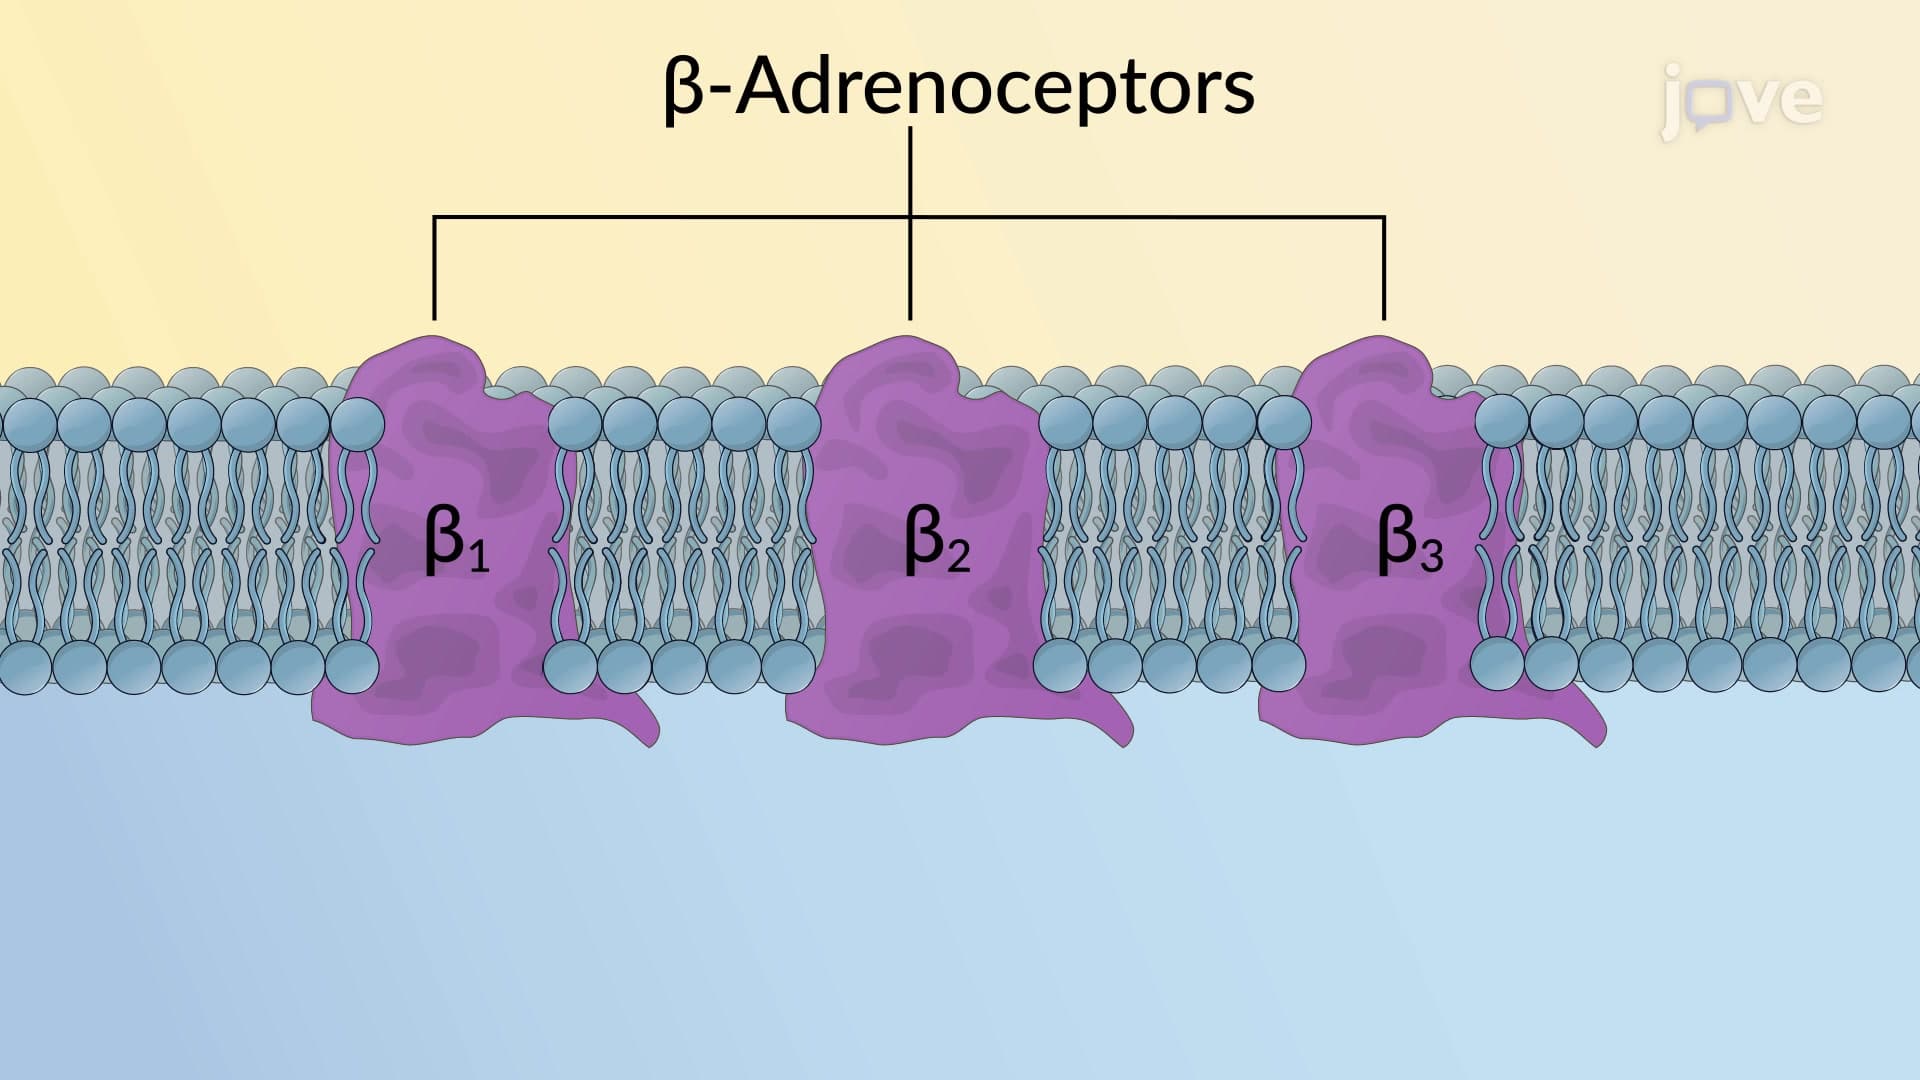
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers