Related Experiment Video
Updated: Sep 26, 2026

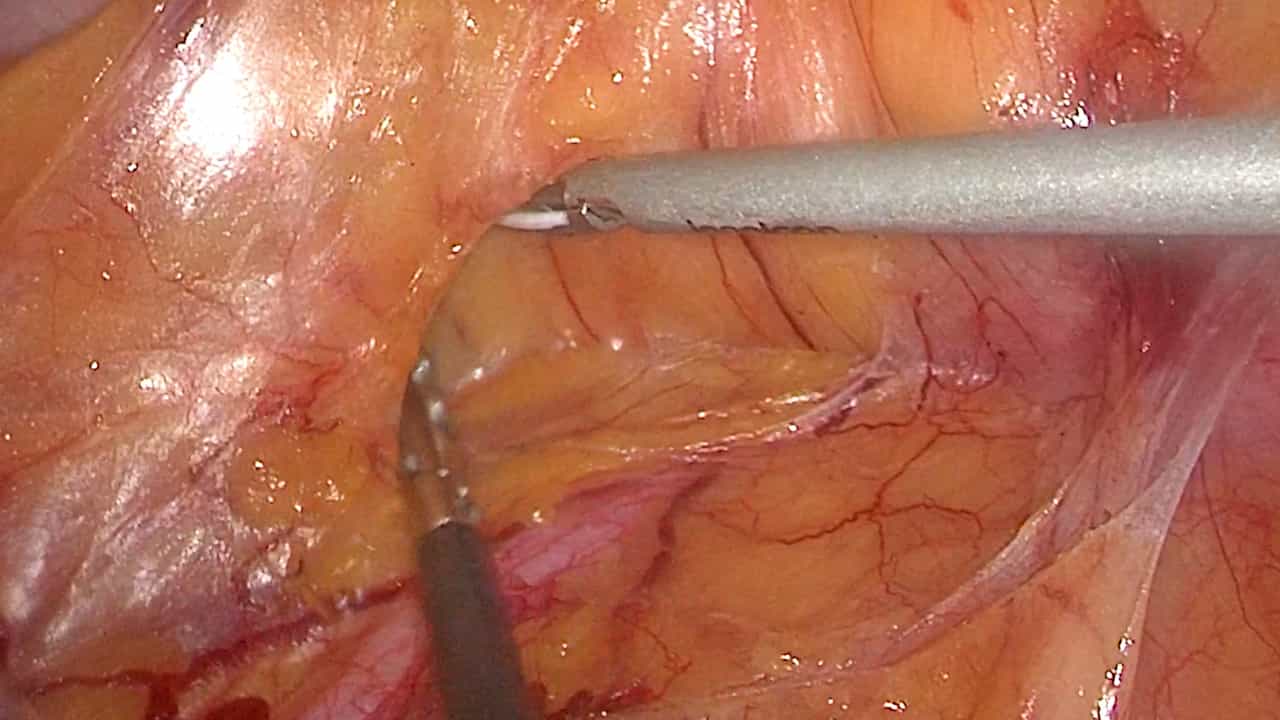
Clinical Application of 24 G Cannula Needle and 3-0 Polypropylene Suture in Vas Deferens Exploration
Published on: February 10, 2023
The pediatric inguinal hernia: is contralateral exploration justified?
1Department of Surgery, Universidad Central del Caribe, School of Medicine, San Juan, PR 00922-0426.

Insights
Contralateral inguinal hernia exploration in children is justified, especially in females and infants under two months. Routine exploration helps detect patent processus vaginalis, preventing future hernias without significant complications.
Area of Science:
- Pediatric Surgery
- Surgical Outcomes
Background:
- Inguinal hernias are common in infants, with potential for contralateral involvement.
- Bilateral repair is often considered to address this risk.
Purpose of the Study:
- To evaluate the justification for contralateral inguinal hernia exploration in pediatric patients.
- To identify factors influencing positive contralateral findings.
Main Methods:
- Retrospective review of 161 pediatric patients undergoing bilateral inguinal hernia repair.
- Analysis of intraoperative findings, including patent processus vaginalis.
- Six-year follow-up for complications like testicular issues or recurrence.
Main Results:
- Positive contralateral findings (hernial sac or patent processus vaginalis) were observed in 74% of right-sided and 72% of left-sided hernias.
- Females and infants younger than two months showed a higher probability of positive contralateral findings.
- No significant complications such as testicular edema, atrophy, vas deferens injury, or recurrence were reported.
Conclusions:
- Routine contralateral exploration is beneficial for identifying and addressing patent processus vaginalis in pediatric inguinal hernias.
- Specific criteria, including surgeon experience and minimizing operative time, support routine contralateral exploration.
Abstract:
To determine if contralateral inguinal hernia exploration is justified we decided to study our experience with 161 consecutive cases who underwent bilateral repair during a 30 months period. 61% of the population were infants younger than two years of age, and 19% premature babies. 69 pts presented with an RIH, 47 with an LIH and 45 pts with BIH. 16% suffered an episode of preoperative incarceration which were all reduced satisfactorily and operated promptly. A positive contralateral finding (either a hernial sac or a patent processus vaginalis) was identified in 74% RIH and 72% LIH patients upon exploration. No incidence of testicular edema/atrophy, vas deferens injury, or recurrence was reported in the six-year follow-up of the study. Statistical analysis of the contralateral findings during surgery with sex, gestational age and age at operation showed that females and infants younger than two months of age had a higher probability of having positive findings. We could not show that prematurity or left-sided hernias were associated with a higher positive contralateral rate. The major benefit of contralateral exploration is based on the fact that it allows discovery and elimination of a patent processus vaginalis so a hernia cannot develop subsequently. We conclude by establishing certain criteria that justifies the routine contralateral exploration of the pediatric hernia: the surgeon should be experienced in child care, associated conditions should not increase the surgical risks significantly, time-consuming dissections of the cord structures should be discouraged, and the operating time should be kept to a minimum.